Related Experiment Video
Updated: Jun 24, 2026
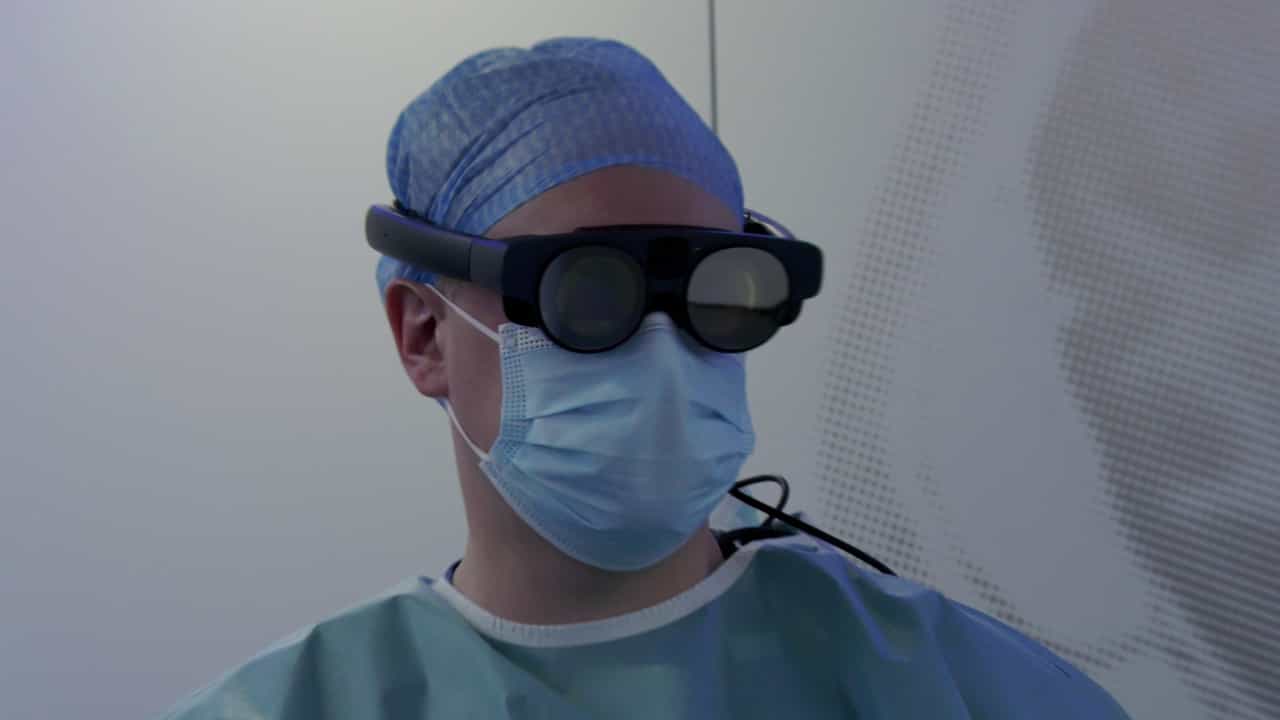
Pedicle Screw Placement Using an Augmented Reality Head-Mounted Display in a Porcine Model
Published on: May 24, 2024
Diameter, length, and direction of pedicle screws for scoliotic spine: analysis by multiplanar reconstruction of
Katsushi Takeshita1, Toru Maruyama, Hirotaka Chikuda
1Department of Orthopaedic Surgery, The University of Tokyo, Tokyo, Japan. Takeshita-ort@h.u-tokyo.ac.jp

Study Design:
A morphometric study of thoracic and lumbar spine in scoliosis.
Objective:
The purpose of the present study was to evaluate the appropriate values of diameter, length, and direction of pedicle screws with a straightforward trajectory in scoliosis.
Summary Of Background Data:
Several authors have analyzed the pedicle shape and evaluated the feasibility of pedicle screws in the scoliotic spine. To date, however, none of them have reported analysis by multiplanar reconstruction of computed tomography.
Methods:
Computed tomography with a thickness of 1.25 mm was obtained before surgery in 41 Japanese with scoliosis. A total of 1100 pedicles were evaluated by simulating screw placement with the straightforward approach in a multiplanar reconstruction image. We chose the optimal slice where the insertion point and direction were determined to get the largest diameter of a screw in every vertebra. Length from the insertion point to the tip of the simulated screw was measured.
Results:
Screws of L1 and L2 were significantly smaller than those of T12 and L3 (P < 0.001). On the concave side, 37% of T3-T9 pedicles did not accept a 4-mm diameter screw even with 25% expansion. Length on the convex side was shorter at T5 and T7-T9 than that on the concave side (P < 0.05). On the convex side, 11% at T4-T8 vertebrae did not accept a 25-mm length screw. Average angle of screws of T1, T2, and L5 was greater than 15 degrees and 17% of the screws at T7-T10 were placed in the lateral direction.
Conclusion:
In T3-T9 on the concave side, pedicle screws with a straightforward trajectory are not held within 37% of pedicles even with plastic deformation. We recommend that surgeons consider combined use of various types of anchoring when preoperative evaluation reveals narrow pedicles for screw placement.
