Related Experiment Video
Updated: Jun 24, 2026

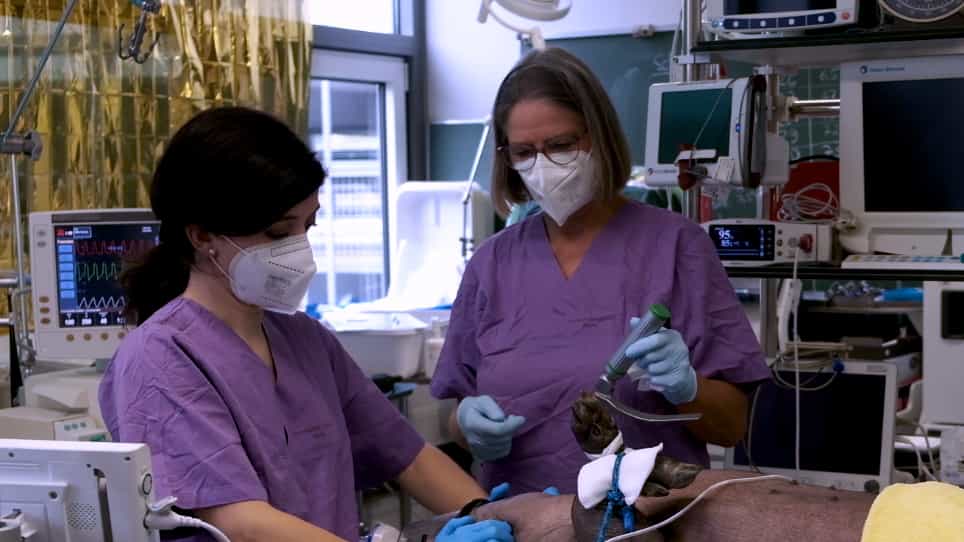
A Structured Approach to Extubation in Mechanically Ventilated Rats
Published on: July 18, 2025
A pilot study of a new test to predict extubation failure
José F Solsona1, Yolanda Díaz, Antonia Vázquez
1ICU Hospital de Mar, Paseo Maritimo 25-29 Barcelona 08003, Spain. 13713@imas.imim.es

Introduction:
To determine whether subjecting patients to 100 ml of additional dead space after a 120-minute weaning trial could predict readiness for extubation.
Methods:
This was a prospective, non-randomised pilot study in an intensive care unit at a university hospital with 14 beds. It included all non-tracheostomised patients with improvement of the underlying cause of acute respiratory failure, and those with no need for vasoactive or sedative drugs were eligible. Patients fulfilling the Consensus Conference on Weaning extubation criteria after 120 minutes spontaneous breathing (n = 152) were included. To the endotracheal tube, 100 cc dead space was added for 30 minutes. Patients tolerating the test were extubated; those not tolerating it received six hours of supplementary ventilation before extubation. The measurements taken and main results were: arterial pressure, heart rate, respiratory rate, oxygen saturation, end-tidal carbon dioxide and signs of respiratory insufficiency were recorded every five minutes; and arterial blood gases were measured at the beginning and end of the test. Extubation failure was defined as the need for mechanical and non-invasive ventilation within 48 hours of extubation.
Results:
Twenty-two patients (14.5%) experienced extubation failure. Only intercostal retraction was independently associated with extubation failure. The sensitivity (40.9%) and specificity (97.7%) yield a probability of extubation failure of 75.1% for patients not tolerating the test versus 9.3% for those tolerating it.
Conclusions:
Observing intercostal retraction after adding dead space may help detect susceptibility to extubation failure. The ideal amount of dead space remains to be determined.
Trial Registration:
Current Controlled Trials ISRCTN76206152.
Related Concept Videos
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement: