Risk factors for septicemia following endoscopic biliary stenting
Related Experiment Video
Updated: Aug 21, 2026
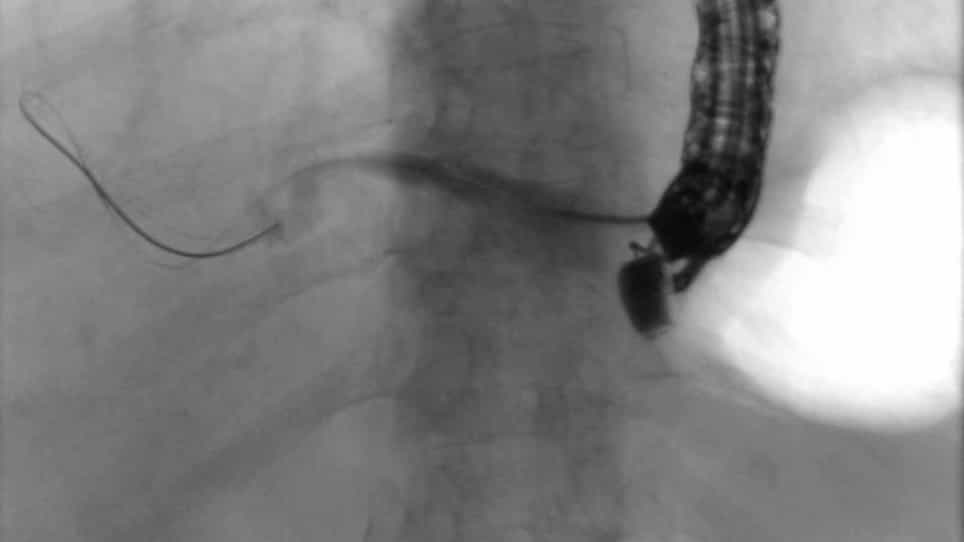
Endoscopic Ultrasound-Guided Biliary Drainage: Endoscopic Ultrasound-Guided Hepaticogastrostomy in Malignant Biliary Obstruction
Published on: March 25, 2022
S Motte1, J Deviere, J M Dumonceau
1Department of Medecine, Hôpital Erasme, Université Libre de Bruxelles, Belgium.

Abstract:
The purpose of this study was to identify patients who were more likely to experience septicemia after endoscopic biliary drainage. In an attempt to determine the relative importance of each risk factor and their possible interdependancy to more precisely identify high-risk patients and to deduce some guidelines for prevention, a discriminant regression analysis of risk factors for septicemia was used. Clinical, biological, and radiological data of 34 consecutive patients who experienced septicemia within 3 days after endoscopic biliary stenting were reviewed retrospectively and compared with data of a group of 71 patients without any septic complication. If only data available before the procedure were used in the discriminant analysis, prior cholangitis and leucocytosis appeared as significant risk factors, but the linear combination of these data could not predict septicemia in 50% of cases. When information concerning the quality of drainage after the procedure was introduced into the analysis, 91% of the septicemic patients were identified, and other expected risk factors such as the nature of the stricture, the type of drainage, or prior cholangitis and leukocytosis had no or marginal predictive values. Patients referred from centers where duodenoscopes might have been poorly disinfected appeared to be at higher risk for Pseudomonas aeruginosa septicemia. These results emphasize the crucial role of the quality of drainage as a risk for septicemia. Regarding the prevention of infection, it is concluded from this study that (a) pure diagnostic endoscopic retrograde cholangiopancreatography should be avoided in obstructed patients if drainage cannot be performed during the same procedure; (b) drainage should be as complete as possible; (c) antibiotics should be administered before ERCP to every patient with suspected obstructive jaundice and should cover P. aeruginosa if local epidemiological data suggest that there is a problem with disinfection of the endoscopes; and (d) the quality of drainage should guide the duration of antibiotic prophylaxis.
More Related Videos
Related Concept Videos
 01:17
Chronic Bowel Disorders: Introduction
Irritable Bowel Syndrome (IBS) is a common disorder affecting the gastrointestinal tract. The distinctive feature is recurrent abdominal pain associated with altered bowel movements, manifesting as constipation, diarrhea, or fluctuating between both. The...
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus.
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:29
Endoscopic Procedures I: Esophagogastroduodenoscopy
During an EGD, the endoscope can be used to:
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:20
Cholecystitis