Related Experiment Video
Updated: Jun 23, 2026


Separation of Immune Cell Subpopulations in Peripheral Blood Samples from Children with Infectious Mononucleosis
Published on: September 7, 2022
[Hyper-IgM syndrome in a boy with recurrent pneumonia and hepatosplenomegaly]

Introduction:
We present a boy diagnosed at age 14 years with hyper-immunoglobulin (Ig) M syndrome, a congenital immunodeficiency characterized by reduced plasma concentrations of IgA, IgE and IgG, with normal or elevated concentrations of IgM. This syndrome is caused by a defect of CD40 ligand (CD40L) on T-helper lymphocytes, impeding the "second signal" during activation of B lymphocytes and interactions of T cells with dendritic cells and macrophages, resulting in the absence of secondary immune response (class switching, affinity maturation, immune memory), as well as responses to T-dependent antigens, with an impairment of cellular immunity.
Case Outline:
The history of the presented patient was dominated by frequent lower respiratory infections and failure to thrive. Physical examination demonstrated severe hepatosplenomegaly. The suspicion of hyper-IgM syndrome was raised by low plasma IgA (0.36 g/l) with high plasma IgM (35.5 g/l), while the concentration of IgG was within the normal range (12.1 g/l). The diagnosis was confirmed by flow cytometry, which demonstrated the absence of expression of CD40L on lymphocytes following stimulation by phorbolmyristylacetate and calcium ionophore. Since the time of diagnosis, intravenous immunoglobulin therapy has led to catch-up growth, recession of hepatosplenomegaly and reduction in the frequency of respiratory infections.
Conclusion:
Our report emphasizes the importance for the primary healthcare paediatrician to be well informed about the clinical presentation and pathogenesis of hyper-IgM syndrome, in order to provide early detection and increase the likelihood of success in treating this rare immunodeficiency. To the best of our knowledge, this is the first case of hyper-IgM syndrome reported in the Republic of Serbia.
Related Concept Videos
 01:22
Development of Immunocompetence
The initial cells that migrate from the fetal thymus settle within the skin and epithelial tissues lining the mouth, digestive tract, and in females, the uterus and vagina. These cells, including skin-based dendritic cells, serve as antigen-presenting cells, playing a key role in T cell activation.
Subsequent T...
 01:36
Humoral Immune Responses
 01:19
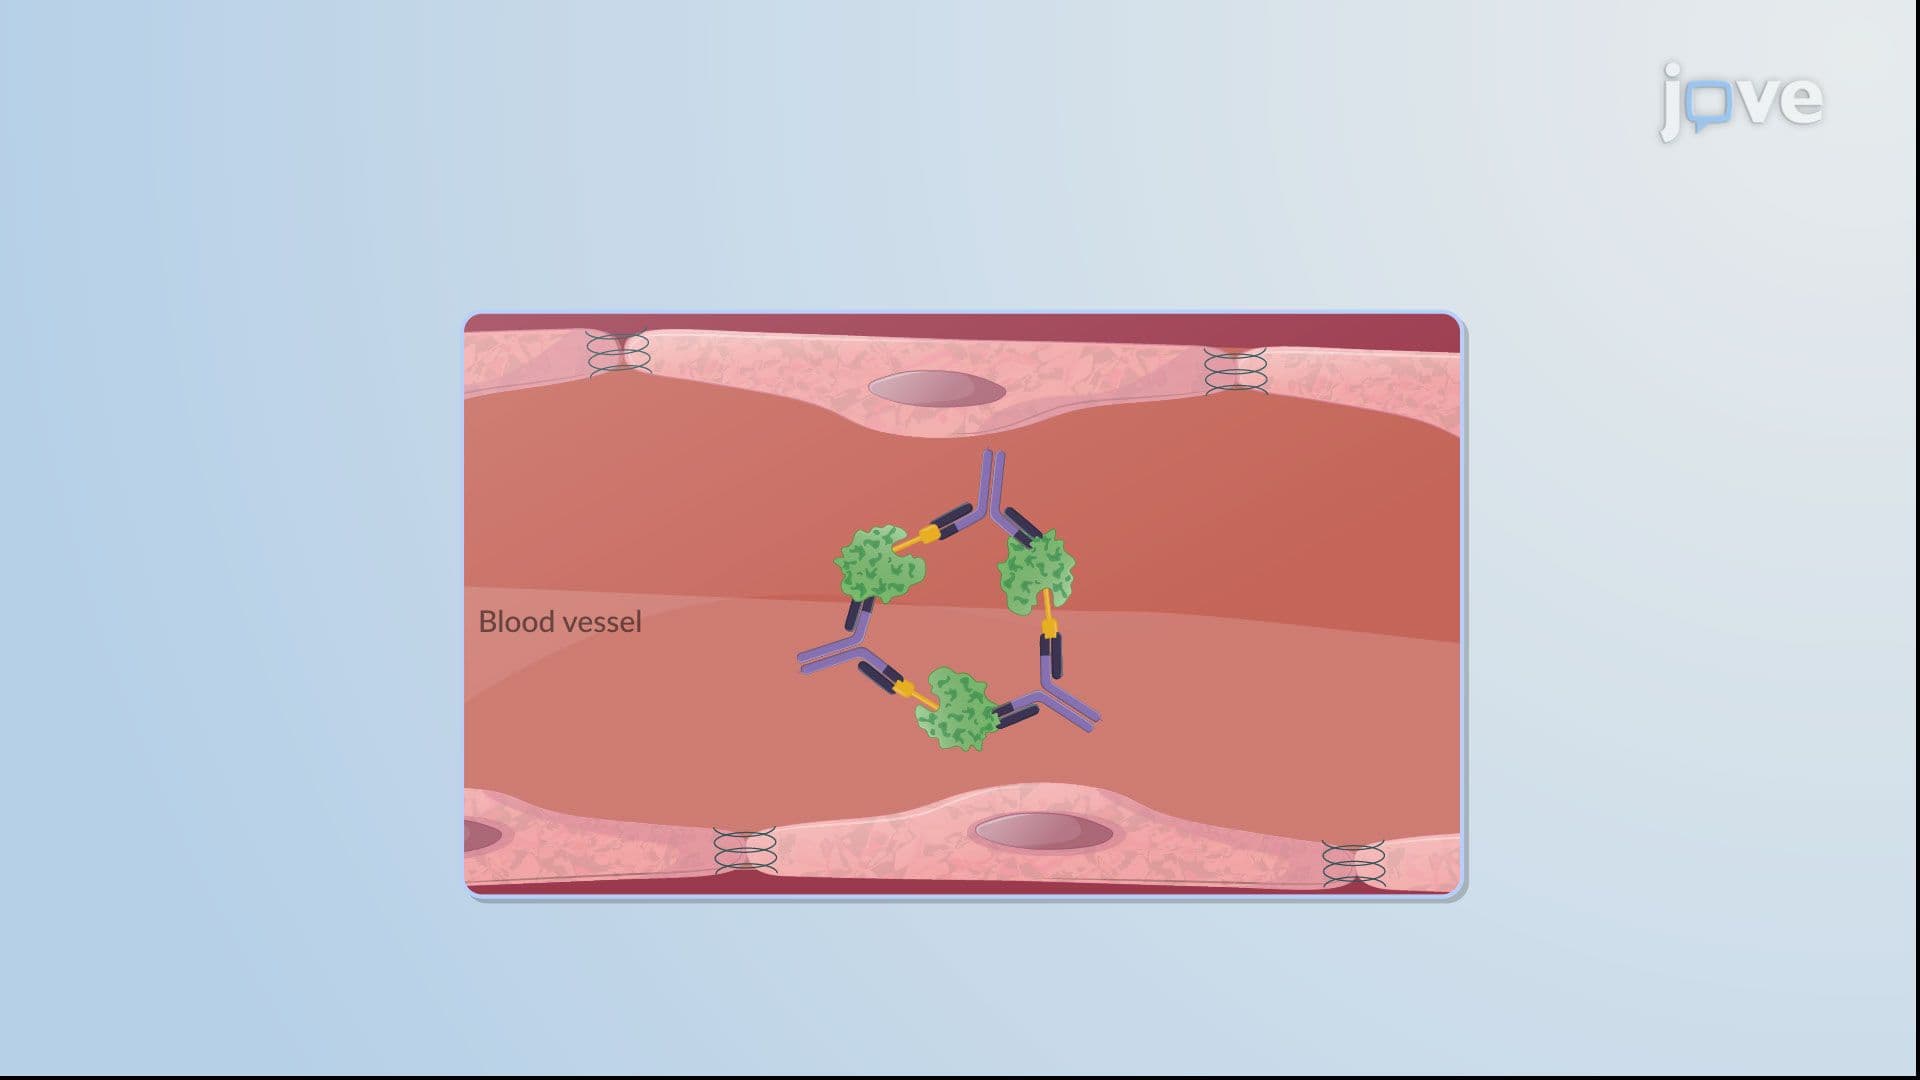
Hypersensitivity Reactions: Immune-Complex Reactions
 01:25
Immunodeficiency Diseases
There are three main causes of immunodeficiency disorders...
 01:27
Myocarditis II: Clinical Features and Diagnostic Tests