Related Experiment Video
Updated: Jun 23, 2026


Introduction of Intracapsular Rotary-cut Procedures (IRCP): A Modified Hysteromyomectomy Procedures Facilitating Fertility Preservation
Published on: January 17, 2019
Uterine rupture in second-trimester misoprostol-induced abortion after cesarean delivery: a systematic review
1From the Department of Obstetrics and Gynecology, University of North Carolina School of Medicine, Chapel Hill, North Carolina.

Objective:
To determine the risk of uterine rupture when using misoprostol for second-trimester abortion in women with a history of cesarean delivery.
Data Sources:
MEDLINE, EMBASE, CINAHL, LILACS, and the Cochrane Library were searched systematically for all articles published before September 2008.
Methods Of Study Selection:
Sixty-three articles were found using the above data sources. I excluded case reports, narrative reviews or commentaries, studies that excluded women with a history of cesarean delivery, studies with unrelated outcomes, studies not conducted in humans, and studies that were not available in English. The remaining 16 studies that described misoprostol use for second-trimester abortion in women with a history of cesarean delivery were examined.
Tabulation, Integration, And Results:
The number of participants with and without cesarean delivery, regimen of medical abortion used, and cases of uterine rupture were reviewed. To estimate the risk of uterine rupture in women with prior cesarean delivery undergoing second-trimester abortion with misoprostol and number needed to harm, I pooled the results of all 16 studies. The risk of uterine rupture in women with prior cesarean delivery was 0.28% (95% confidence interval [CI] 0.08-1.00%). The risk of uterine rupture in women without prior cesarean delivery was 0.04% (95% CI 0.01-0.20%). Based on these risks, if 414 women with a history of cesarean delivery were given misoprostol for second-trimester abortion, one would experience uterine rupture.
Conclusion:
The risk of uterine rupture among women with a prior cesarean delivery undergoing second-trimester abortion using misoprostol is less than 0.3%. This may be acceptable to both patients and providers.

Related Concept Videos
 01:20
Drugs for Peptic Ulcer Disease: Prostaglandin Analogs as Mucosal Protective Agents
Non-steroidal anti-inflammatory drugs (NSAIDs) can induce peptic ulcers by inhibiting cyclooxygenase, decreasing...
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:21
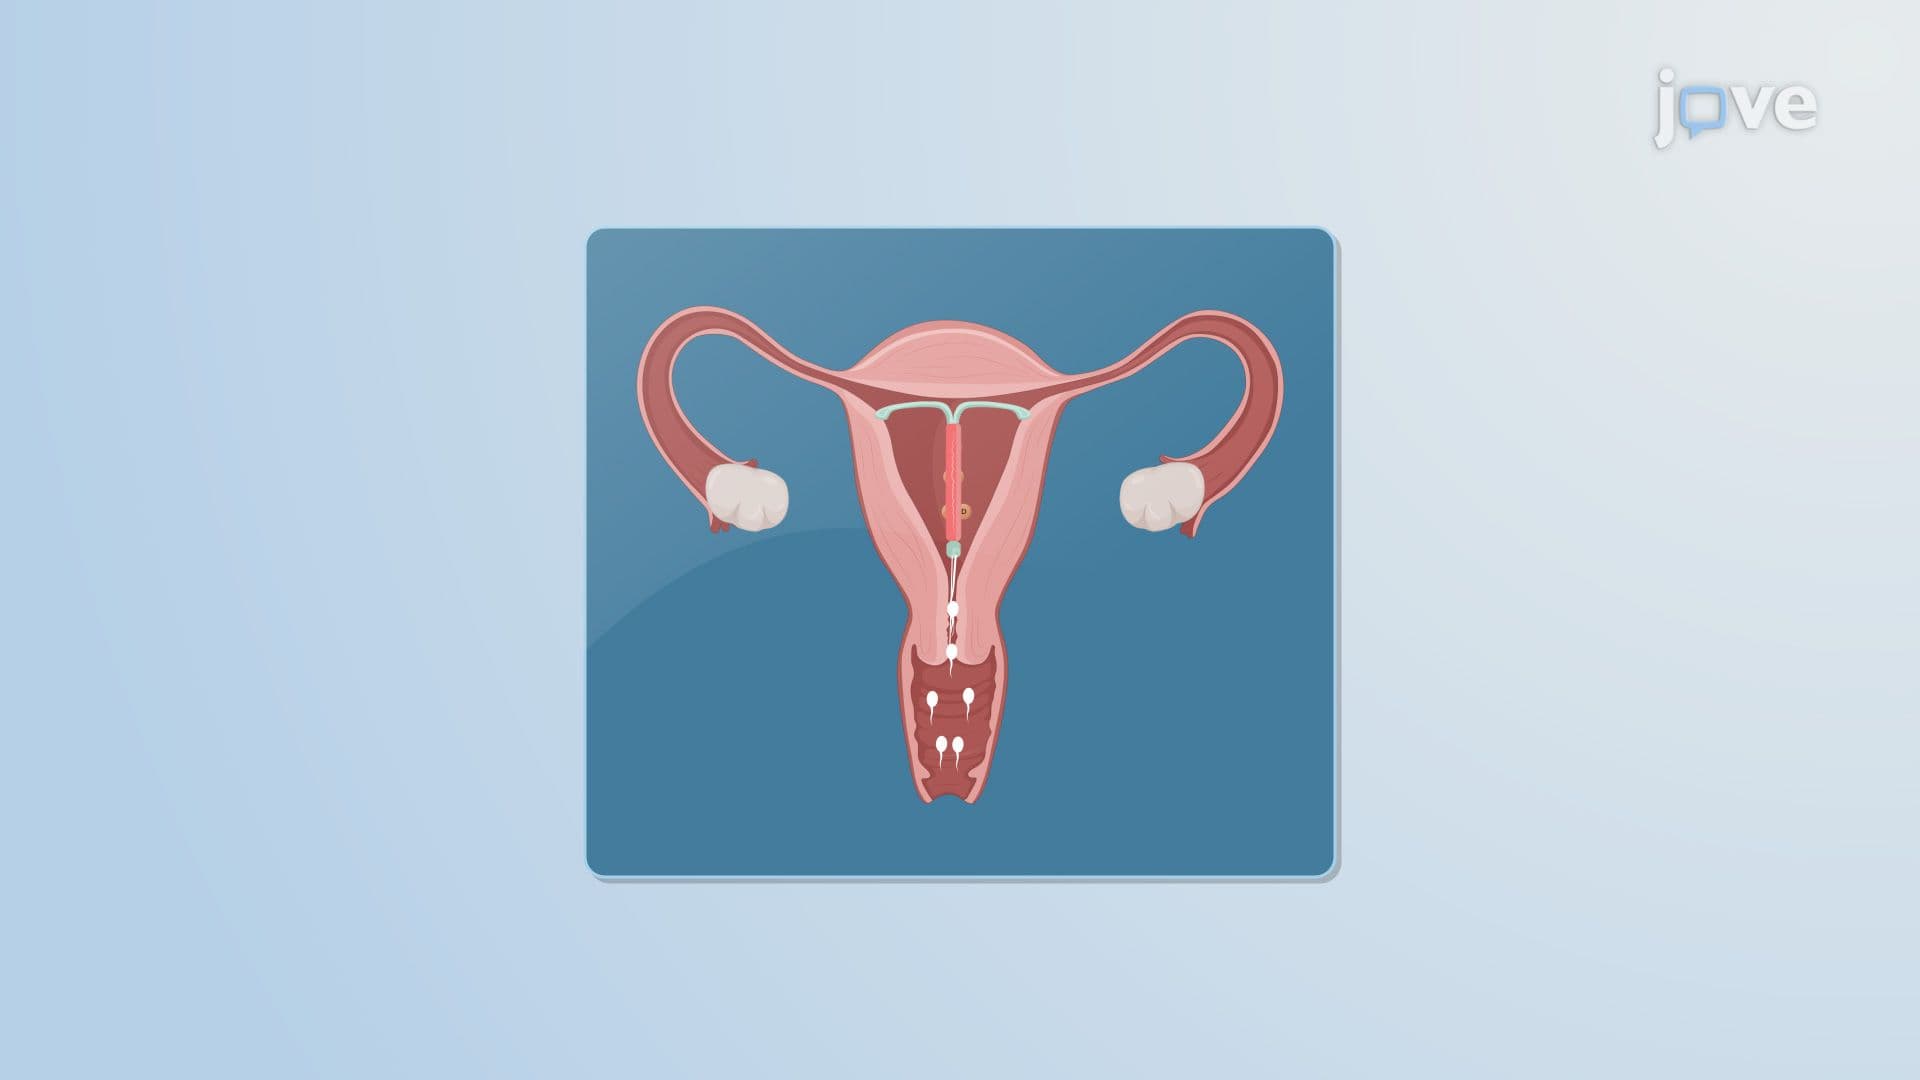
Intrauterine Drug Delivery Systems
 01:07
Intestinal Obstruction II: Pathophysiology