Related Experiment Video
Updated: Jun 23, 2026
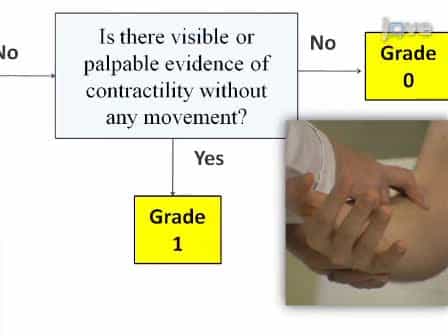

Manual Muscle Testing: A Method of Measuring Extremity Muscle Strength Applied to Critically Ill Patients
Published on: April 12, 2011
Signs of critical illness polyneuropathy and myopathy can be seen early in the ICU course
K Ahlbeck1, K Fredriksson, O Rooyackers
1Department of Physiology and Pharmacology, Section for Anaesthesiology and Intensive Care Medicine, Karolinska Institutet and Karolinska University Hospital, Stockholm, Sweden. karsten.ahlbeck@karolinska.se

Insights
Critical illness polyneuropathy and myopathy (CIPNM) develops early in intensive care units, particularly in patients with sepsis and steroid treatment. Changes in nerve and muscle function appear at different times during mechanical ventilation.
Area of Science:
- Intensive care medicine
- Neurology
- Mitochondrial biology
Background:
- Critical illness polyneuropathy and myopathy (CIPNM) is a common ICU complication.
- CIPNM can prolong hospital stays and increase costs.
- Predisposing factors and temporal patterns of CIPNM are not well understood.
Purpose of the Study:
- To investigate the time course of CIPNM in critically ill patients.
- To comprehensively describe changes in neurophysiology, histology, and mitochondrial function.
- To identify factors associated with CIPNM development.
Main Methods:
- Studied 10 ICU patients requiring mechanical ventilation.
- Performed serial neurophysiological, histological, and biochemical analyses over 28 days.
- Assessed mitochondrial content, respiratory enzymes, and oxidative stress markers.
Main Results:
- All patients showed neurophysiological abnormalities; 5/5 with sepsis and steroid treatment met CIPNM criteria.
- CIPNM did not impact patient outcomes.
- Nerve changes occurred early, while muscle changes appeared later.
- Decreased citrate synthase and increased mitochondrial superoxide dismutase were observed.
Conclusions:
- CIPNM signs are detectable early in the ICU course.
- Sepsis and corticosteroid treatment increase the likelihood of CIPNM.
- Understanding CIPNM's temporal pattern aids early detection and management.
Background:
Critical illness polyneuropathy and myopathy (CIPNM) is recognized as a common condition that develops in the intensive care unit (ICU). It may lead to a prolonged hospital stay with subsequent increased ICU and hospital costs. Knowledge of predisposing factors is insufficient and the temporal pattern of CIPNM has not been well described earlier. This study investigated patients with critical illness in need of prolonged mechanical ventilation, describing comprehensively the time course of changes in muscle and nerve neurophysiology, histology and mitochondrial oxidative function.
Methods:
Ten intensive care patients were investigated 4, 14 and 28 days after the start of mechanical ventilation. Laboratory tests, neurophysiological examination, muscle biopsies and clinical examinations were performed. Neurophysiological criteria for CIPNM were noted and measurements for mitochondrial content, mitochondrial respiratory enzymes and markers of oxidative stress were performed.
Results:
While all patients showed pathologic changes in neurophysiologic measurements, only patients with sepsis and steroid treatment (5/5) fulfilled the CIPNM criteria. The presence of CIPNM did not affect the outcome, and the temporal pattern of CIPNM was not uniform. All CIP changes occurred early in ICU care, while myopathy changes appeared somewhat later. Citrate synthase was decreased between days 4 and 14, and mitochondrial superoxide dismutase was increased.
Conclusion:
With comprehensive examination over time, signs of CIPNM can be seen early in ICU course, and appear more likely to occur in patients with sepsis and corticosteroid treatment.
Related Concept Videos
 01:28
Diphtheria
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:25
Endocarditis II: Clinical Features of Infective Endocarditis
 01:19
Type I Diabetes III: Clinical Manifestations
 01:27
Myocarditis II: Clinical Features and Diagnostic Tests
 01:29
Acute Kidney Injury III: Clinical Manifestations