Related Experiment Video
Updated: Jun 23, 2026

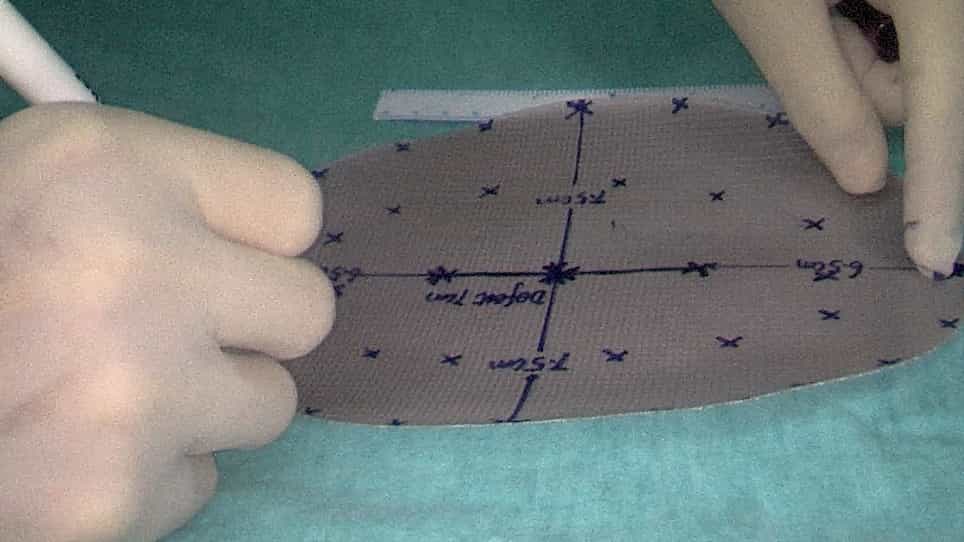
Laparoscopic Repair of Para-Esophageal Hernia Using Absorbable Biosynthetic Mesh
Published on: September 11, 2021
Laparoscopic inguinal hernia repair: audit of our experience with laparoscopic trans-abdominal pro-peritoneal repair
Francesco Tatulli1, Giuseppe Chetta, Antonio Caputi
1UOC di Chirurgia Generale, Ospedale V Emanuele II, A.S.L. BAT, Bisceglie, Bari.

Several laparoscopic procedures have successfully passed the stage of feasibility assessment and are currently under scrutiny with regard to indications. Laparoscopic repair of inguinal hernia is a typical example of such investigations, being mostly recommended only for bilateral and recurrent hernias at the moment. We performed an audit of our experience with 100 consecutive laparoscopic trans-abdominal pro-peritoneal repairs (T.A.P.P.) on 54 patients, mostly presenting with bilateral inguinal hernias over a period of 3 years. Operative time averaged 102 minutes for unilateral repairs and 123 minutes for bilateral repairs. When other procedures were added or a recurrent hernia was treated, operative time for bilateral repairs increased to 142 and 156 minutes, respectively. Prolene mesh size was 10 x 12 cm in most patients. Hospital stay averaged 3.7 days overall, averaging 3.3 and 3 days for bilateral and unilateral repairs. Added procedures lengthened the hospital stay to 4 and 10.6 days, respectively. In 85% of patients gas was passed on postoperative day 1. Postoperative morbidity consisted in 2 major (sizable haematoma) and 20 minor complications. Pain as estimated by a VAS scale was mild to low. Follow-up was obtained in 85% of patients and revealed only 2 recurrences, 1 incisional hernia, 1 persistent swelling from a spiral tack, and 1 post-discharge bronchitis. In conclusion we believe laparoscopic inguinal hernia repair is the method of choice for treatment of bilateral and recurrent hernias and in selected cases of unilateral hernias.
Several laparoscopic procedures have successfully passed the stage of feasibility assessment and are currently under scrutiny with regard to indications. Laparoscopic repair of inguinal hernia is a typical example of such investigations, being mostly recommended only for bilateral and recurrent hernias at the moment. We performed an audit of our experience with 100 consecutive laparoscopic trans-abdominal pro-peritoneal repairs (T.A.P.P.) on 54 patients, mostly presenting with bilateral inguinal hernias over a period of 3 years. Operative time averaged 102 minutes for unilateral repairs and 123 minutes for bilateral repairs. When other procedures were added or a recurrent hernia was treated, operative time for bilateral repairs increased to 142 and 156 minutes, respectively. Prolene mesh size was 10 x 12 cm in most patients. Hospital stay averaged 3.7 days overall, averaging 3.3 and 3 days for bilateral and unilateral repairs. Added procedures lengthened the hospital stay to 4 and 10.6 days, respectively. In 85% of patients gas was passed on postoperative day 1. Postoperative morbidity consisted in 2 major (sizable haematoma) and 20 minor complications. Pain as estimated by a VAS scale was mild to low. Follow-up was obtained in 85% of patients and revealed only 2 recurrences, 1 incisional hernia, 1 persistent swelling from a spiral tack, and 1 post-discharge bronchitis. In conclusion we believe laparoscopic inguinal hernia repair is the method of choice for treatment of bilateral and recurrent hernias and in selected cases of unilateral hernias.