Related Experiment Video
Updated: Jun 23, 2026


Multiple Intravenous Bolus Dosing and Invasive Hemodynamic Assessment in a Hypoxia-Induced Mouse Pulmonary Artery Hypertension Model
Published on: November 11, 2022
Meropenem dosing in critically ill patients with sepsis and without renal dysfunction: intermittent bolus versus
Jason A Roberts1, Carl M J Kirkpatrick, Michael S Roberts
1Burns, Trauma and Critical Care Research Centre, The University of Queensland, Brisbane, Australia. j.roberts2@uq.edu.au

Objectives:
To compare the plasma and subcutaneous tissue concentration-time profiles of meropenem administered by intermittent bolus dosing or continuous infusion to critically ill patients with sepsis and without renal dysfunction, and to use population pharmacokinetic modelling and Monte Carlo simulations to assess the cumulative fraction of response (CFR) against Gram-negative pathogens likely to be encountered in critical care units.
Patients And Methods:
We randomized 10 patients with sepsis to receive meropenem by intermittent bolus administration (n = 5; 1 g 8 hourly) or an equal dose administered by continuous infusion (n = 5). Serial subcutaneous tissue concentrations were determined using microdialysis and compared with plasma data for first-dose and steady-state pharmacokinetics. Population pharmacokinetic modelling of plasma data and Monte Carlo simulations were then undertaken with NONMEM.
Results:
It was found that continuous infusion maintains higher median trough concentrations, in both plasma (intermittent bolus 0 versus infusion 7 mg/L) and subcutaneous tissue (0 versus 4 mg/L). All simulated intermittent bolus, extended and continuous infusion dosing achieved 100% of pharmacodynamic targets against most Gram-negative pathogens. Superior obtainment of pharmacodynamic targets was achieved using administration by extended or continuous infusion against less susceptible Pseudomonas aeruginosa and Acinetobacter species.
Conclusions:
This is the first study to compare the relative concentration-time data of bolus and continuous administration of meropenem at the subcutaneous tissue and plasma levels. We found that the administration of meropenem by continuous infusion maintains higher concentrations in subcutaneous tissue and plasma than by intermittent bolus dosing. Administration by extended or continuous infusion will achieve superior CFR against less-susceptible organisms in patients without renal dysfunction.
Related Concept Videos
 01:24
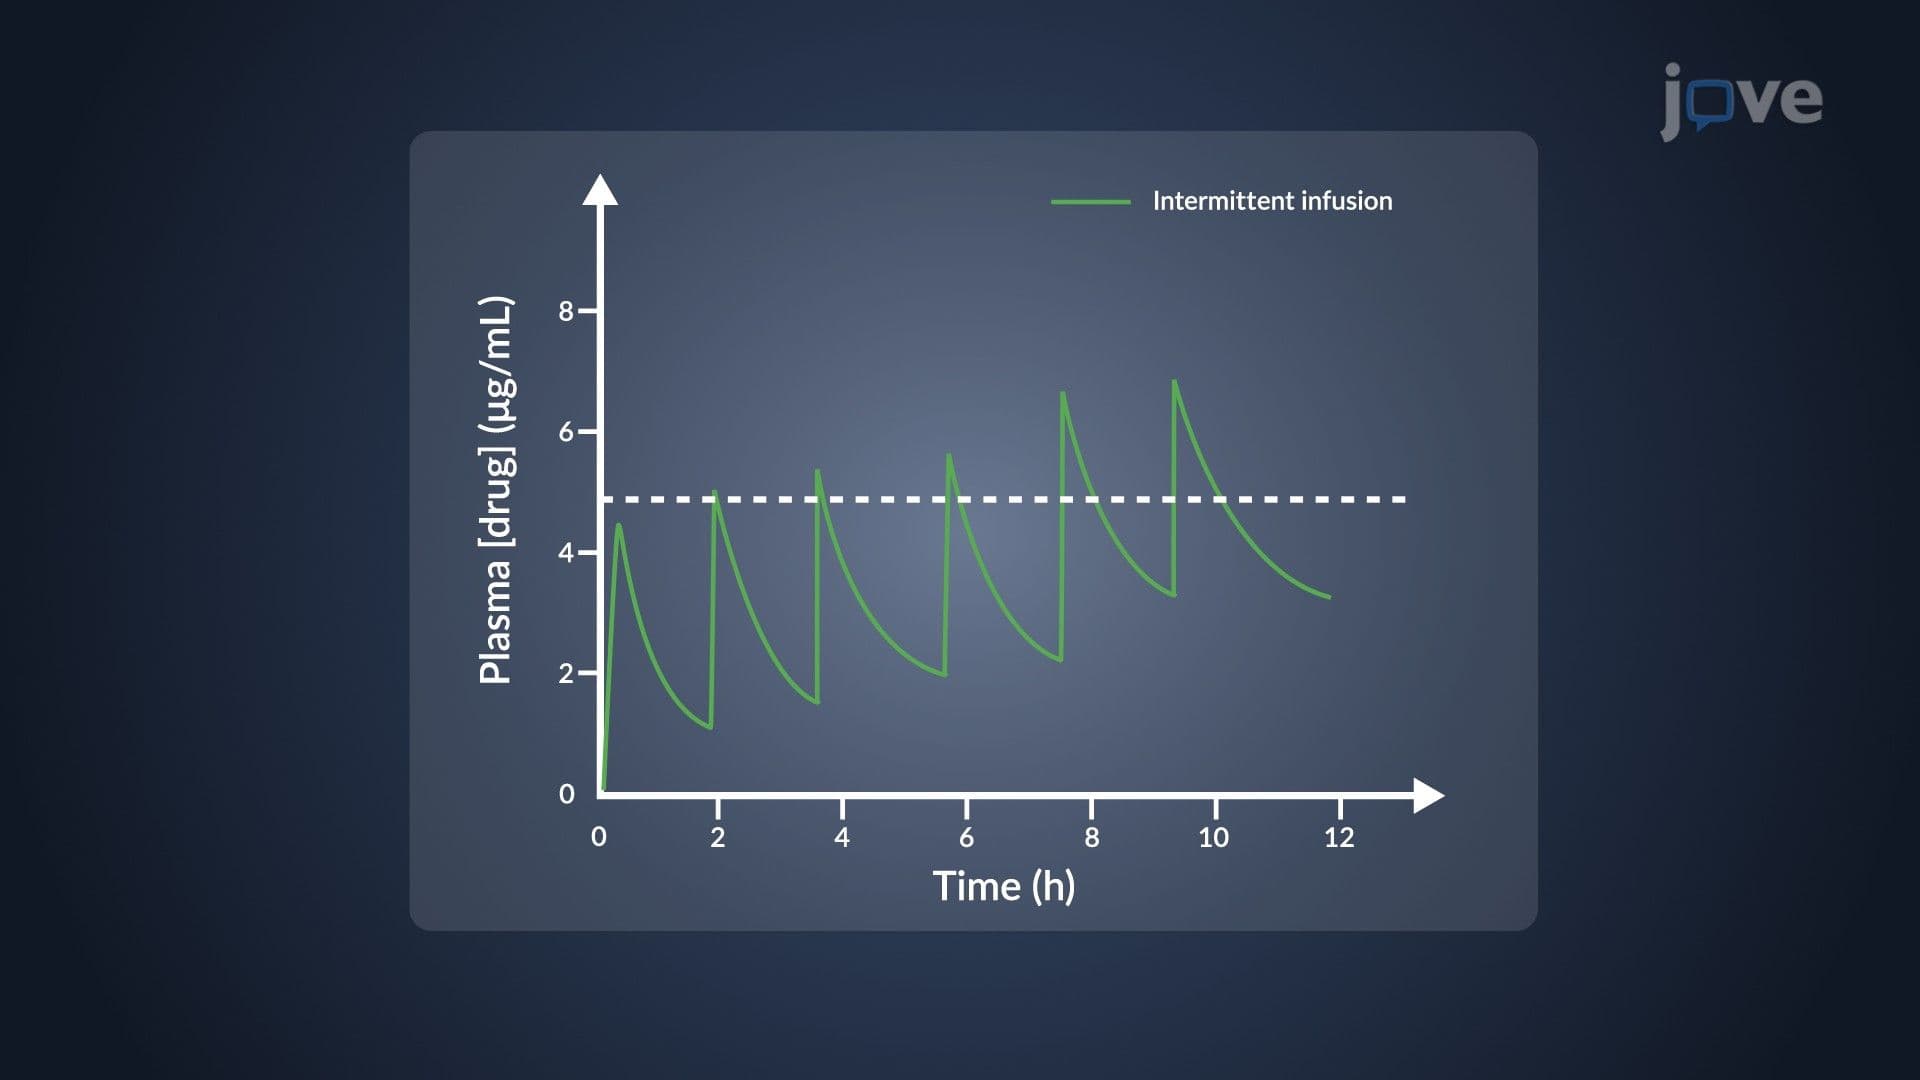
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:15
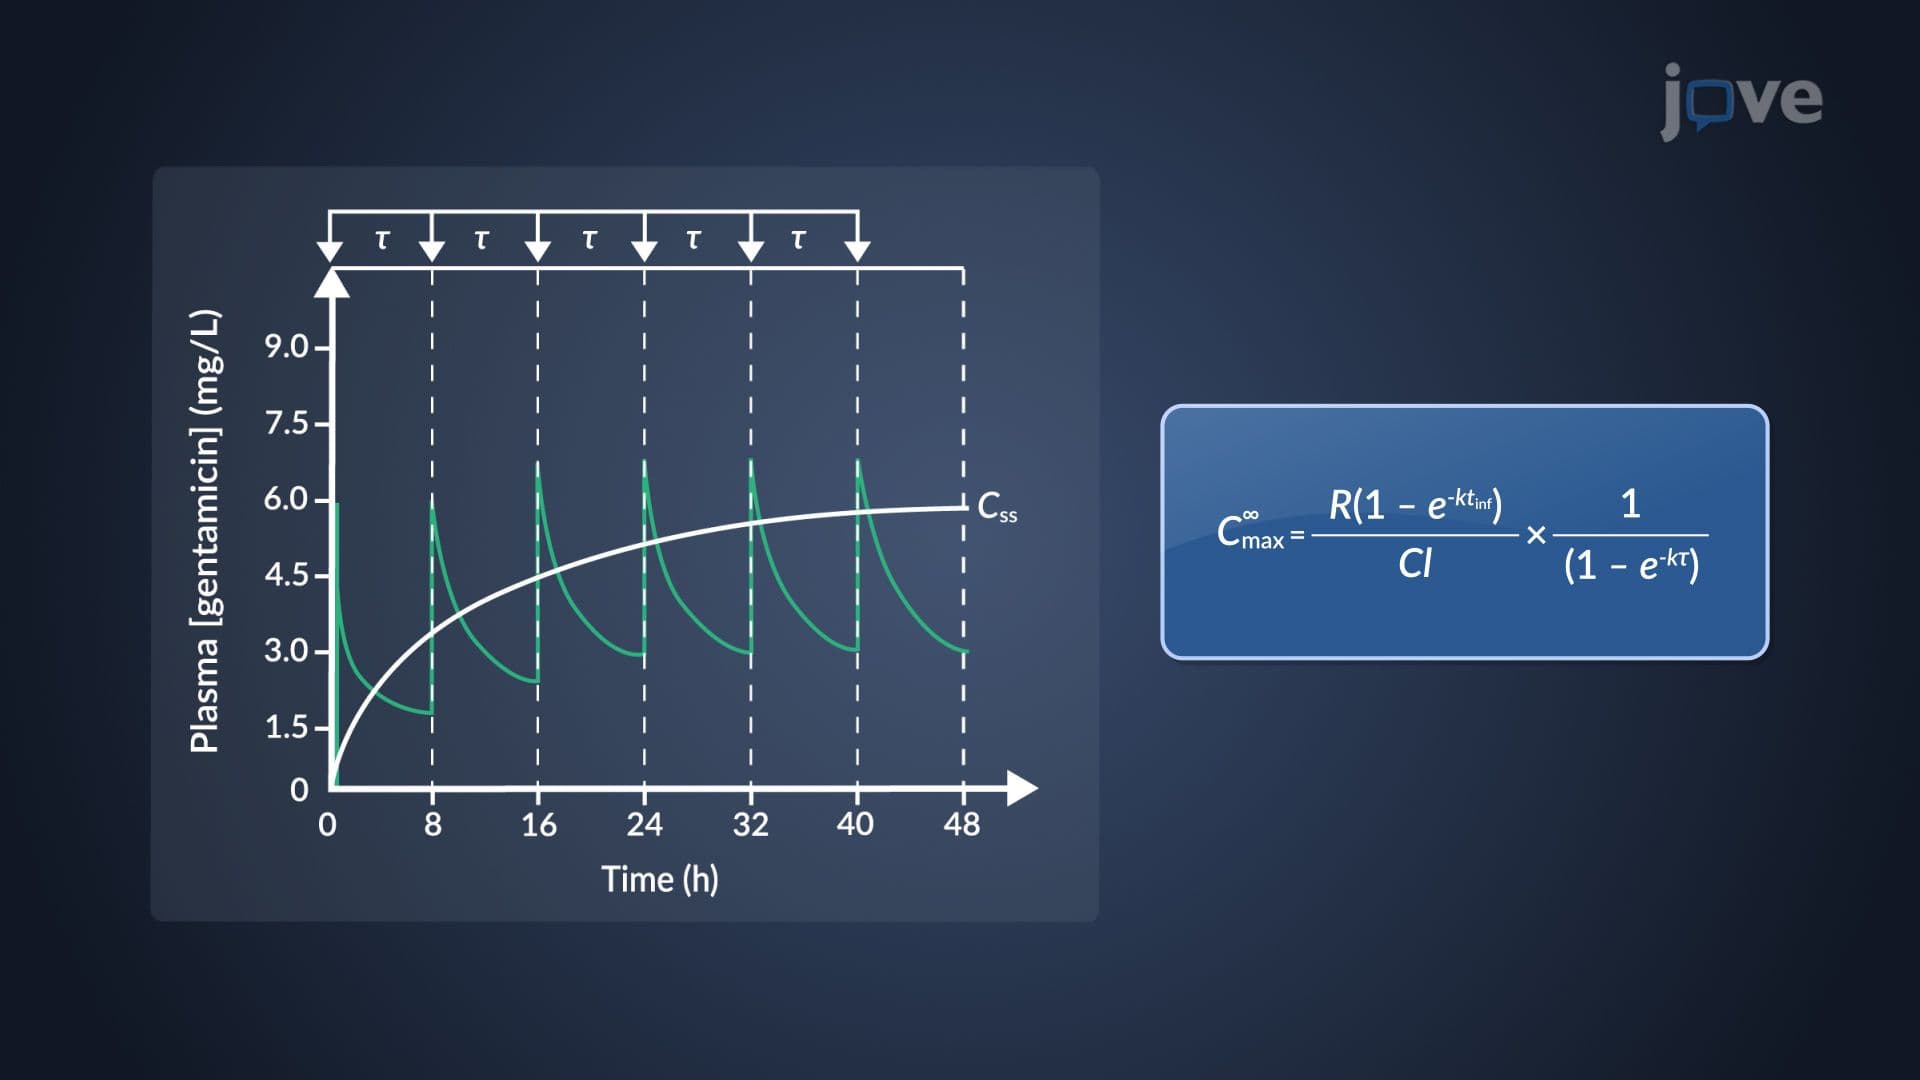
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:19
One-Compartment Open Model for IV Bolus Administration: General Considerations
The drug's presence in the body is defined by an equation representing the difference between the rates of drug entry and exit. Key parameters—elimination rate constant, half-life,...
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:15
Impact of Pharmacokinetic–Pharmacodynamic Models: Regulatory Decisions