Related Experiment Video
Updated: Jun 23, 2026
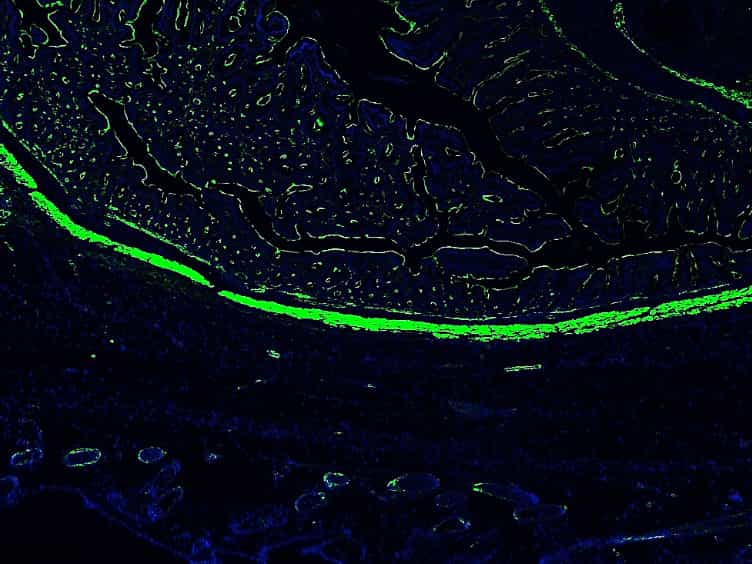

Creation of Abdominal Adhesions in Mice
Published on: August 27, 2016
[New aspects of pathogenesis of adhesive process in the abdominal cavity]

Insights
Polyenzyme therapy significantly reduced intestinal obstruction in children and prevented adhesions in rats. This approach down-regulates inflammatory responses by modulating key growth factors, offering a promising treatment for post-surgical adhesions.
Area of Science:
- Surgical pathology
- Gastroenterology
- Immunology
Background:
- Abdominal adhesions are a primary cause of morbidity and mortality following abdominal surgery.
- Adhesive intestinal obstruction presents a significant clinical challenge, particularly in pediatric patients.
Purpose of the Study:
- To evaluate the efficacy of polyenzyme therapy in managing acute adhesive intestinal obstruction.
- To investigate the impact of polyenzyme preparations on the development of postoperative abdominal adhesions in a rat model.
Main Methods:
- A clinical study involving 126 children with acute adhesive intestinal obstruction, divided into polyenzyme and monoenzyme groups.
- An experimental study with 70 adult rats, comparing a polyenzyme preparation group with a control group regarding cecal adhesions.
- Immunohistochemical detection of vascular endothelial growth factor (VEGF), fibroblast growth factor (FGF), and Laminin in rats.
Main Results:
- The polyenzyme group showed a lower incidence of intestinal obstruction (1 case) compared to the monoenzyme group (4 cases).
- Rats receiving polyenzyme preparation exhibited significantly fewer cecal adhesions than the control group (Chi-square test = 23.1, p = 0.001).
- Polyenzyme therapy normalized levels of angiogenesis factors (VEGF, FGF, Laminin) and down-regulated inflammatory responses mediated by T-lymphocytes and macrophages.
Conclusions:
- Polyenzyme therapy demonstrates significant therapeutic potential in reducing postoperative abdominal adhesions and treating adhesive intestinal obstruction.
- The mechanism involves modulating the expression of key growth factors and inflammatory mediators, thereby mitigating the adhesion cascade.
Abstract:
Adhesive process in the abdominal cavity is the leading cause of morbidity and mortality in abdominal surgery. The clinical investigation included 126 children with acute adhesive intestinal obstruction. All patients were divided into two groups: polyenzyme and monoenzyme groups. In the polyenzyme group there was one case of intestinal obstruction. In the monoenzyme group there were 4 children with intestinal obstruction. The experiment included 70 adult rats divided in two equal groups: the main and control groups. The main group animals were given a polyenzyme preparation. The control group had a high incidence of cecal adhesions, which was significantly higher than the number of adhesions in the main group (Chi-square test = 23.1, df=2, p = 0.001). Proteolytic enzymes induce cells to express, de novo, the vascular endothelial growth factor, fibroblast growth factor and Laminin. As a consequence of these effects, activation of T-lymphocytes and macrophages mediating the inflammatory response will be down-regulated. It was found that the levels of VEGF, FGF and Laminin in the abdominal cavity, detected by immunohistochemistry, were different in the rats having high level and having no postoperative abdominal adhesion. The level of angiogenesis factors was also rapidly normalized by means of polyenzyme therapy.

Related Concept Videos
 01:24
Adherens Junctions
Adherens Junctions are Dynamic
The endothelial cells...
 01:19
Ascites
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:19
Appendicitis
 01:07
Intestinal Obstruction II: Pathophysiology
 01:21
Acute Pancreatitis II: Pathophysiology