Related Experiment Video
Updated: Jun 23, 2026


Surgically Induced Cardiac Volume Overload by Aortic Regurgitation in Mouse
Published on: August 30, 2022
Left ventricular outflow tract gradient provoked by upright position or exercise in treated patients with
Pawel Petkow Dimitrow1, Maria Bober, Joanna Michałowska
12nd Department of Cardiology, CMUJ, Kracow, Poland. dimitrow@mp.pl

Insights
In treated hypertrophic cardiomyopathy (HCM) patients without resting obstruction, changing to an upright position induced a left ventricular outflow tract (LVOT) gradient in 21.6%, and exercise in 34.5%. Minimal septal-mitral distance may identify patients with inducible obstruction.
Area of Science:
- Cardiology
- Echocardiography
- Hypertrophic Cardiomyopathy
Background:
- Hypertrophic cardiomyopathy (HCM) is a genetic heart condition characterized by thickening of the heart muscle.
- Left ventricular outflow tract (LVOT) obstruction can develop in HCM patients, even if not present at rest.
- Assessing the inducibility of LVOT gradient is crucial for risk stratification and management.
Purpose of the Study:
- To evaluate the inducibility of LVOT gradient in treated HCM patients without resting obstruction.
- To determine the role of postural changes (supine to upright) and treadmill exercise in provoking LVOT gradient.
- To identify echocardiographic predictors of inducible LVOT obstruction.
Main Methods:
- 37 treated HCM patients with resting LVOT gradient <30 mmHg were studied.
- LVOT gradient was assessed in supine, upright, and during treadmill exercise.
- Systolic mitral-septal distance was measured to assess LVOT narrowing.
Main Results:
- Upright position induced an LVOT gradient (>=30 mmHg) in 8 of 37 patients (21.6%).
- Treadmill exercise induced a significant LVOT gradient in 10 of the remaining 29 patients (34.5%).
- Lower systolic mitral-septal distance was associated with inducible LVOT gradient.
Conclusions:
- LVOT gradient is inducible by postural changes and exercise in a significant proportion of treated, nonobstructive HCM patients.
- Upright position and moderate exercise can provoke LVOT obstruction.
- Minimal systolic mitral-septal distance is a potential marker for identifying patients with inducible LVOT obstruction.
Objectives:
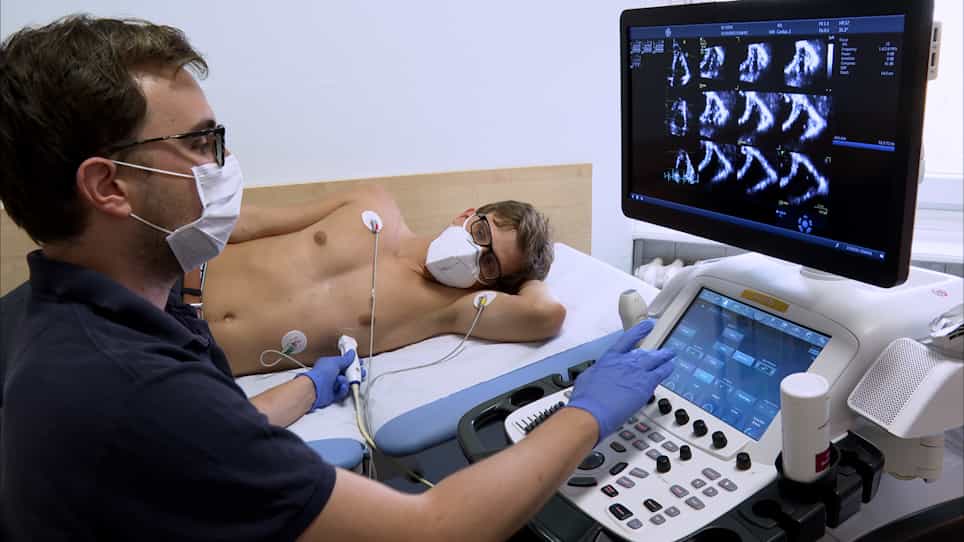
The aim of the study was to assess inducibility of left ventricular outflow tract (LVOT) gradient by change of position from supine to upright and by treadmill exercise in treated patients with hypertrophic cardiomyopathy (HCM) without obstruction at rest.
Methods:
We studied 37 treated HCM patients (21 men and 16 women, mean age 44 +/- 12 years) with LVOT gradient <30 mmHg at rest in supine position. The patients were then placed in upright position and the gradient was reexamined. The patients who developed LVOT gradient >or= 30 mmHg during this maneuver were not exercised, whereas the remaining patients (nonobstructive in orthostatic position) performed moderate-intensity exercise on a treadmill, with continuous monitoring of the LVOT gradient. For comparison with resting measurements, gradients at peak exercise (in upright position) and at recovery (in supine position) were used. The resting minimal distance between the mitral valve and ventricular septum at systole was used to assess the degree of narrowing of LVOT.
Results:
The orthostatic position provoked LVOT gradient >or= 30 mmHg in 8 of 37 patients. At peak exercise, 10 of the remaining 29 patients developed significant LVOT gradient. At recovery in supine position, this significant gradient disappeared in 6 of 10 patients, despite only a short delay in measurement. Of resting echocardiographic parameters, only systolic mitral-septal distance differentiated between the provocable and nonprovocable subgroups. Patients with provocable gradient (either by changing position or by exercise) presented with lower values of this parameter than the nonprovocable subgroup.
Conclusions:
In nonobstructive HCM patients under treatment, the LVOT gradient was inducible by upright position in 21.6% and by upright moderate exercise in 34.5%. The minimal septal-mitral distance may be useful to identify patients with provocable obstruction.
Related Concept Videos
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:29
Heart Failure II: Pathophysiology
 01:22
Mitral Stenosis I: Introduction
 01:20
Mitral Regurgitation I: Introduction
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send blood...
 01:29
Cardiomyopathy V: Interprofessional Care