Related Experiment Video
Updated: Jun 23, 2026


Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Congenital dislocated spine: implications for orthopaedic management
Elke Viehweger1, Marie-Christine Giacomelli, Yann Glard
1Department of Pediatric Orthopaedics, Children's Hospital TIMONE, Marseille, France. elke.viehweger@mail.ap-hm.fr

Background:
Congenital dislocation of the spine (CDS) is a rare malformation due to a developmental failure of the spine and the spinal cord at a single spinal level. New embryological and physiopathological findings define CDS as an autonomous entity compared with multilevel pathologies. The severity of CDS neurological outcome requires its treatment by experienced pediatric spine surgeons in a pediatric specialty hospital. This report aims to propose a comprehensive orthopaedic management strategy and operative technique of CDS in 6 new patients.
Methods:
The records of patients treated at our institution for congenital anomalies of the spine were reviewed in a retrospective study. Inclusion criteria were extracted from the actual context of new embryologic theories: single level involvement; sudden mainly sagittal vertebral displacement with anterior translation of the entire cranial vertebral column on the caudal vertebrae ("step-off sign"); underlying spinal malformation at a clearly distinct level; spinal cord intact both cranial and caudal to the malformation; possibility of malformed aspect of the 2 involved vertebrae. Demographic data, family, and clinical history were collected. Complete set of plain radiographs and modern imaging computed tomography and magnetic resonance imaging were analyzed.
Results:
Six children treated between 1993 and 2007 have been classified as CDS. The mean follow-up to date of the 4 patients alive after the last corrective surgery is 9.8 years (range, 1-14.6 years). All patients alive have at follow-up solid stable fusion and no progression of spinal deformity. Two of the patients are independent walkers.
Conclusions:
The neurological involvement of CDS if present initially is the consequence of an associated spinal cord malformation without mechanical factor. Adaptation of the therapeutic strategy may avoid secondary neurological damage. Parents should be counseled as soon as the diagnosis is made, the obstetrical and postnatal orthopaedic management has to be adapted. Stabilization of the spine including very early cast immobilization and an early instrumented decompression-stabilization with circumferential fusion in 1 stage is required.
Related Concept Videos
 01:29
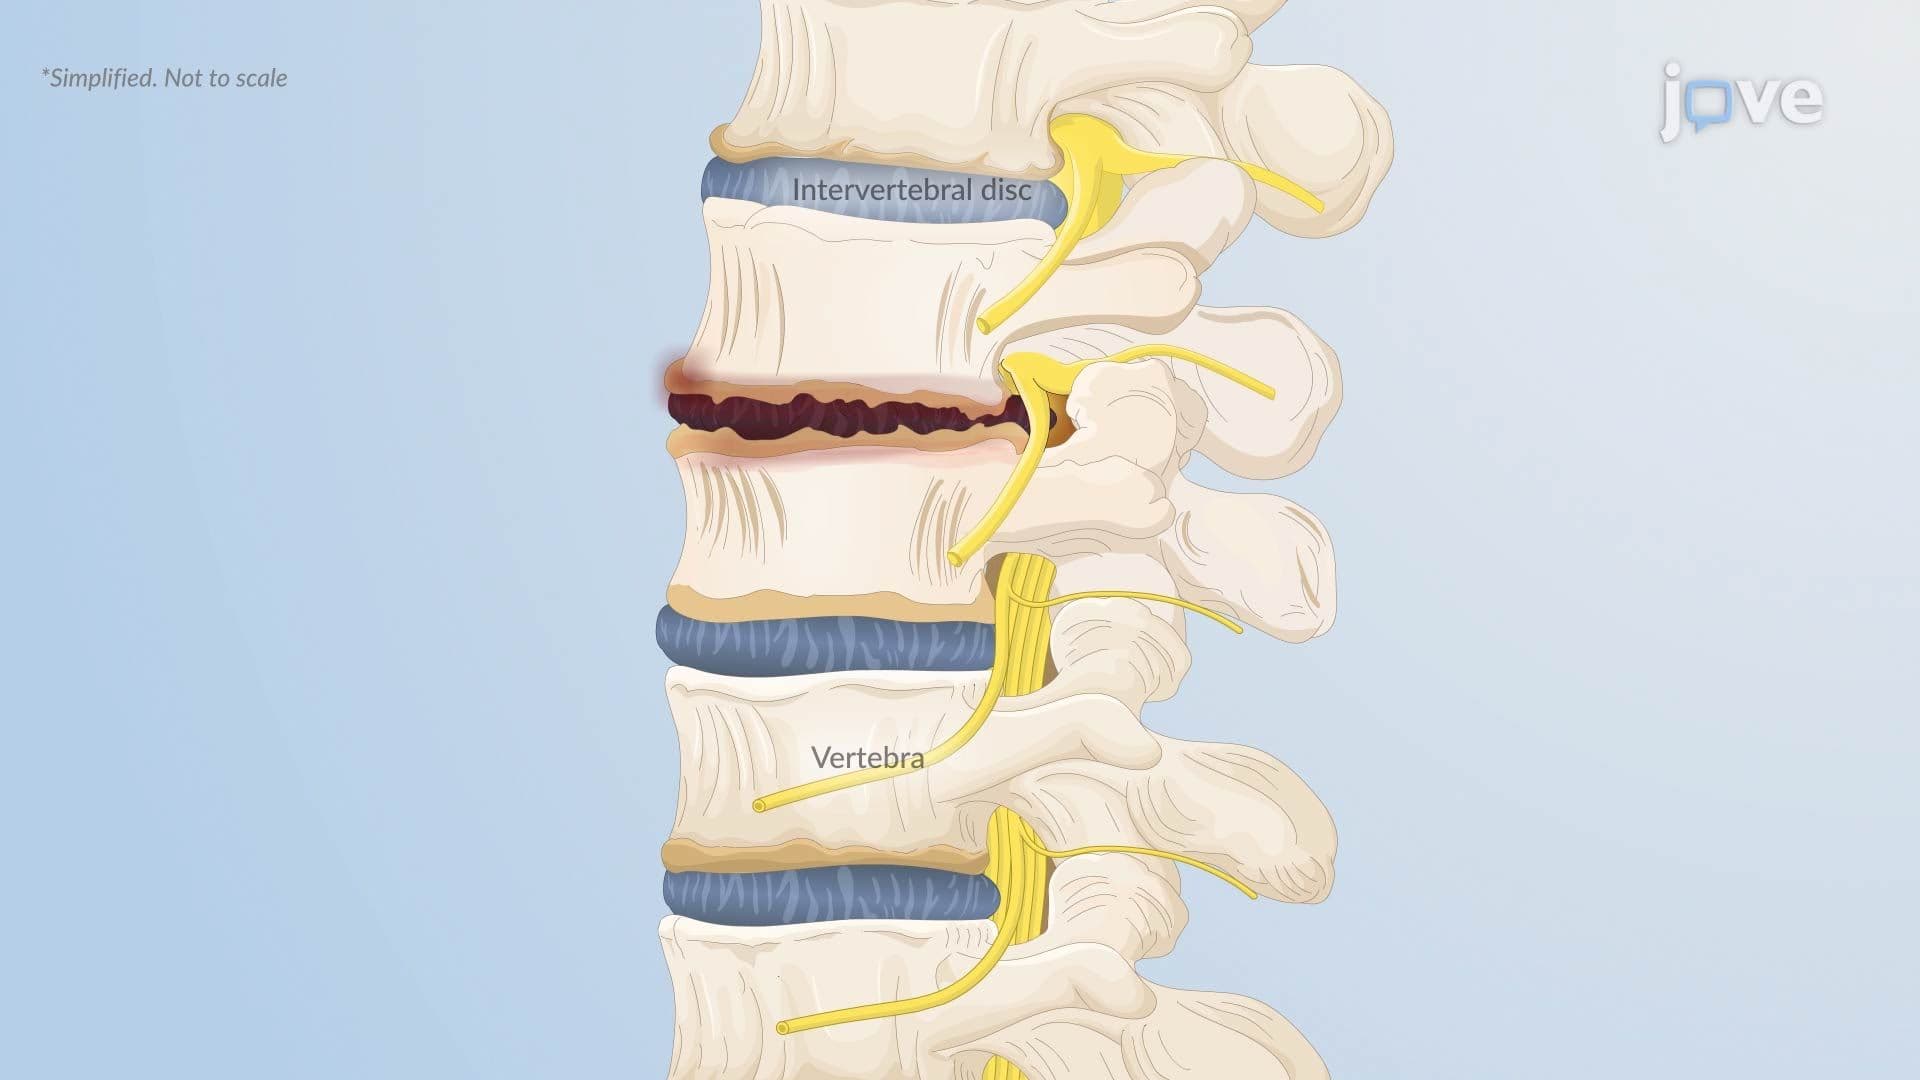
Herniated Intervertebral Disc l: Introduction
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the procedure...
 01:16
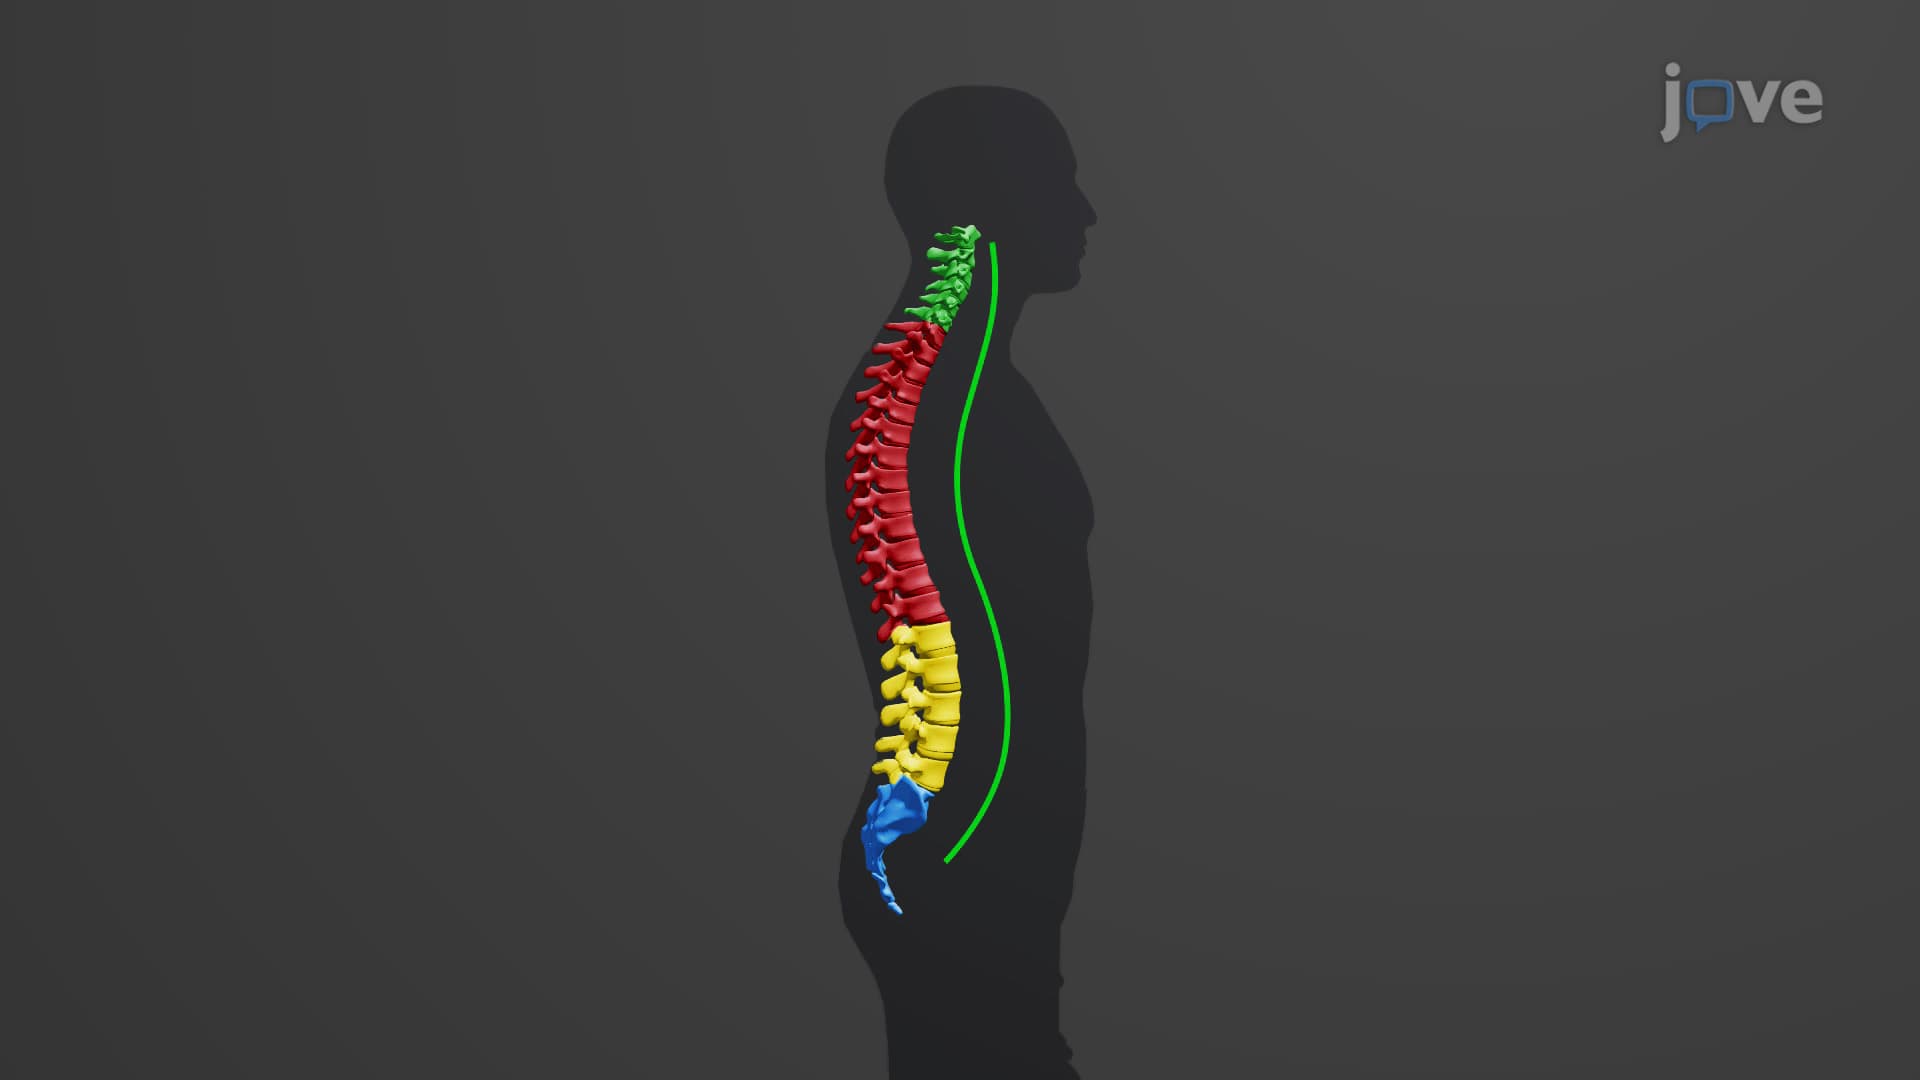
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form the...