Related Experiment Video
Updated: Jun 22, 2026
Exploring Independent Effects of Follicle-Stimulating Hormone In Vivo in a Mouse Model
Published on: August 11, 2023
Physiologic and nonphysiologic effects of exogenous prostaglandin F2alpha on reproductive hormones in mares
O J Ginther1, M A R Siddiqui, M A Beg
1Eutheria Foundation, Cross Plains, WI 53528, USA; Pathobiological Sciences, University of Wisconsin, Madison, WI 53706, USA. ginther@svm.vetmed.wisc.edu

Abstract:
Responses to intravenous treatment of mares with prostaglandin F2alpha (PGF) 8 d after ovulation were studied in three groups (n=4/group): control (no treatment), bolus (single treatment with 2.5 mg PGF), and infusion (0.1 mg PGF during 2 h). Infusion resulted in a 13,14-dihydro-15-keto-PGF2alpha (PGFM) concentration (559+/-44 pg/mL) that was not different from the mean concentration for the major portion of a natural PGFM pulse associated with luteolysis (569+/-45 pg/mL; n=5). Progesterone in the bolus group increased (P<0.03) between 0 (17.8+/-3.5 ng/mL) and 2 min (25.3+/-4.8 ng/mL), peaked at 10 min (28.5+/-4.6 ng/mL), and then decreased. In the infusion group, progesterone decreased (P<0.05) during 1 min (17.2+/-1.3 ng/mL) to 15 min (13.5+/-1.5 ng/mL) after the beginning of infusion and decreased (P<0.05) similarly to the bolus group during 2 to 12 h; concentrations were lower (P<0.05) at each hour than in controls. Interval between ovulations was shorter (P<0.05) in the bolus (19.3+/-2.0 d) and infusion (18.8+/-2.1 d) groups than in controls (24.3+/-1.3 d). Concentrations of follicle-stimulating hormone (FSH), luteinizing hormone (LH), and cortisol increased (P<0.05) within 10 min in the bolus group but did not change in the infusion group. Results supported the hypothesis that increases in progesterone, FSH, LH, and cortisol after a bolus luteolytic PGF treatment are nonphysiologic. Past conclusions on the nature of the luteolytic mechanism are problematic if based on responses to treatment with a single luteolytic bolus of PGF.
Related Concept Videos
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:20
Drugs for Peptic Ulcer Disease: Prostaglandin Analogs as Mucosal Protective Agents
Non-steroidal anti-inflammatory drugs (NSAIDs) can induce peptic ulcers by inhibiting cyclooxygenase, decreasing...
 01:24
Gonadal and Placental Hormones
In males, testosterone is the primary gonadal androgen. It plays a central role in the maturation of male reproductive organs — the penis and testes. Additionally, testosterone is instrumental in the development of secondary sexual characteristics — a deep voice as well as facial and pubic hair growth — and...
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
 01:22
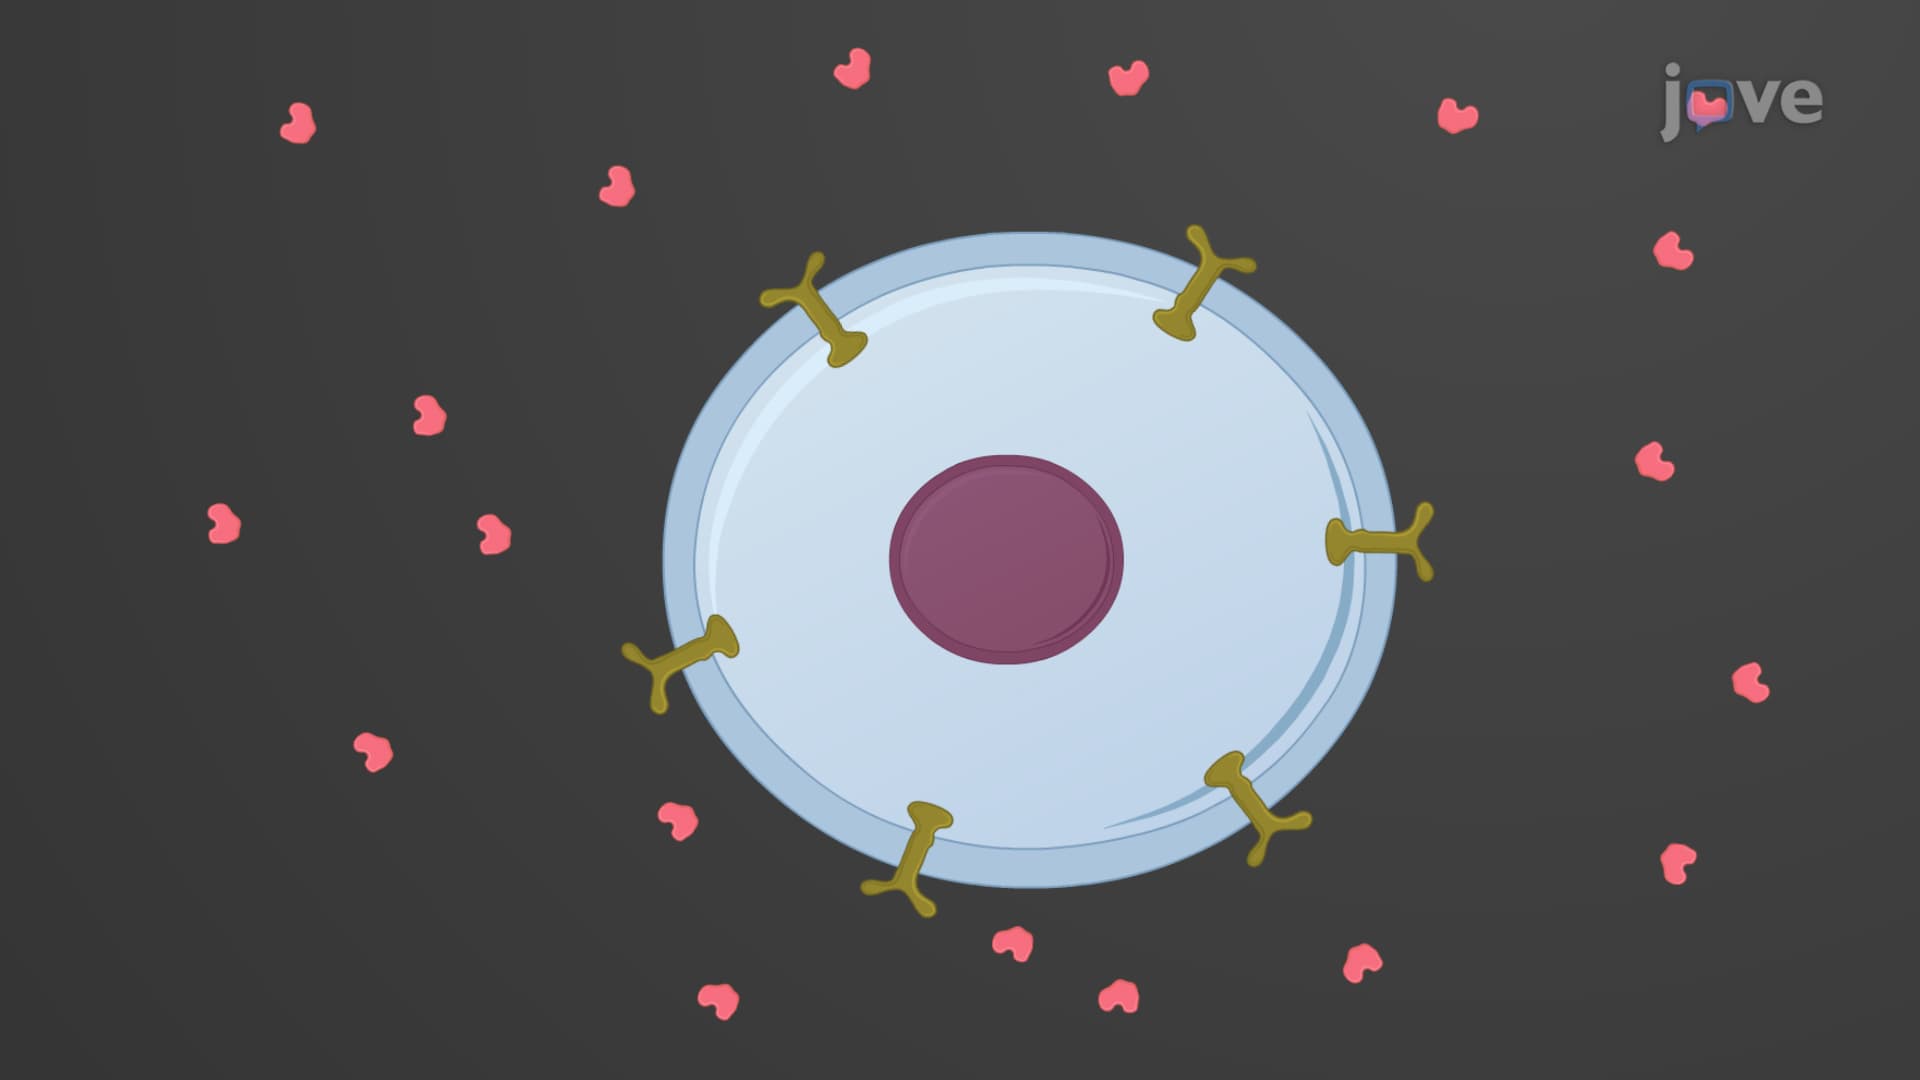
Target Cell Response to Hormones
Notably, the cellular response can be regulated by altering the number of receptors expressed in the cell. For example, prolonged exposure to elevated hormone levels results in a gradual decline or down-regulation in the number of receptors for that specific hormone on the cell surface. Conversely, in response to low hormone levels, cells may use up-regulation, producing an...
 01:27
Ovarian Cycle