Related Experiment Video
Updated: Jun 22, 2026


Guidelines for Elective Pediatric Fiberoptic Intubation
Published on: January 17, 2011
[Simplified method to maintain propofol blood concentration in an approximately constant level associated to nitrous
Pedro Thadeu Galvão Vianna1, Elizabeth Pricoli Vilela, Francisco Carlos Obata Cordon
1Departamento de Anestesiologia, Universidade Estadual de São Paulo, Brazil. ptgv@uol.com.br

Insights
Marsh pharmacokinetic parameters for propofol infusion in children resulted in a lower error rate for achieving target concentrations. This method also required less propofol for similar clinical outcomes, making it preferable for pediatric anesthesia.
Area of Science:
- Anesthesiology
- Pharmacokinetics
- Pediatric Medicine
Context:
- Target-controlled infusion (TCI) of propofol aims for stable blood concentrations.
- Optimizing TCI requires accurate pharmacokinetic models.
- Pediatric anesthesia presents unique challenges in drug dosing.
Purpose:
- To compare the clinical and laboratory performance of propofol infusion in children using two pharmacokinetic models: Shorts and Marsh.
- To evaluate the accuracy of achieving a target propofol concentration of 4 microg.kg-1.
Summary:
- Forty-one pediatric patients (4-12 years) received propofol anesthesia using either Shorts (Group S) or Marsh (Group M) parameters.
- Blood propofol concentrations were measured at 20, 40, and 60 minutes.
- Marsh parameters demonstrated a statistically significant lower error rate (EPAM) at 60 minutes and required less propofol for comparable clinical results.
Impact:
- Marsh pharmacokinetic parameters are more accurate for TCI of propofol in pediatric patients aged 4-12 years.
- This approach can lead to more efficient anesthetic management and potentially reduced drug administration.
- Recommends Marsh parameters as the preferred method for this patient population.
Background And Objectives:
Maintaining target-controlled propofol blood concentrations in approximately constant levels is a technique that can be used in a simple way in the operating room. The aim of this study was to compare in clinical and laboratorial terms propofol infusion in children, using Shorts and Marshs pharmacokinetic parameters.
Methods:
Forty-one patients of both genders, aged 4 to 12 years, physical status ASAI or ASAII were distributed in two groups: Group S (n = 20) and Group M (n = 21). Shorts pharmacokinetic parameters were applied to group S, while Marshs pharmacokinetic parameters were applied to group M. Intravenous anesthesia was induced with 30 microg.kg-1 bolus alfentanil, 3 mg.kg-1 propofol and 0.08 mg.kg-1 pancuronium. Patients were intubated and anesthesia was maintained with N2O/O2 (60%) in controlled mechanical ventilation. Propofol infusion in group S was 254 microg.kg-1 (30 min) followed by 216 microg.kg-1.min-1 for additional 30 minutes. Propofol infusion in group M was 208 microg.kg-1 (30 min.) followed by 170 microg.kg-1.min-1 for additional 30 minutes. Using specific pharmacokinetic parameters for each group, the goal was a target-concentration of 4 microg.kg-1 propofol. Three blood samples were collected (at 20, 40 and 60 minutes) to measure propofol by the High Performance Liquid Chromatography method.
Results:
Groups S and M were similar in age, height, weight and gender (p > 0.05). There were no statistically significant differences between groups in SBP, DBP, HR, FiN2O, hemoglobin SpO2 and end tidal P ET CO2. The number of repeated alfentanil boluses showed no statistically significant difference between both groups. Bispectral index (BIS) showed also no statistically significant differences between M0 (awaken) and remaining moments in both groups. Error Performance Median (EPM) and Error Performance Absolute Median (EPAM) values were statistically different between groups in moment 60. Median propofol blood concentrations (microg.kg-1) were significantly different between groups M and S in moment 60 and between moments 40 and 60 in group S.
Conclusions:
Anesthesia with propofol using Marshs pharmacokinetic parameters (group M) showed a lower error rate for obtaining 4 microg.kg-1 propofol target-concentration. In addition, less propofol was needed to obtain similar clinical results. For these reasons, it should be the method of choice for children ASA I aged 4 to 12 years.
More Related Videos
 14:52
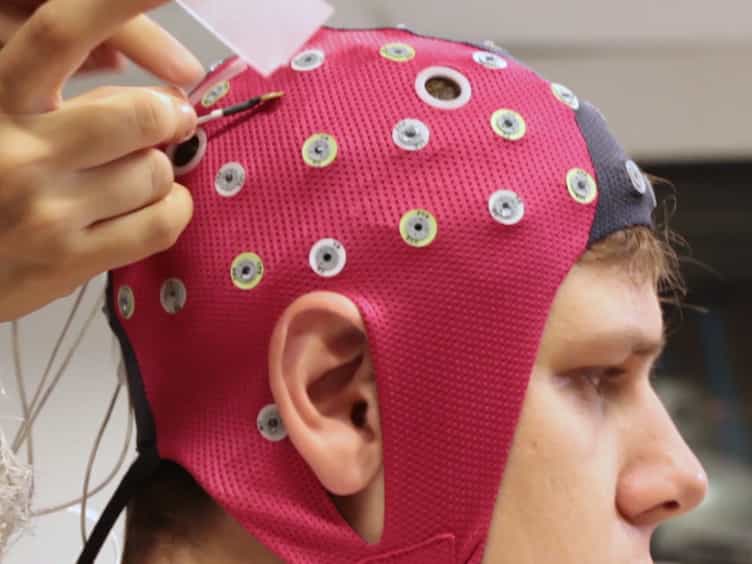
Recording Brain Electromagnetic Activity During the Administration of the Gaseous Anesthetic Agents Xenon and Nitrous Oxide in Healthy Volunteers
Published on: January 13, 2018
 09:36
Halogenated Agent Delivery in Porcine Model of Acute Respiratory Distress Syndrome via an Intensive Care Unit Type Device
Published on: September 24, 2020
Related Concept Videos
 01:24
Parenteral Anesthetics: Overview
 01:20
Inhalational Anesthetics: Overview
 01:18
Drug Delivery: Enteral Route
Drugs in...
 01:28
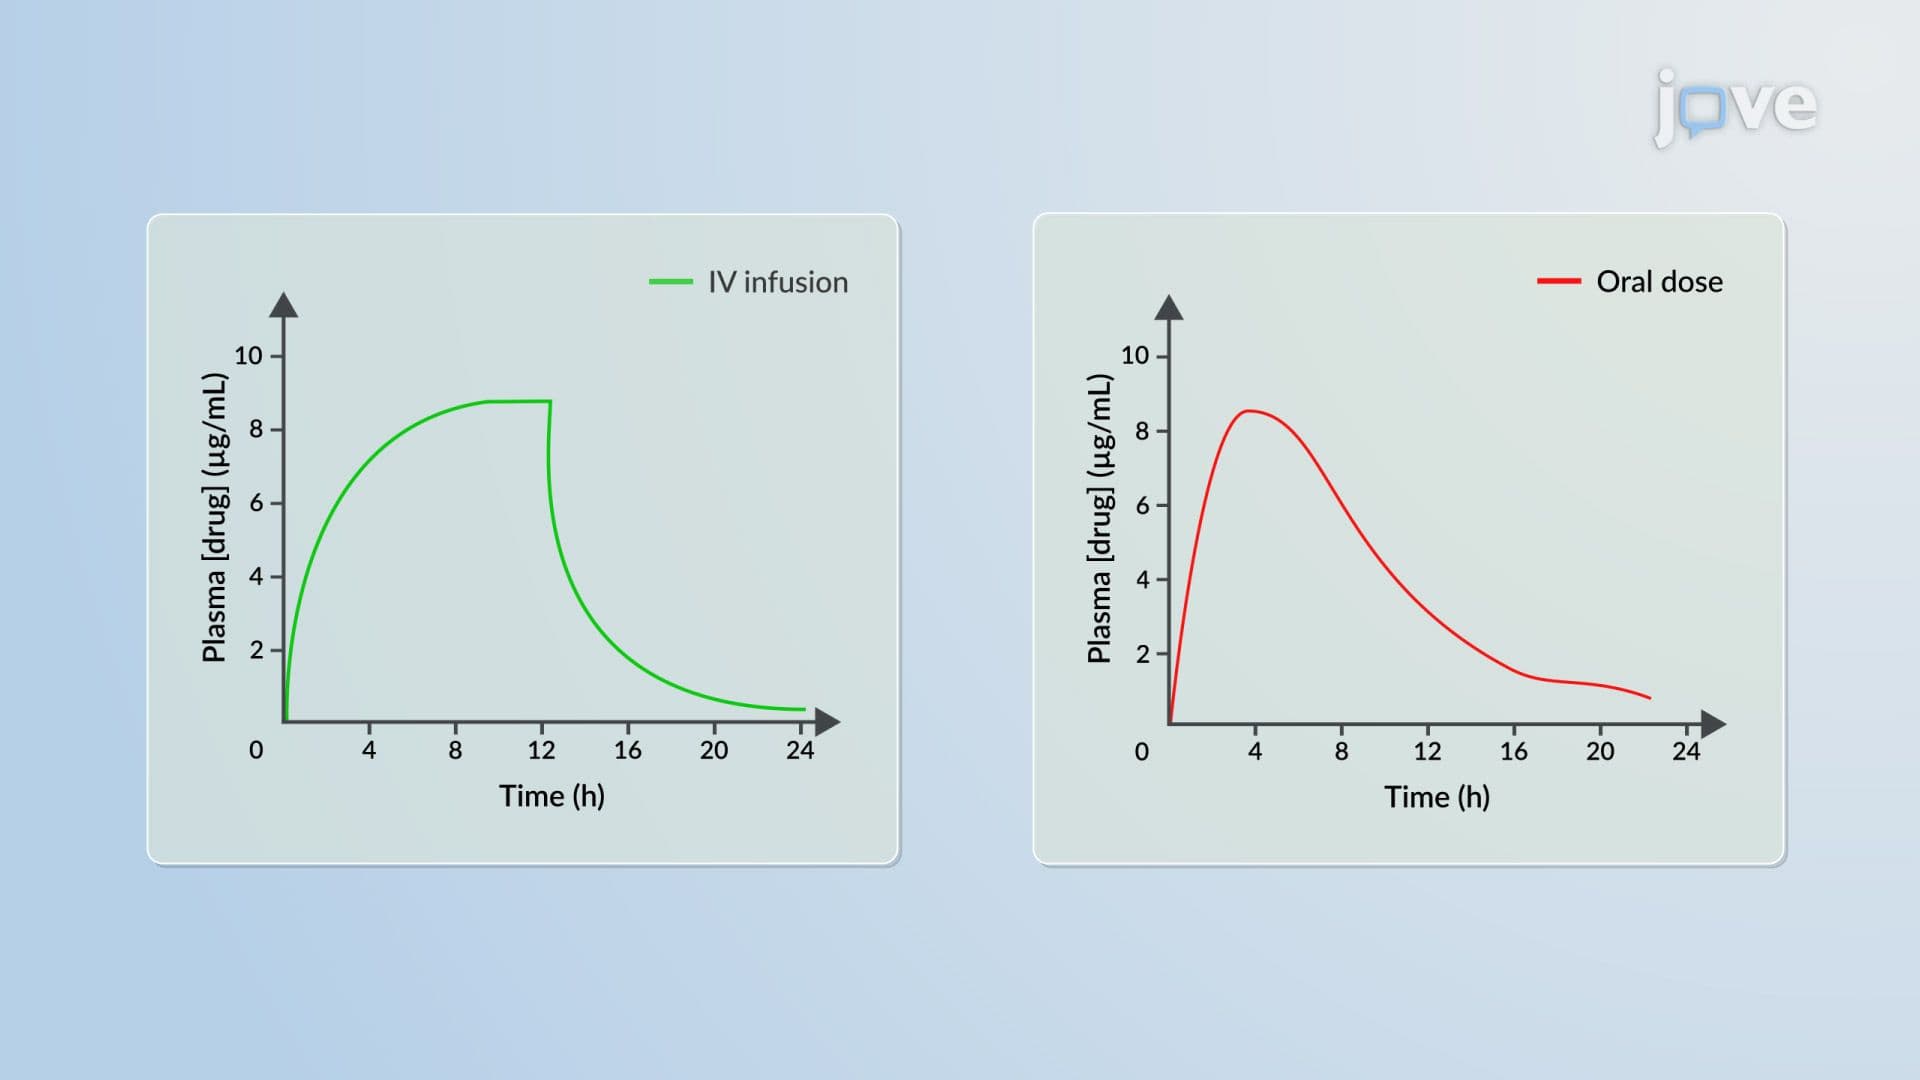
IV Infusion to Oral Dosing: Conversion Methods
 01:29
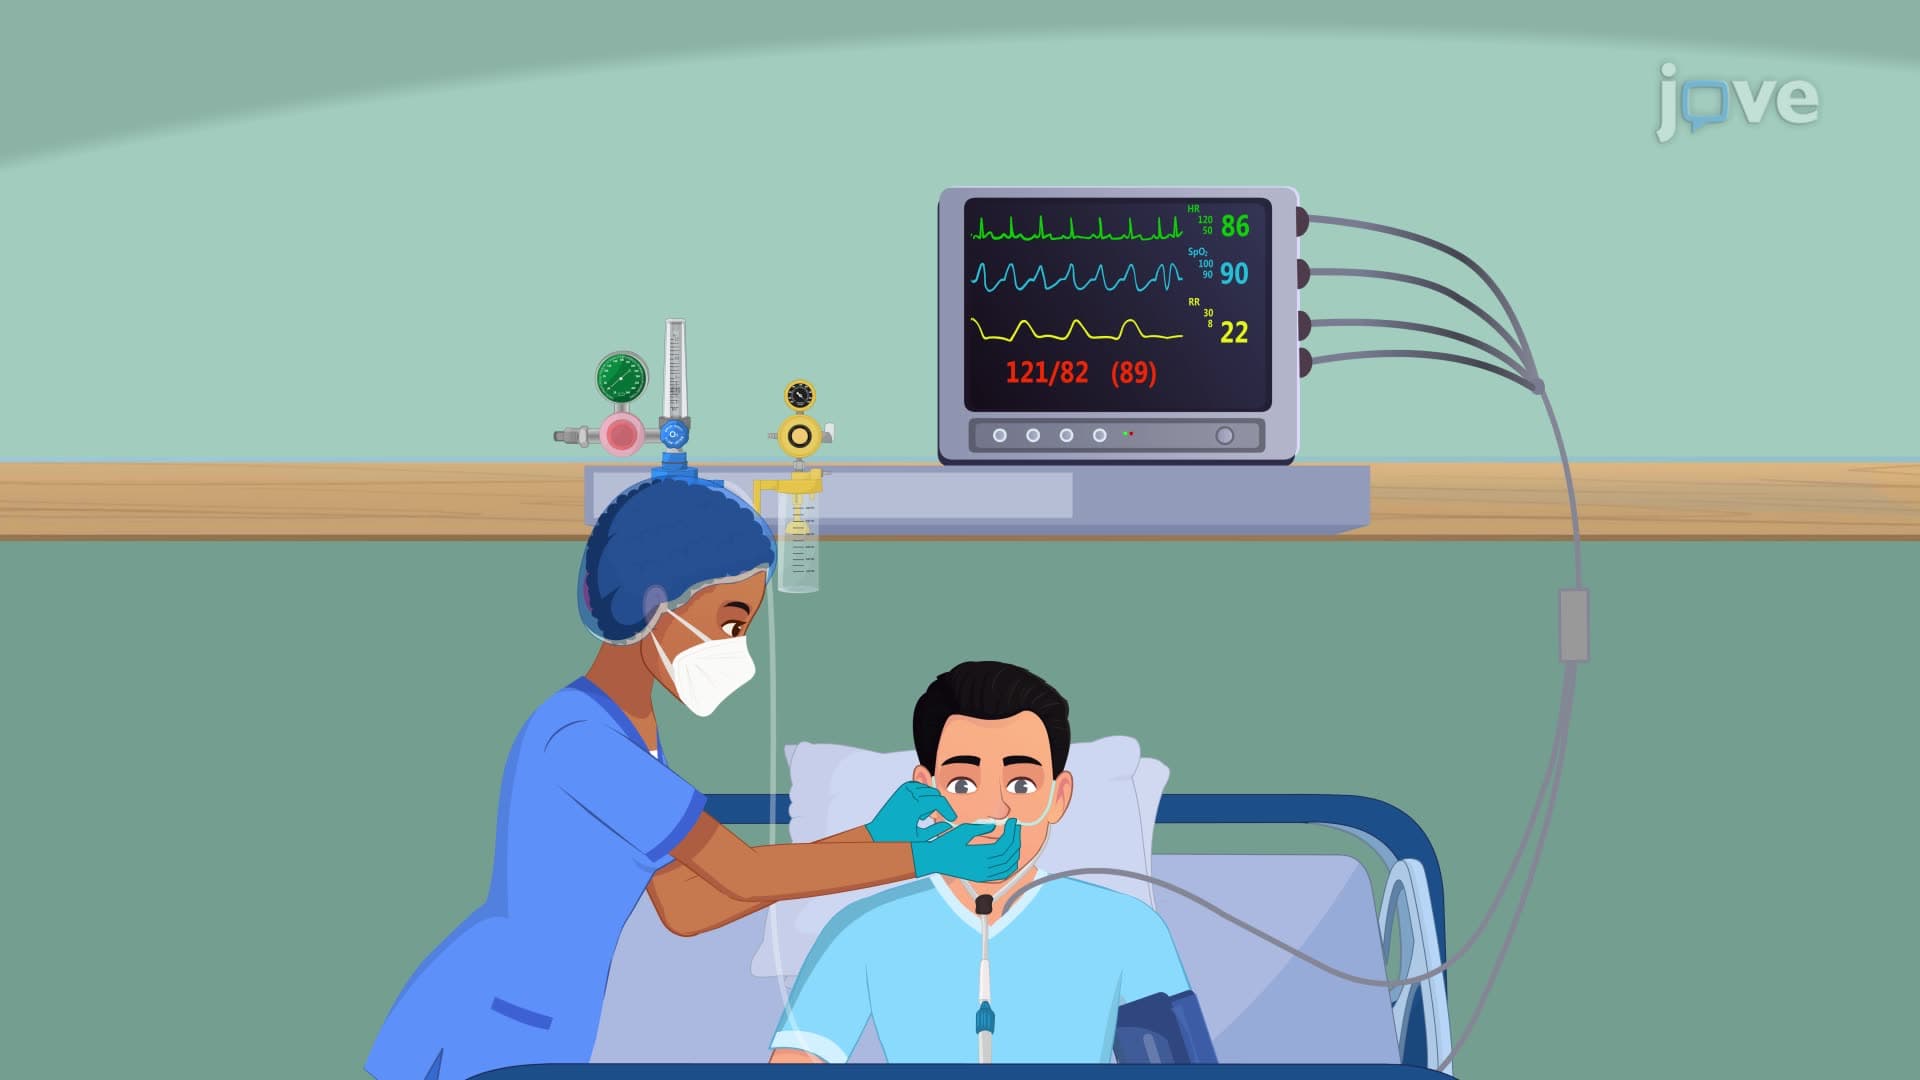
Administering Oxygen by Nasal Cannula
Nasal Cannulas
A nasal cannula is a lightweight tube split into two prongs placed in the nostrils, connected...
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution