Related Experiment Video
Updated: Jun 22, 2026


Assessment of Intestinal Transcytosis of Neonatal Escherichia coli Bacteremia Isolates
Published on: February 17, 2023
Clinical and laboratory assessment of dehydration severity in children with acute gastroenteritis
Patricia C Parkin1, Colin Macarthur, Amina Khambalia
1Division of Pediatric Medicine and the Pediatric Outcomes Research Team, Hospital for Sick Children, 555 University Avenue, Toronto, Ontario, Canada. patricia.parkin@sickkids.ca

Insights
Assessing dehydration in young children with acute gastroenteritis can be improved by using the Clinical Dehydration Scale and laboratory tests. These tools help clinicians better determine the severity of dehydration.
Area of Science:
- Pediatric Emergency Medicine
- Clinical Assessment
- Gastroenterology
Background:
- Dehydration is a common complication of acute gastroenteritis in children.
- Accurate assessment of dehydration severity is crucial for appropriate management.
- Existing clinical and laboratory methods require further evaluation for reliability.
Purpose of the Study:
- To evaluate the effectiveness of clinical and laboratory assessments in determining dehydration severity.
- To analyze the predictive value of specific clinical scores and laboratory markers.
- To provide evidence for improved diagnostic algorithms in pediatric dehydration.
Main Methods:
- A study was conducted on children aged 1 to 36 months with acute gastroenteritis.
- Clinical assessments using the Clinical Dehydration Scale were performed.
- Laboratory measures including venous pH and serum bicarbonate levels were collected.
- Weight change post-rehydration was used as an outcome measure.
Main Results:
- The Clinical Dehydration Scale showed varying likelihood ratios (LR+) for different score ranges.
- A clinical score of 5 to 8 had an LR+ of 5.2 (95% CI = 2.2-12.8).
- Laboratory measures demonstrated significant predictive value: venous pH <7.32 (LR+ = 7.2) and serum bicarbonate <18 mmol/L (LR+ = 11.6).
Conclusions:
- The Clinical Dehydration Scale is a valuable tool for assessing dehydration severity in children.
- Laboratory markers, particularly venous pH and serum bicarbonate, significantly aid in evaluating dehydration.
- Integrating clinical and laboratory assessments can enhance clinical decision-making for pediatric dehydration.
Objective:
To evaluate clinical and laboratory assessment of dehydration severity in children, 1 to 36 months, with acute gastroenteritis.
Study Design:
Clinical and laboratory measures and weight change following rehydration were collected for enrolled children.
Setting:
Pediatric emergency department.
Results:
Likelihood ratio (LR+) and 95% confidence interval (CI): for a clinical score of 0, the LR+ was 2.2 (95% CI = 0.9-5.3); for a clinical score of 1 to 4, the LR+ was 1.3 (95% CI = 0.90-1.74); for a clinical score of 5 to 8, the LR+ was 5.2 (95% CI = 2.2-12.8); for a venous pH <7.32, the LR+ was 7.2 (95% CI = 2.4-21.9); and for serum bicarbonate <18 mmol/L, the LR+ was 11.6 (95% CI = 3.5-38.0).
Conclusion:
Clinicians may find it useful to incorporate the Clinical Dehydration Scale and laboratory measures into clinical decision-making algorithms to assess dehydration severity in children with acute gastroenteritis.
Related Concept Videos
 01:29
Acute Kidney Injury III: Clinical Manifestations
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:17
Assessment of the Gastrointestinal System I: Subjective Data
Health History
The initial step in assessing the GI system is obtaining a comprehensive health history. This includes inquiring about the patient's history or presence of problems related to...
 01:18
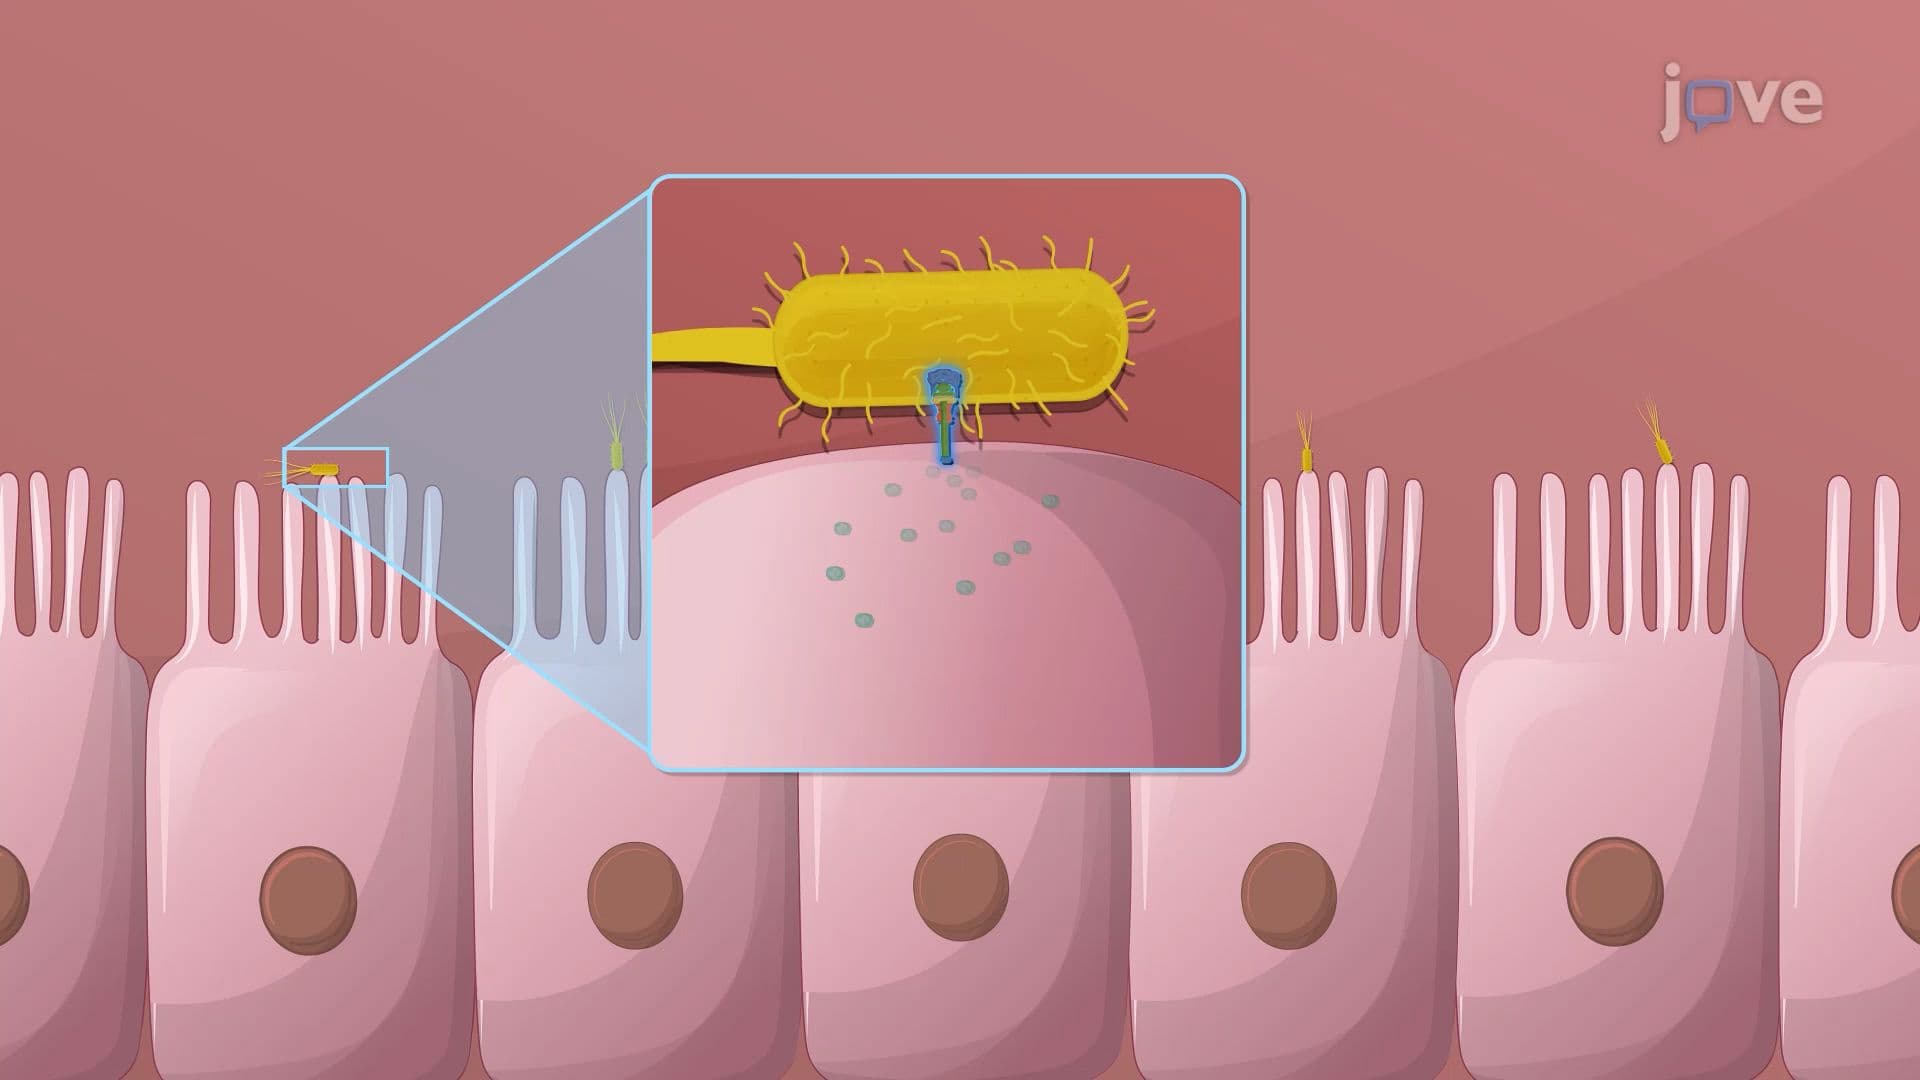
Bacterial Gastroenteritis
 01:30
Irritable Bowel Syndrome II: Clinical Features and Diagnostic Evaluation
Irritable Bowel Syndrome (IBS) is classified into subtypes based on the predominant bowel habits as determined by the Bristol Stool Form Scale (BSFS). The subtypes are:
 01:30
Serum Laboratory Studies, Stool Test, Breath Test