[Insulin pump for treatment of children and adolescents with diabetes]
Related Experiment Video
Updated: Jun 22, 2026

Improving IV Insulin Administration in a Community Hospital
Published on: June 11, 2012
Dag Helge Frøisland1, Anne Lee Solevåg, Trond Markestad
1Sykehuset Innlandet, 2629 Lillehammer. dag.froisland@hil.no

Insights
Insulin pumps offer comparable safety and disease control for pediatric diabetes patients compared to multiple daily injections. Most children and adolescents also prefer insulin pump therapy for better diabetes management.
Area of Science:
- Pediatric Endocrinology
- Diabetes Management
- Metabolic Control
Background:
- Stricter metabolic control targets for pediatric diabetes patients.
- Comparison of insulin administration methods is crucial for optimizing care.
- Advancements in diabetes technology necessitate updated treatment evaluations.
Purpose of the Study:
- To compare multi-injection insulin therapy with continuous subcutaneous insulin infusion (insulin pumps) in children and adolescents with type 1 diabetes.
- To evaluate differences in metabolic control (HbA1c, ketoacidosis, hypoglycemia) between the two insulin delivery methods.
- To assess patient satisfaction and preference for each insulin administration method.
Main Methods:
- Retrospective analysis of 80 pediatric patients with type 1 diabetes from 1995-2004.
- Data collection from medical records and a national pediatric diabetes monitoring program.
- Assessment of glycosylated hemoglobin (HbA1c), ketoacidosis incidence, severe hypoglycemia, and patient preference.
Main Results:
- Mean HbA1c levels decreased from 9.1 to 8.3 as insulin pump use increased.
- Insulin pump users showed a trend towards lower mean HbA1c, but no significant difference in ketoacidosis or hypoglycemia rates.
- By study end, 76% of patients utilized insulin pumps, with high patient preference.
Conclusions:
- Insulin pumps provide comparable safety and metabolic control to multiple daily injections in pediatric diabetes patients.
- Continuous subcutaneous insulin infusion is a preferred method of insulin delivery for most children and adolescents with type 1 diabetes.
- Insulin pump therapy is a viable and preferred option for optimizing diabetes management in pediatric populations.
Background:
The goals for metabolic control of children and adolescents with diabetes are stricter than previously. The purpose of the study was to compare two ways of administering insulin; i.e. multi-injection and continuous subcutaneous infusion, with respect to metabolic control and patient satisfaction.
Material And Methods:
The study material consisted of all patients with type I diabetes, treated at the paediatric outpatient clinic, Innlandet Hospital Trust (Lillehammer), Norway in the period 1995 - 2004 (i.e. 5 years before and 5 years after insulin pumps became available). Patient information was retrieved from medical records and the Norwegian benchmarking study on paediatric diabetes (a national monitoring programme for children and adolescents with diabetes). Measures of disease control were glycosylated hemoglobin (HbA1c), incidence of ketoacidosis and severe hypoglycemia, and patient satisfaction in terms of patient preference.
Results:
80 patients were included in the study. Mean HbA1c was unchanged during the first 5-year period, but gradually decreased from 9.1 (SD 1.6 ) to 8.3 (SD 0.9) as the proportion of patients on continuous infusion increased. Mean HbA1c tended to be lower for pump users, but there was no change in the frequency of ketoacidosis or hospitalization due to hypoglycemia. 76 % of patients used an insulin pump at the end of the study. One patient reverted to multi-injections.
Interpretation:
The study suggests that insulin pumps compare well with multi-injections with respect to safety and disease control and that most children and adolescents prefer the pumps.

Related Concept Videos
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:22
Diabetes Mellitus: Overview and Type I Subtype
Type 1 diabetes is an autoimmune disease in which the immune system mistakenly attacks and destroys the insulin-producing beta cells in the pancreas. As a result, the body is unable to produce sufficient insulin, and individuals with...
 01:27
Insulin Formulations: Types and Delivery
Short-acting insulins are divided into rapid-acting...
 01:15
Diabetes: Management and Pharmacotherapy
Insulin remains the cornerstone of treatment for most patients with type 1 and many...
 01:29
Drug Dosing: Infants and Children
 01:25
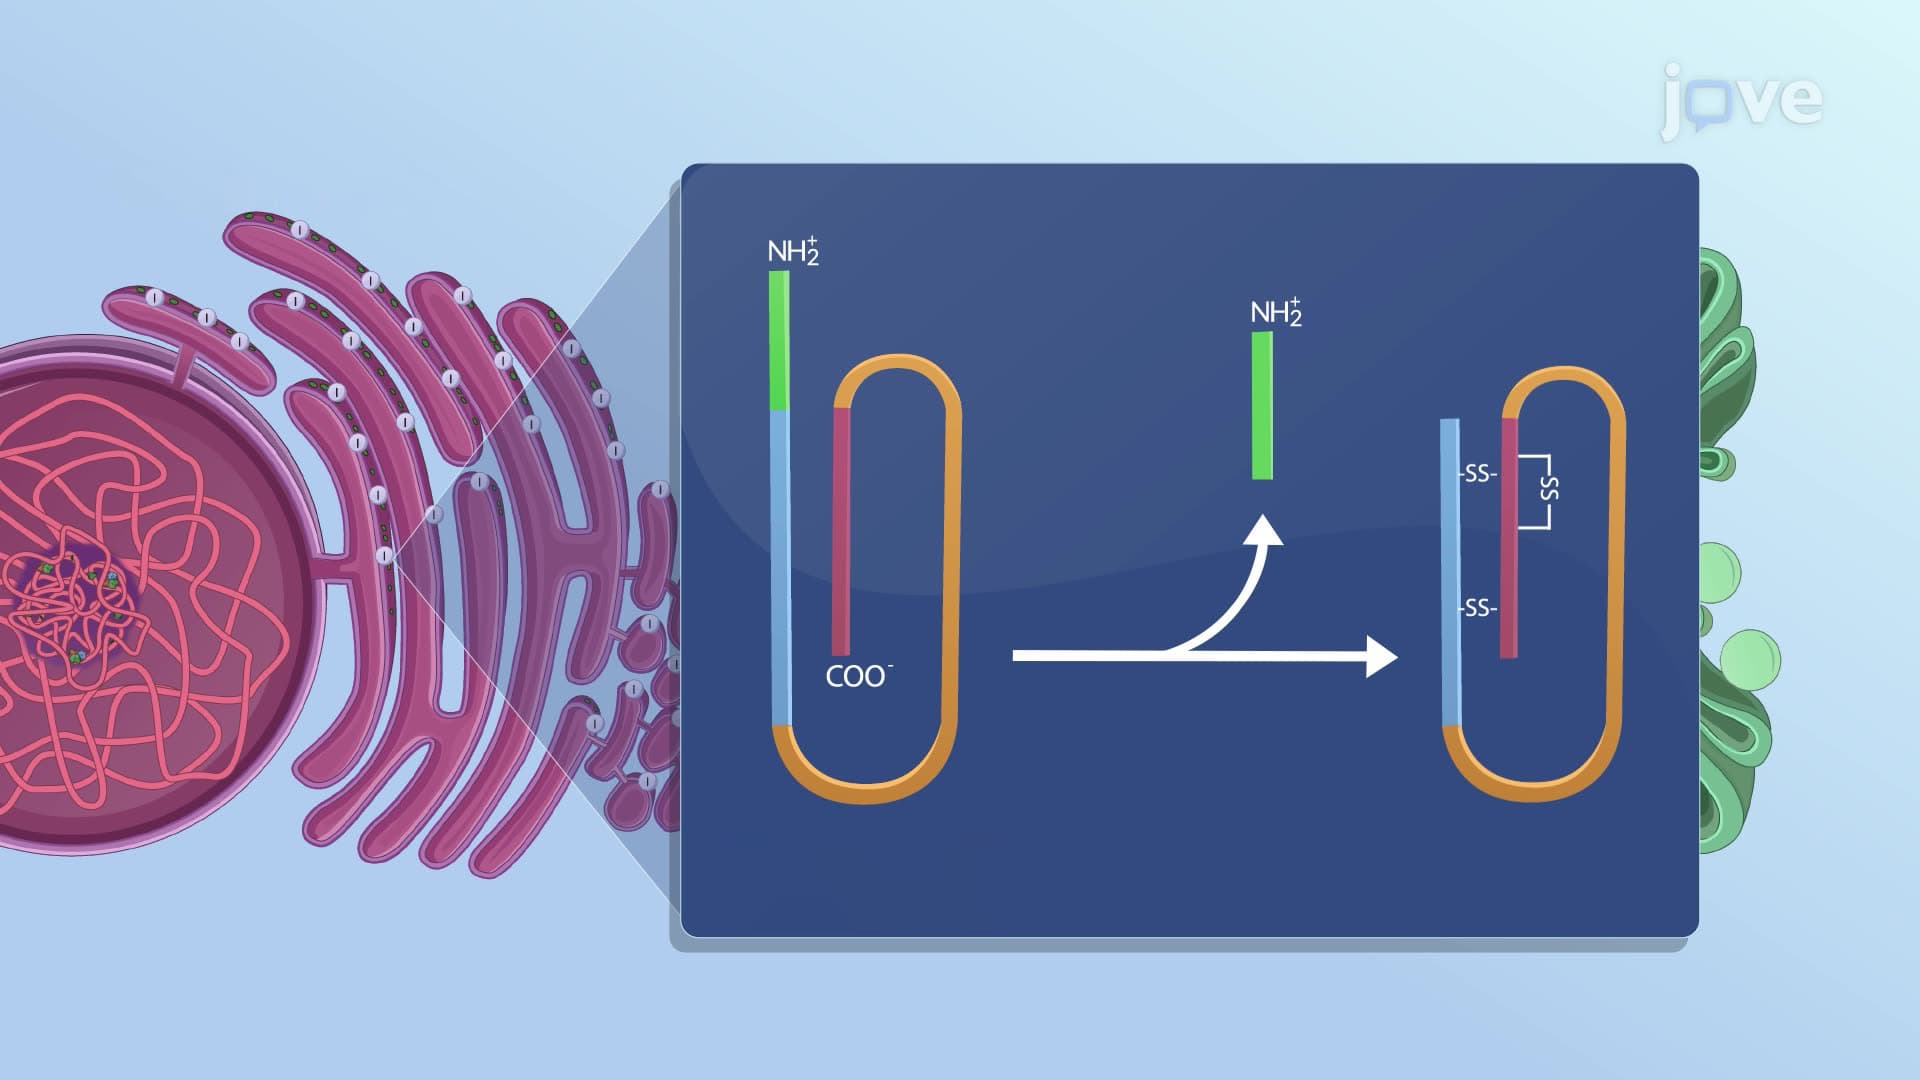
Insulin: Biosynthesis, Chemistry, and Preparation
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment primarily uses...