Related Experiment Video
Updated: Jun 22, 2026


Complete and Partial Resuscitative Endovascular Balloon Occlusion of the Aorta for Hemorrhagic Shock
Published on: May 19, 2022
Benefits of the RAS blockade: clinical evidence before the ONTARGET study
Christine Perret-Guillaume1, Laure Joly, Piotr Jankowski
1Department of Geriatrics, Medical School of Nancy, Nancy, France.

Abstract:
Activation of the AT1 angiotensin II (Ang II) receptors has various effects including vasoconstriction, hypertrophy, and possibly hyperplasia of vascular smooth muscle cells and cardiomyocytes and increase in extracellular collagen matrix synthesis. These actions lead to the development of cardiovascular hypertrophy and fibrosis, as well as arterial stiffness, which are some key factors in the development of the cardiovascular and renal complications. In clinical studies, it has been shown that renin-angiotensin blockade has direct and specific implications in the evolution of heart failure, coronary disease, stroke, and hypertensive and diabetic renal disease. The beneficial cardiovascular and renal effects of blocking the renin-angiotensin-aldosterone system reported in numerous clinical trials may be at least partially related to the actions of these drugs on cardiovascular and renal fibrosis, and arterial stiffness. These effects are now well-established and lead the international medical societies to propose the use of the renin-angiotensin system (RAS) blockers as initial treatment (both angiotensin-converting enzyme inhibitors and angiotensin II receptor blockers) in several cardiovascular, metabolic, and renal disorders such as hypertension, heart failure, and proteinuria.
Insights
Blocking the renin-angiotensin system (RAS) reduces cardiovascular and renal disease by targeting angiotensin II (Ang II) receptor activation. RAS blockers are recommended for hypertension, heart failure, and proteinuria.
Area of Science:
- Cardiovascular Medicine
- Nephrology
- Pharmacology
Background:
- Activation of angiotensin II (Ang II) receptors promotes vasoconstriction, cardiac and vascular hypertrophy, and fibrosis.
- These effects contribute to cardiovascular and renal complications, including arterial stiffness, heart failure, and kidney disease.
Purpose of the Study:
- To review the implications of renin-angiotensin blockade in cardiovascular and renal diseases.
- To highlight the role of blocking the renin-angiotensin-aldosterone system (RAAS) in managing these conditions.
Main Methods:
- Review of clinical studies and trials on renin-angiotensin system (RAS) blockers.
- Analysis of the effects of RAS blockade on cardiovascular and renal fibrosis and arterial stiffness.
Main Results:
- Renin-angiotensin blockade demonstrates direct and specific benefits in heart failure, coronary disease, stroke, and hypertensive and diabetic renal disease.
- Beneficial cardiovascular and renal effects are linked to reduced fibrosis and arterial stiffness.
Conclusions:
- Blocking the renin-angiotensin-aldosterone system (RAAS) offers significant cardiovascular and renal protection.
- International guidelines recommend RAS blockers (ACE inhibitors and ARBs) as first-line treatment for hypertension, heart failure, and proteinuria.
Related Concept Videos
 01:25
Antianginal Drugs: Calcium Channel Blockers and Ranolazine
CCBs, a diverse class that includes dihydropyridines (nifedipine) and diphenylalkylamines (verapamil and diltiazem), exert their effect by blocking calcium channels in cardiac and smooth muscle cells. This...
 01:27
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers
 01:25
Antihypertensive Drugs: Direct Renin Inhibitors
 01:17
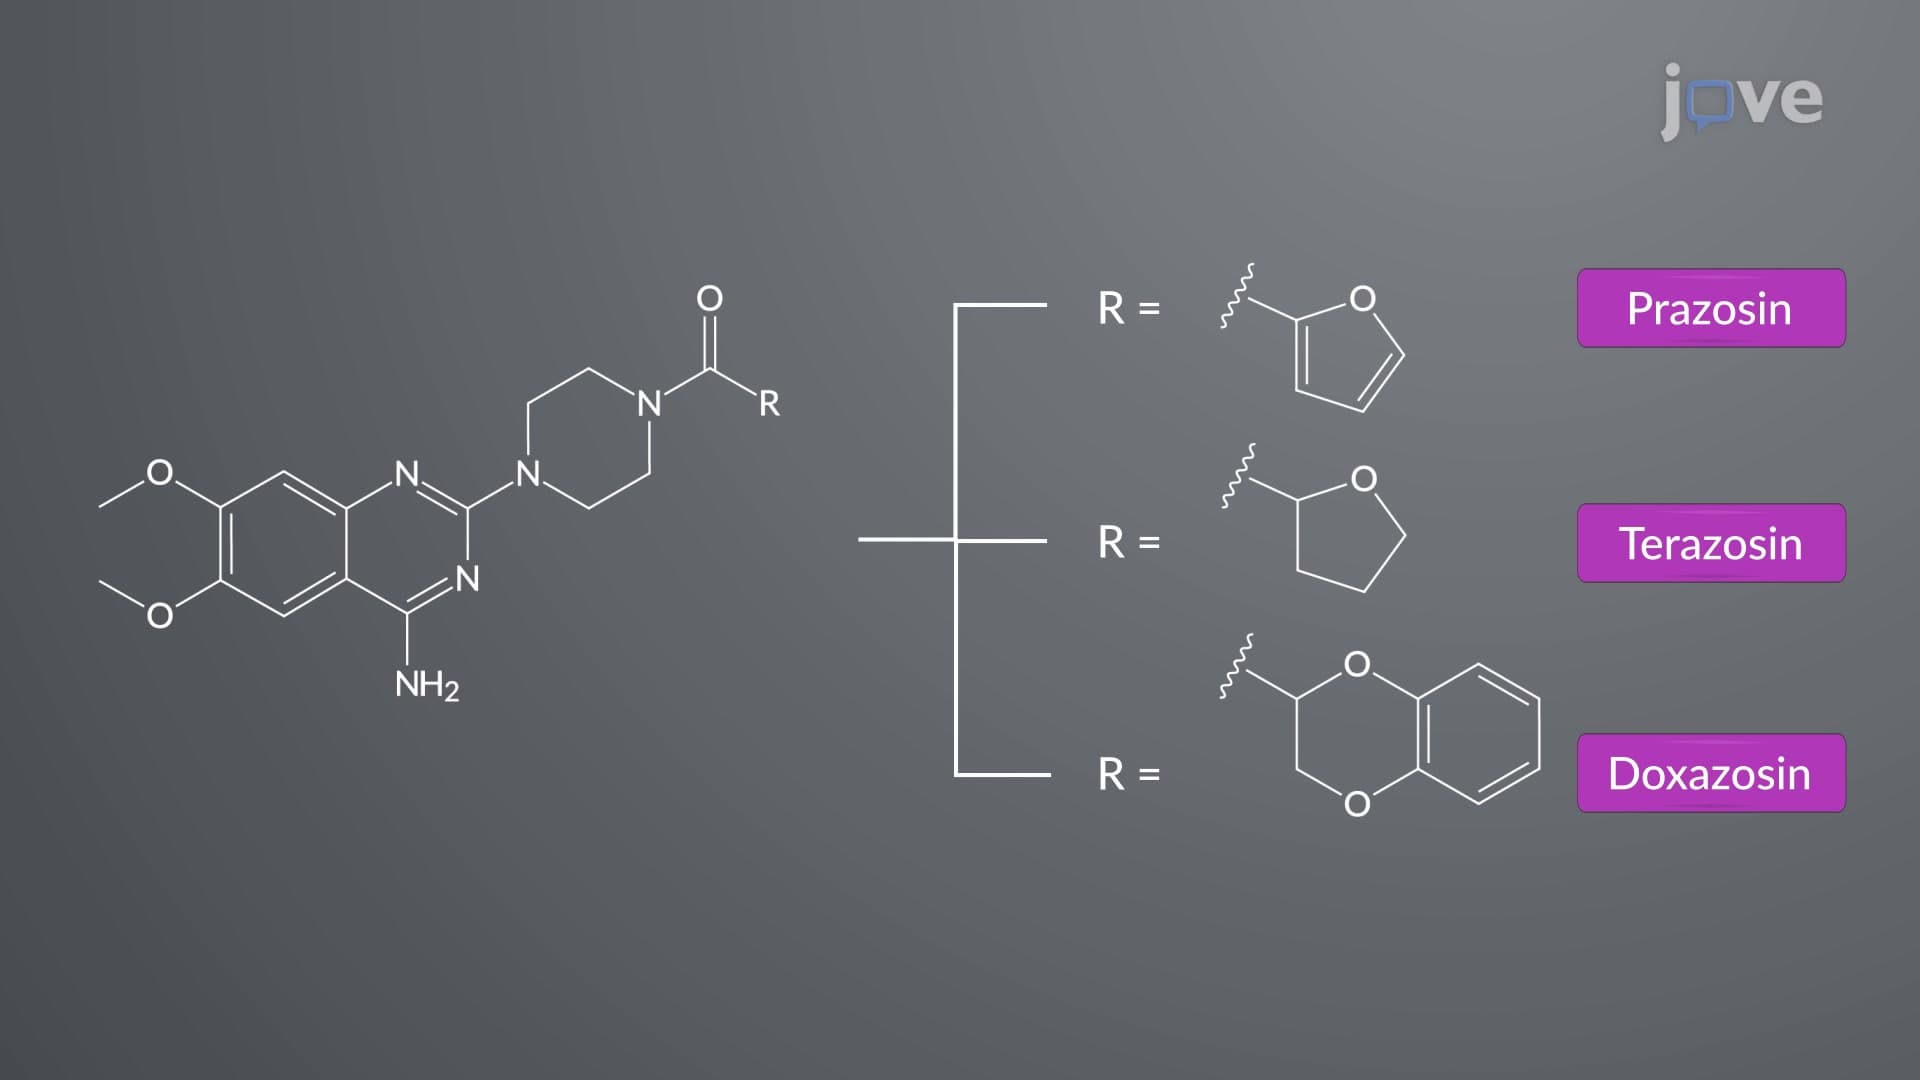
Adrenergic Antagonists: Chemistry and Classification of ɑ-Receptor Blockers
Nonselective α-blockers: Nonselective α-blockers contain haloalkylamine or imidazoline moieties. Phenoxybenzamine, with a haloalkylamine...
 01:26
Treatment for Pulmonary Arterial Hypertension: Receptor Tyrosine Kinase Inhibitors and Calcium Channel Blockers
TKIs, such as imatinib (Gleevec), are particularly effective in tackling the growth and mitogenic factors that become upregulated in PAH patients. These factors contribute to the...
 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...