Related Experiment Video
Updated: Jun 22, 2026

Assessing Urinary Tract Junction Obstruction Defects by Methylene Blue Dye Injection
Published on: October 12, 2017
Age-dependent renal expression of acid-base transporters in neonatal ureter obstruction
Guixian Wang1, Sukru Oguzkan Topcu, Troels Ring
1The Water and Salt Research Center, University of Aarhus, Aarhus C, Denmark.

Abstract:
Congenital obstructive nephropathy accounts for a major proportion of renal insufficiency in infancy and childhood. In an earlier investigation we demonstrated that bilateral complete ureteral obstruction (BUO) in rats is associated with inadequate urinary acidification [Am J Physiol Renal Physiol. 295(2):F497-506, 2008]. The aim of the study reported here was to determine whether this defect is also associated with unilateral ureteral obstruction (UUO), which is clinically more common than BUO. The time-course of the changes in protein expression levels of major renal acid-base transporters was examined at 7 and 14 weeks in rats with neonatally induced partial unilateral ureteral obstruction (PUUO), which was performed within the first 48 h of life. We observed that protein expression of the renal acid-base transporters NHE3, NBC1, NBCn1, pendrin and Na(+)-K(+)-ATPase was increased in both obstructed and non-obstructed kidneys 7 weeks after the induction of neonatal PUUO. This was confirmed by immunocytochemistry. In contrast, 14 weeks after the induction of PUUO, there was a significant downregulation of the renal acid-base transporters NBC1, NBCn1 and Na(+)-K(+)-ATPase in the obstructed kidneys. These time/age-dependent changes in protein expression were associated with parallel changes in renal function resulting in urine acidification in response to exogenous acid loading. In conclusion, these results show that downregulation of protein expression is a time/age-dependent response to PUUO, which could contribute to the decreased net acid excretion and development of metabolic acidosis in neonatal rats with PUUO.


Related Concept Videos
 01:29
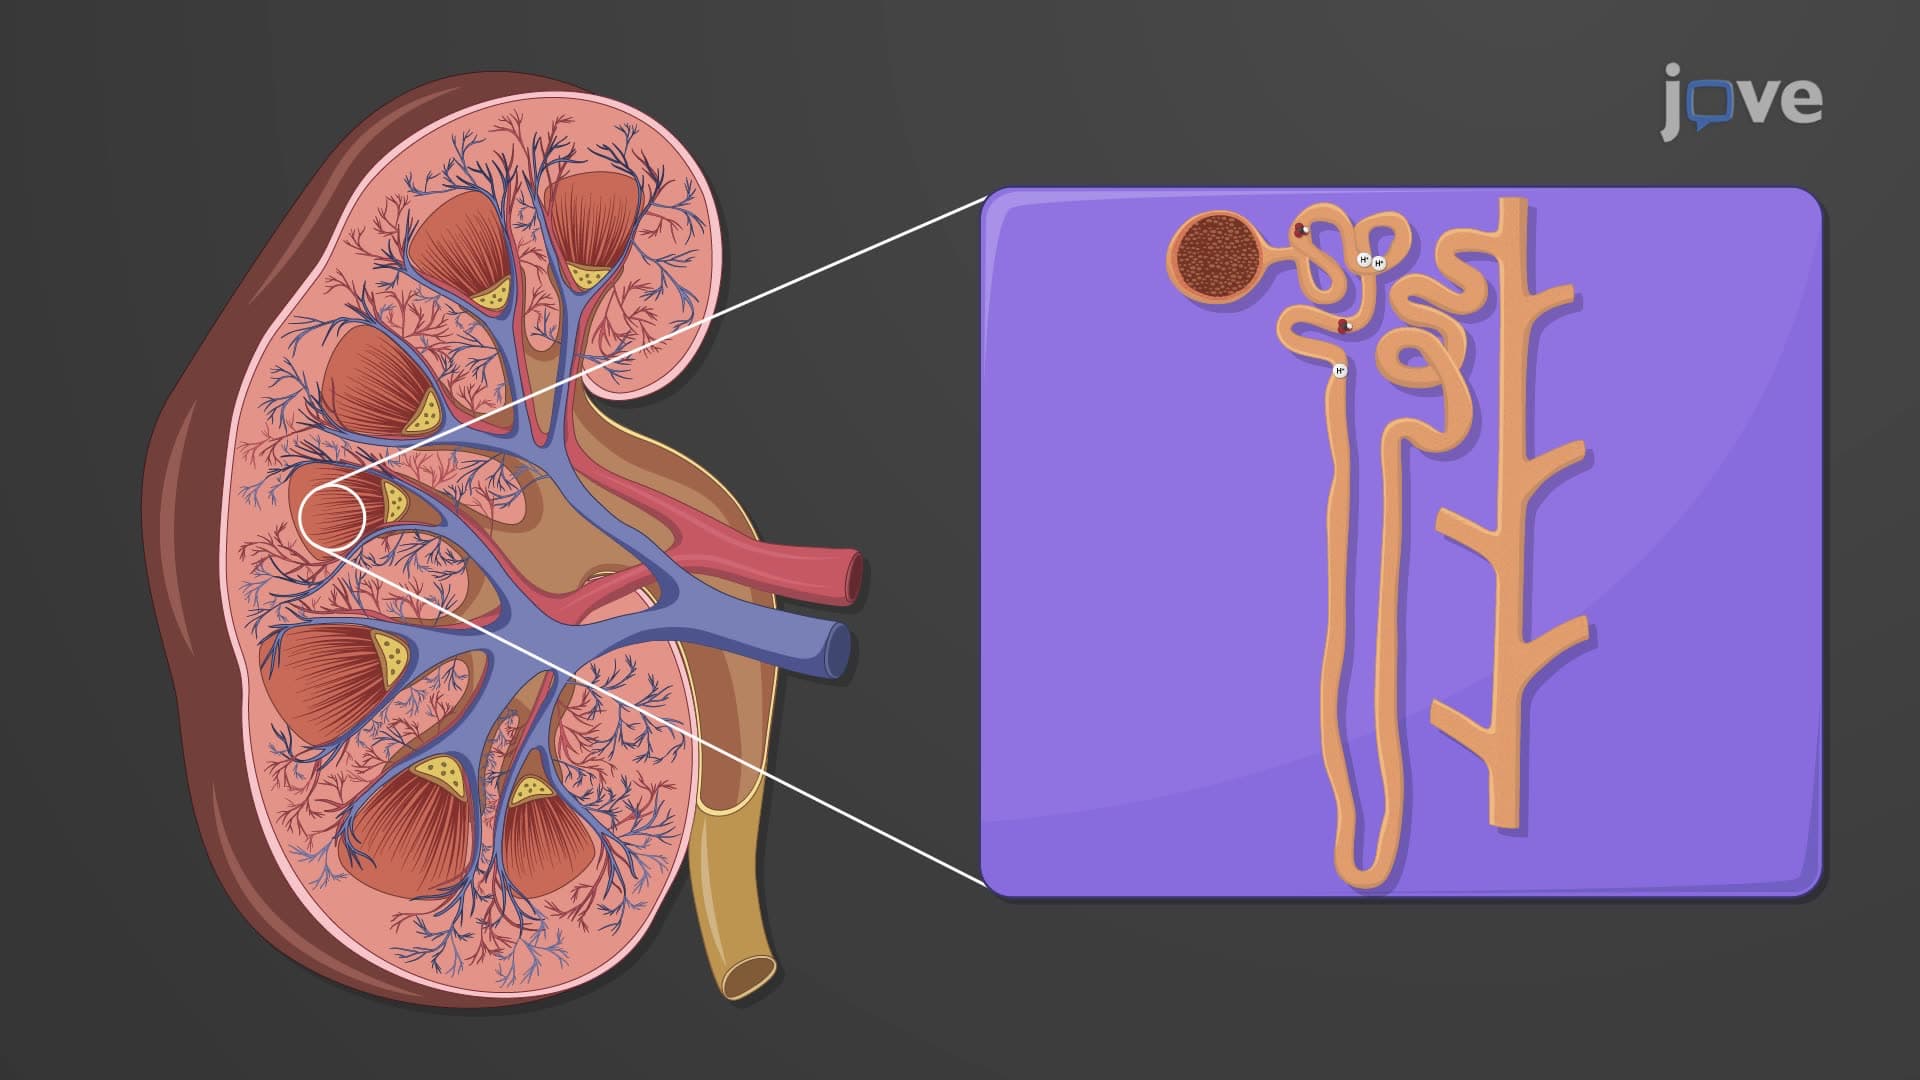
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:29
Acute Kidney Injury II: Pathophysiology
 01:28
Renal Drug Excretion: Tubular Secretion
 01:20
Physiology of the Genitourinary System III: Urine Concentration and Dilution