Related Experiment Video
Updated: Jun 22, 2026

Development of Recombinant Proteins to Treat Chronic Pain
Published on: April 11, 2018
Efficacy of ShotBlocker in reducing pediatric pain associated with intramuscular injections
Lisa A Drago1, Sabina B Singh, April Douglass-Bright
1Department of Emergency Medicine, University of Medicine and Dentistry of New Jersey-Robert Wood Medical School at Camden, NJ 08103, USA. drago-l@cooperhealth.edu

Insights
ShotBlocker effectively reduced pain perception during intramuscular injections in children, as reported by nurses and caregivers. However, children
Area of Science:
- Pediatric Pain Management
- Medical Device Efficacy
- Clinical Trial Research
Background:
- Intramuscular (IM) injections are a common source of acute pain in pediatric patients.
- Effective pain reduction strategies are crucial for improving patient experience and adherence to treatment.
- The ShotBlocker device is designed to mitigate pain associated with needle-based procedures.
Purpose of the Study:
- To evaluate the efficacy of the ShotBlocker device in reducing pain experienced by children during IM injections.
- To compare pain scores between children using ShotBlocker and a control group receiving no intervention.
Main Methods:
- A prospective randomized controlled trial was conducted with 165 children aged 2 months to 17 years.
- Participants were randomized to either the ShotBlocker group or a no-intervention control group.
- Pain was assessed using Likert-type scales by nurses and caregivers, and the Baker Wong Faces scale for older children.
Main Results:
- Nurses reported significantly lower pain scores in the ShotBlocker group (1.8) compared to the no-intervention group (2.6; P < .001).
- Caregivers also reported lower pain scores with ShotBlocker use (2.1 vs 2.6; P = .04).
- No significant difference in pain was reported by children aged 36 months and older, though a trend emerged in older children (≥72 months).
Conclusions:
- Nurses and caregivers perceived ShotBlocker as effective in reducing pediatric pain during IM injections.
- The device demonstrated ease of use with low reported difficulty by nurses.
- Self-reported pain by children did not show significant differences, suggesting potential variations in pain perception reporting across different assessment methods.
Objective:
The aim of the study was to determine the efficacy of ShotBlocker (Bionix, Toledo, Ohio) in reducing pediatric pain with intramuscular (IM) injections.
Methods:
A prospective randomized controlled trial was conducted in children aged 2 months to 17 years who required an IM injection. Children were randomized to the no-intervention group or the ShotBlocker group. Demographic data and the number of IM injections were recorded. Perceived pain scores were obtained from nurses and caregivers using a 6-point Likert-type scale. Baker Wong Faces scale was used in children 36 months or older. Difficulty using the device was also rated by nurses on a 6-point scale.
Results:
One hundred sixty-five children were enrolled with 80 in the no-intervention arm and 85 in the ShotBlocker arm. The mean age of children was 45 months and 56% were male. Perceived pain scores by nurses were higher for the no-intervention group (2.6 vs 1.8, P < .001) as well as by caregivers (2.6 vs 2.1, P = .04). Children aged 36 months and older (n = 64) did not report a difference in pain scores (1.5 vs 1.3, P = .6); however, in a subgroup of children 72 months or older, pain scores trended higher in the no-intervention group (1.3 vs 0.5, P = .051). Nurse-perceived difficulty of ShotBlocker use was low 1.39 (+/-1.1).
Conclusions:
Nurses and caregivers noted lower pain scores in children assigned to the ShotBlocker group. These differences were not as evident when children rated their own pain.


Related Concept Videos
 01:11
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacokinetics
Instead, they are transported by the blood to different tissues. Muscles with a greater blood supply (arteries) and blood flow receive more...
 01:19
Depolarizing Blockers: Pharmocokinetics
 01:16
Local Anesthetics: Clinical Application as Intravenous Regional Anesthesia
One of the advantages of...
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Although all competitive neuromuscular blockers are designed...
 01:29
Drug Delivery: Parenteral Route
There are three primary parenteral routes: intravenous (IV), intramuscular (IM), and subcutaneous (SC). The IV route introduces the drug directly into the bloodstream, ensuring immediate action. The IM route...
 01:17
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
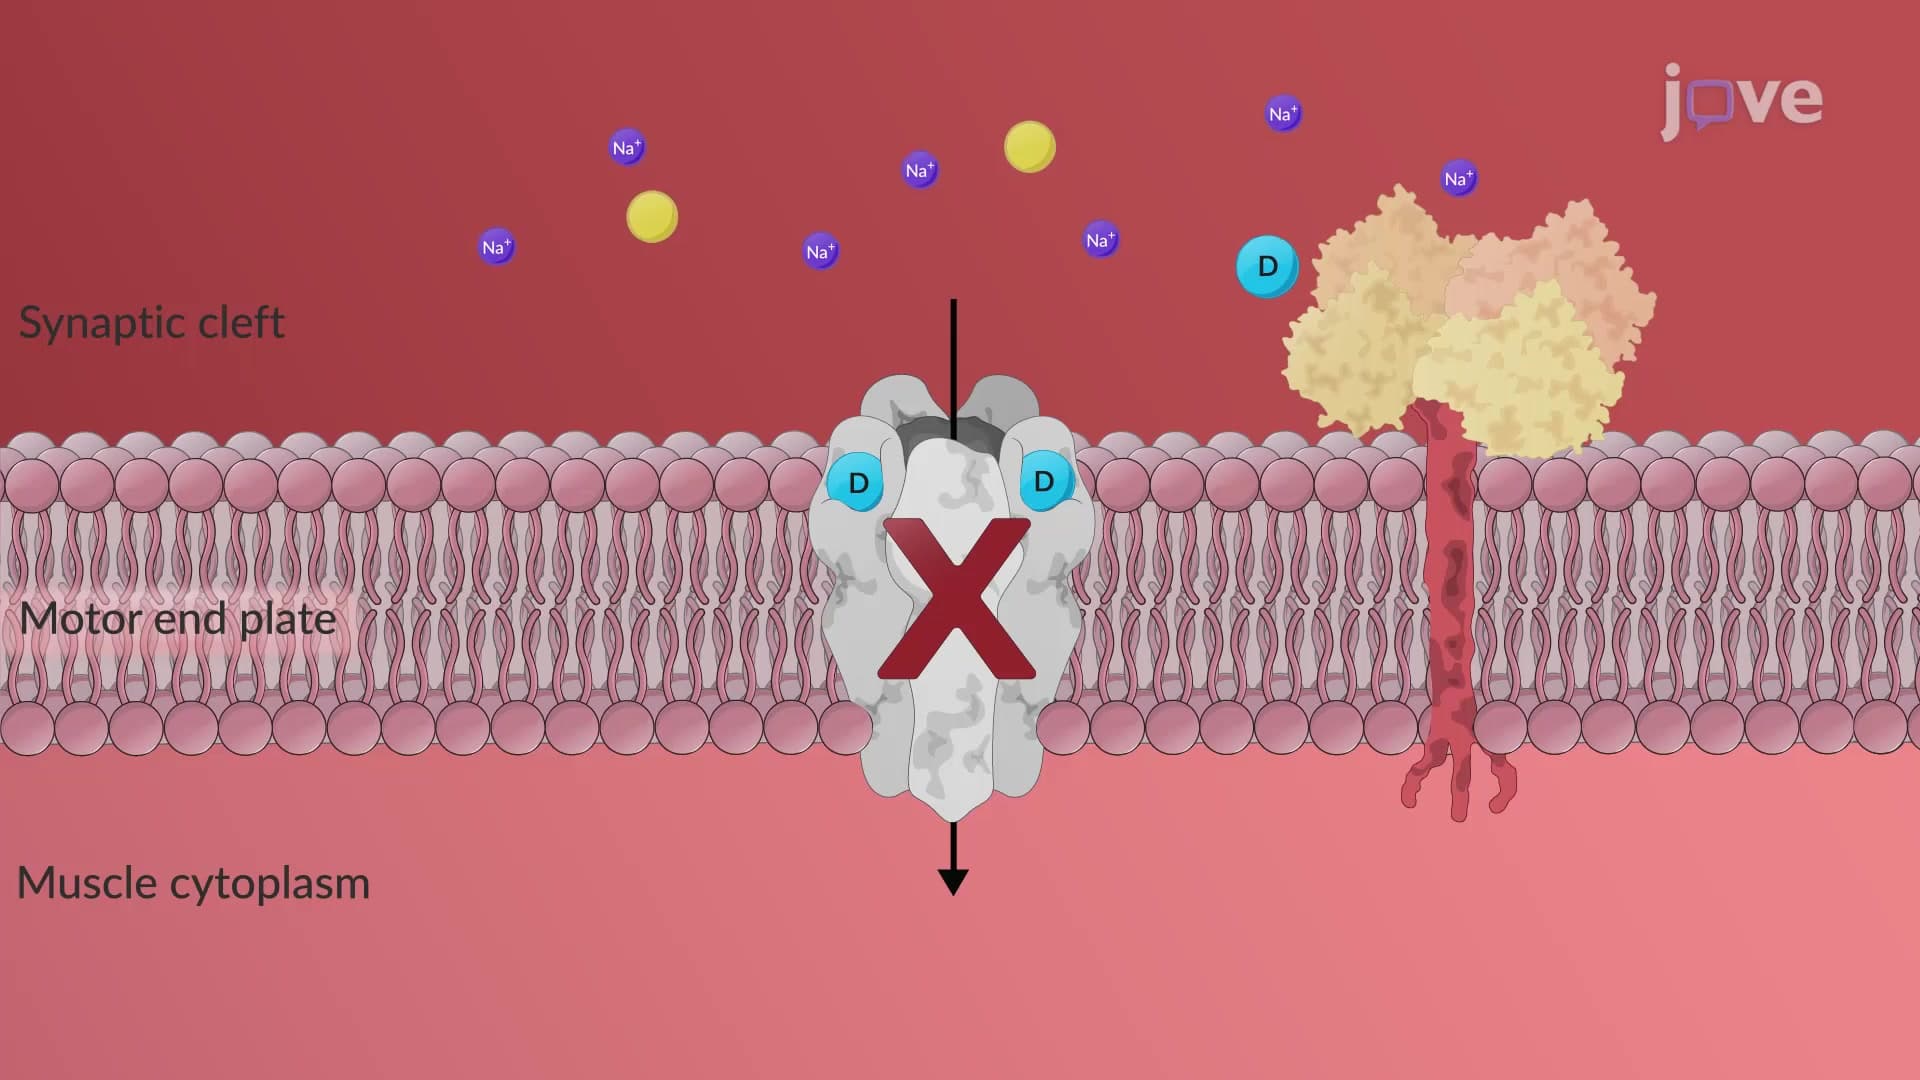
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...