Related Experiment Video
Updated: Jun 22, 2026
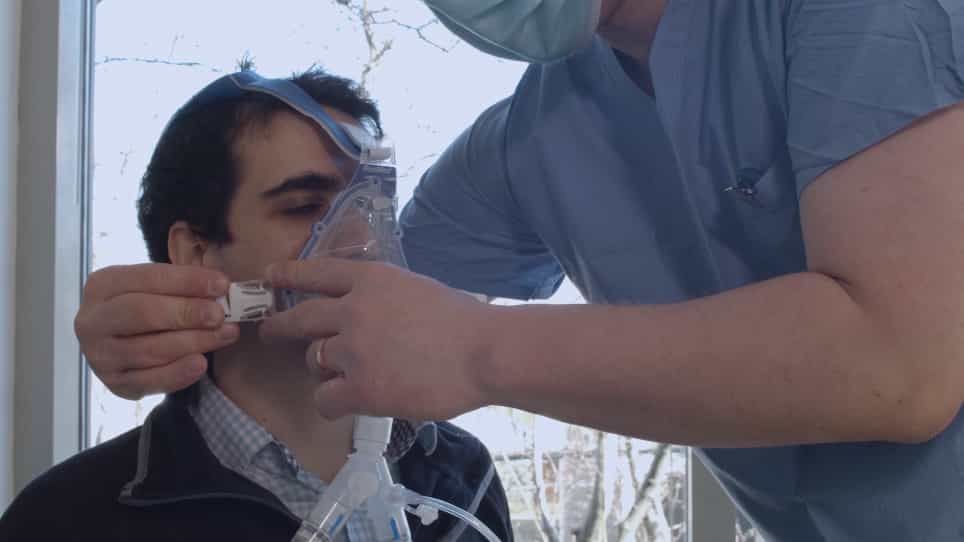

A Novel Inhalation Mask System to Deliver High Concentrations of Nitric Oxide Gas in Spontaneously Breathing Subjects
Published on: May 4, 2021
[Exhaled nitric oxide in children under 4 years of age with recurrent bronchitis]
Inés de Mir Messa1, Antonio Moreno Galdó, Nicolás Cobos Barroso
1Unidad de Neumología Pediátrica y Fibrosis Quística, Hospital Universitari Vall d'Hebron, Barcelona, España. fernandezdemir@gmail.com

Insights
Fractional exhaled nitric oxide (FE(NO)) was higher in preschool children with recurrent bronchitis compared to controls. This marker of bronchial inflammation showed a correlation with eosinophil counts.
Area of Science:
- Pediatric Pulmonology
- Respiratory Medicine
- Biomarkers
Background:
- Recurrent bronchitis is common in preschool children.
- Assessing bronchial inflammation is crucial for diagnosis and management.
- Exhaled nitric oxide (NO) is a non-invasive marker of airway inflammation.
Purpose of the Study:
- To evaluate bronchial inflammation in preschool children with recurrent bronchitis.
- To measure fractional exhaled nitric oxide (FE(NO)) as an indicator of inflammation.
- To compare FE(NO) levels between children with recurrent bronchitis and healthy controls.
Main Methods:
- Included 63 preschool children (under 4 years) with recurrent wheezing and 30 controls.
- Measured FE(NO) using samples collected during tidal breathing via a face mask.
- Analyzed FE(NO) in relation to corticosteroid treatment, eosinophil counts, and methacholine challenge tests.
Main Results:
- FE(NO) was significantly higher in children with recurrent bronchitis (5.3 ppb) versus controls (4.6 ppb).
- Higher FE(NO) levels correlated with elevated eosinophil counts (>400 microL).
- No significant difference in FE(NO) was found between controls and corticosteroid-treated patients.
Conclusions:
- A slight increase in FE(NO) was observed in preschool children with recurrent wheezing bronchitis.
- FE(NO) may serve as a biomarker for bronchial inflammation in this population.
- Further research is needed to clarify the clinical utility of FE(NO) in managing recurrent bronchitis in young children.
Background:
The objective of the study was to assess bronchial inflammation in preschool children with recurrent bronchitis by measuring exhaled nitric oxide.
Patients And Methods:
The study included patients under 4 years of age with at least 3 episodes of wheezing in the past year (n=63) and a control group (n=30). Exhaled nitric oxide was measured in samples collected offline during spontaneous tidal breathing with a face mask and stored in Mylar balloons.
Results:
The fractional exhaled nitric oxide concentration (FE(NO)) was higher in the group with bronchitis (mean [SD], 5.3 [1.3] parts per billion [ppb]) than in the control group (4.6 [1.1]ppb) (P=.02). There was a significant difference between the control group and children in the bronchitis group not treated with inhaled corticosteroids (P<.05), but not between controls and corticosteroid-treated patients. A relationship with eosinophil count was observed in that those with higher counts (>400 microL) had higher FE(NO) levels (P<.01). No relationship was observed between FE(NO) and a positive methacholine challenge test. Follow-up lasted at least 20 months. The initial FE(NO) level did not differ significantly according to whether patients were subsequently transient, infrequent, or frequent wheezers (5.2 [0.98]ppb, 5.6 [1.5]ppb, and 4.8 [1.34]ppb, respectively; P=.36).
Conclusions:
In children under 4 years of age with recurrent wheezing bronchitis who were asymptomatic at study entry, a small increase in FE(NO) was observed although there was a good deal of overlap with the control group.
Related Concept Videos
 01:17
Pulmonary Cycle: Exhalation
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:05
Breathing
 01:23
Upper Respiratory Drugs: Antitussives, Expectorants, and Mucolytics
Antitussives include codeine, dextromethorphan (Robitussin), and benzonatate (Tessalon). Codeine and dextromethorphan exert their effects centrally by suppressing the cough reflex center in the medulla. Benzonatate operates peripherally within the respiratory tract by anesthetizing...
 01:19
Chronic Obstructive Pulmonary Disease IV: Clinical Manifestations
 01:13
Asthma III: Clinical Manifestations