Related Experiment Video
Updated: Jun 22, 2026


A Novel Method: Super-selective Adrenal Venous Sampling
Published on: September 15, 2017
[Adrenal incidentalomas: etiologic diagnostics and basic therapeutic management. A mini-review]
1Università degli Studi di Parma, Libero Docente di Semeiotica Chirurgica.

Abstract:
Since the late 1970s, the number of serendipitously discovered adrenal masses has progressively increased through the widespread use of great sensitivity/high resolution diagnostic imaging while abdomen scanning for extra-adrenal lesions. The majority of these masses are benign and without evidence of endocrine activity. Most adrenal incidentalomas are cortical adenomas whereas the prevalence of adrenocortical carcinomas and other adrenal masses (lipomas, myelolipomas, angio-myelo-lipomas, sarcomas, hamartomas, lymphomas) is relatively low. Computed tomography (CT), magnetic resonance (MR) and functional radioisotope imaging together with thorough biochemical-hormonal testing are carried out to define the aetiology of these lesions. An accurate management of adrenal incidentalomas requires an agreement among radiologist, endocrinologist, oncologist and surgeon. Arguments for benign incidentalomas are mainly small size (< 4 cm), low CT attenuation coefficients and/or typical features on RM imaging. Surgery is mandatory for secretory tumours (functioning cortical adenomas, pheochromocytoma) and for adrenal malignancies. Even modest hormonal activities, as sometimes exhibited from asymptomatic pheochromocytoma or in subclinical primary hypercortisolism/hyperaldosteronism, may be associated with morbidity of some importance. In accordance with international literature, the size of adrenal incidentalomas may be a discriminant criterion for their management: surgery is recommended for masses of large (> 6 cm) diameter or increasing at CT/RM follow-up reevaluation whereas the masses between 4/6 cm form an indeterminate group where the management varies from institution to institution. Laparoscopic transperitoneal as well as retro-peritoneoscopic procedures are gaining more and more attention for less invasive treatment of adrenal incidentalomas. According to 2002 USA-National Institutes of Health guidelines, further studies are necessary to better define natural history, CT and RM malignant features, functional aptitudes of adrenal incidentalomas in order to propose optimal modalities of follow-up and proper surgical strategies.


Related Concept Videos
 01:27
Adrenal Gland Disorders
Adrenal insufficiency, characterized by insufficient cortisol and aldosterone production, leads to conditions like Addison's disease. This disorder, affecting the adrenal cortex, exhibits symptoms such as skin bronzing, dehydration, low blood pressure, fatigue, and weight loss. Congenital adrenal hyperplasia, a genetic ailment causing...
 01:26
Cushing Syndrome I: Introduction
 01:19
Cushing Syndrome II: Pathophysiology
 01:17
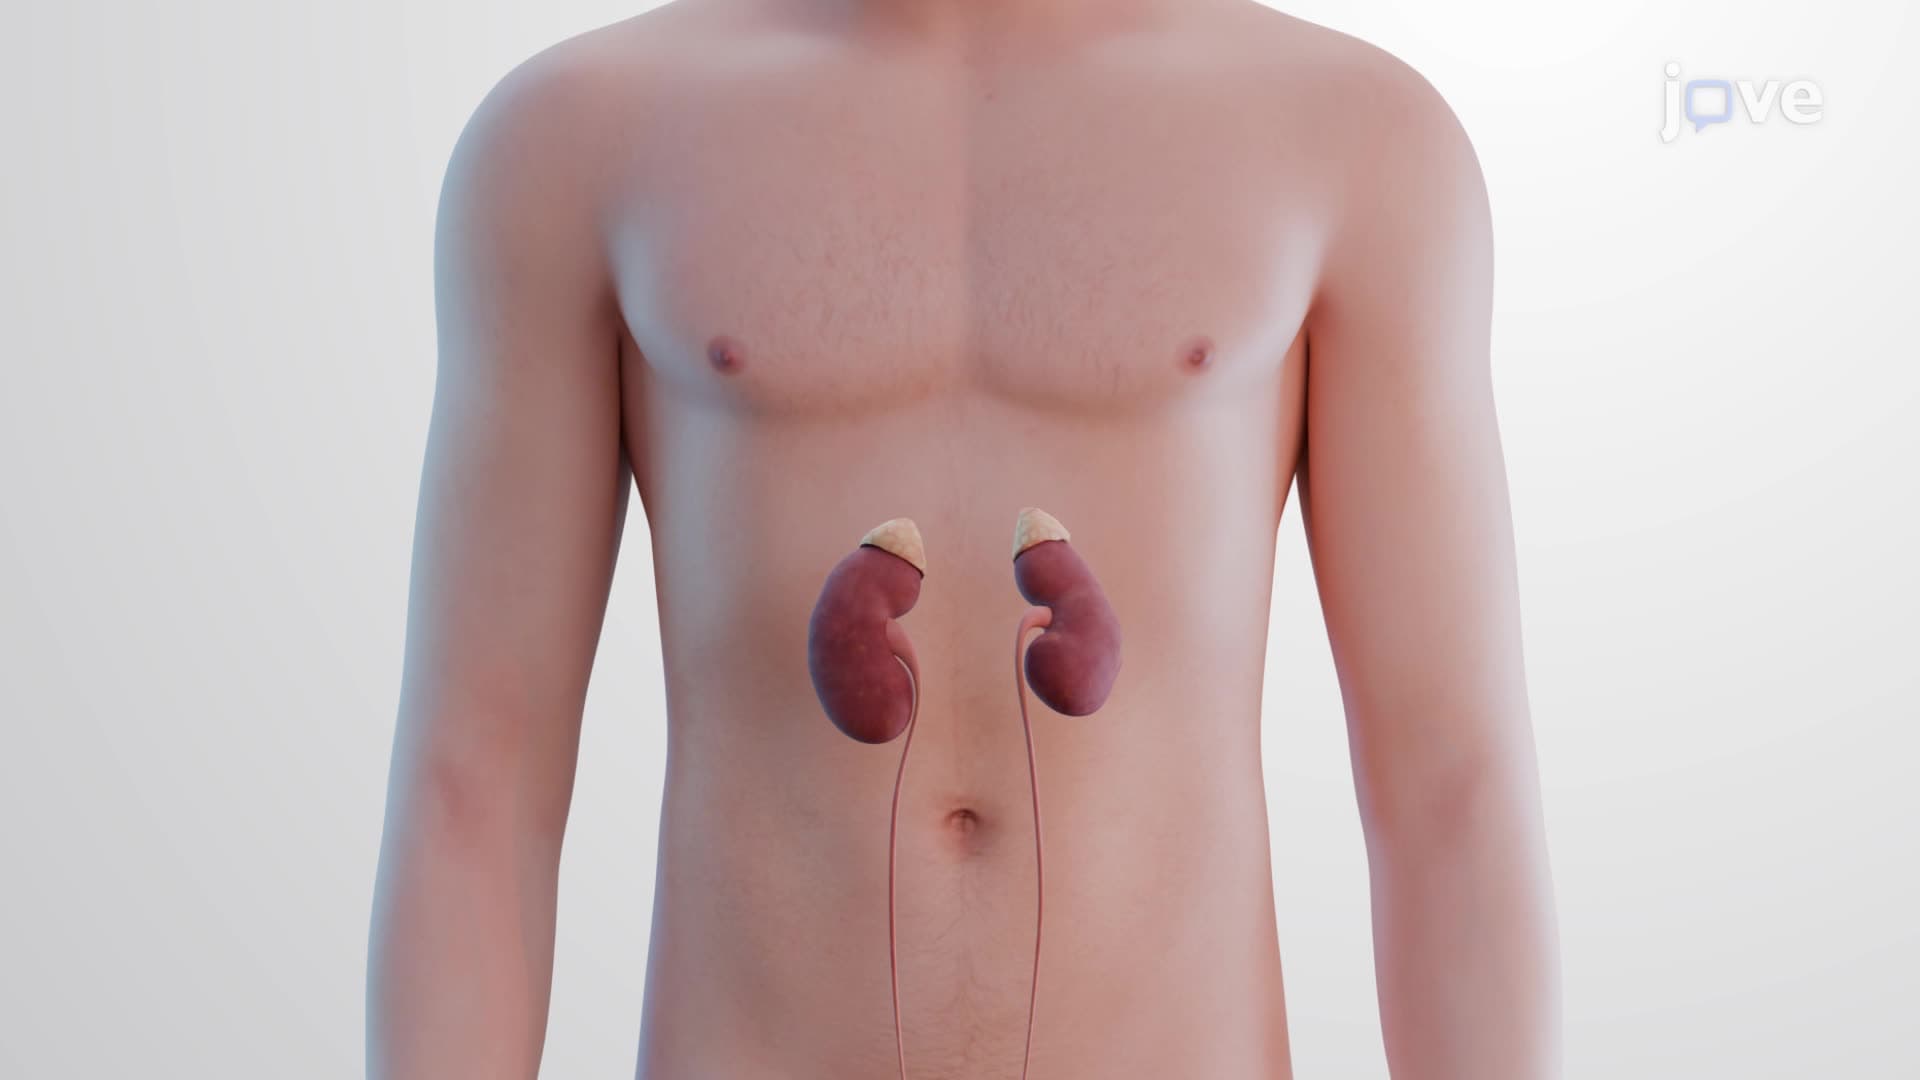
Anatomy of the Adrenal Glands
These glands possess a distinctive yellow tinge due to the stored cholesterol and fatty acids required for hormone synthesis. They are encased in a fibrous capsule and cushioned by fat.
The adrenal gland comprises two distinct regions...
 01:31
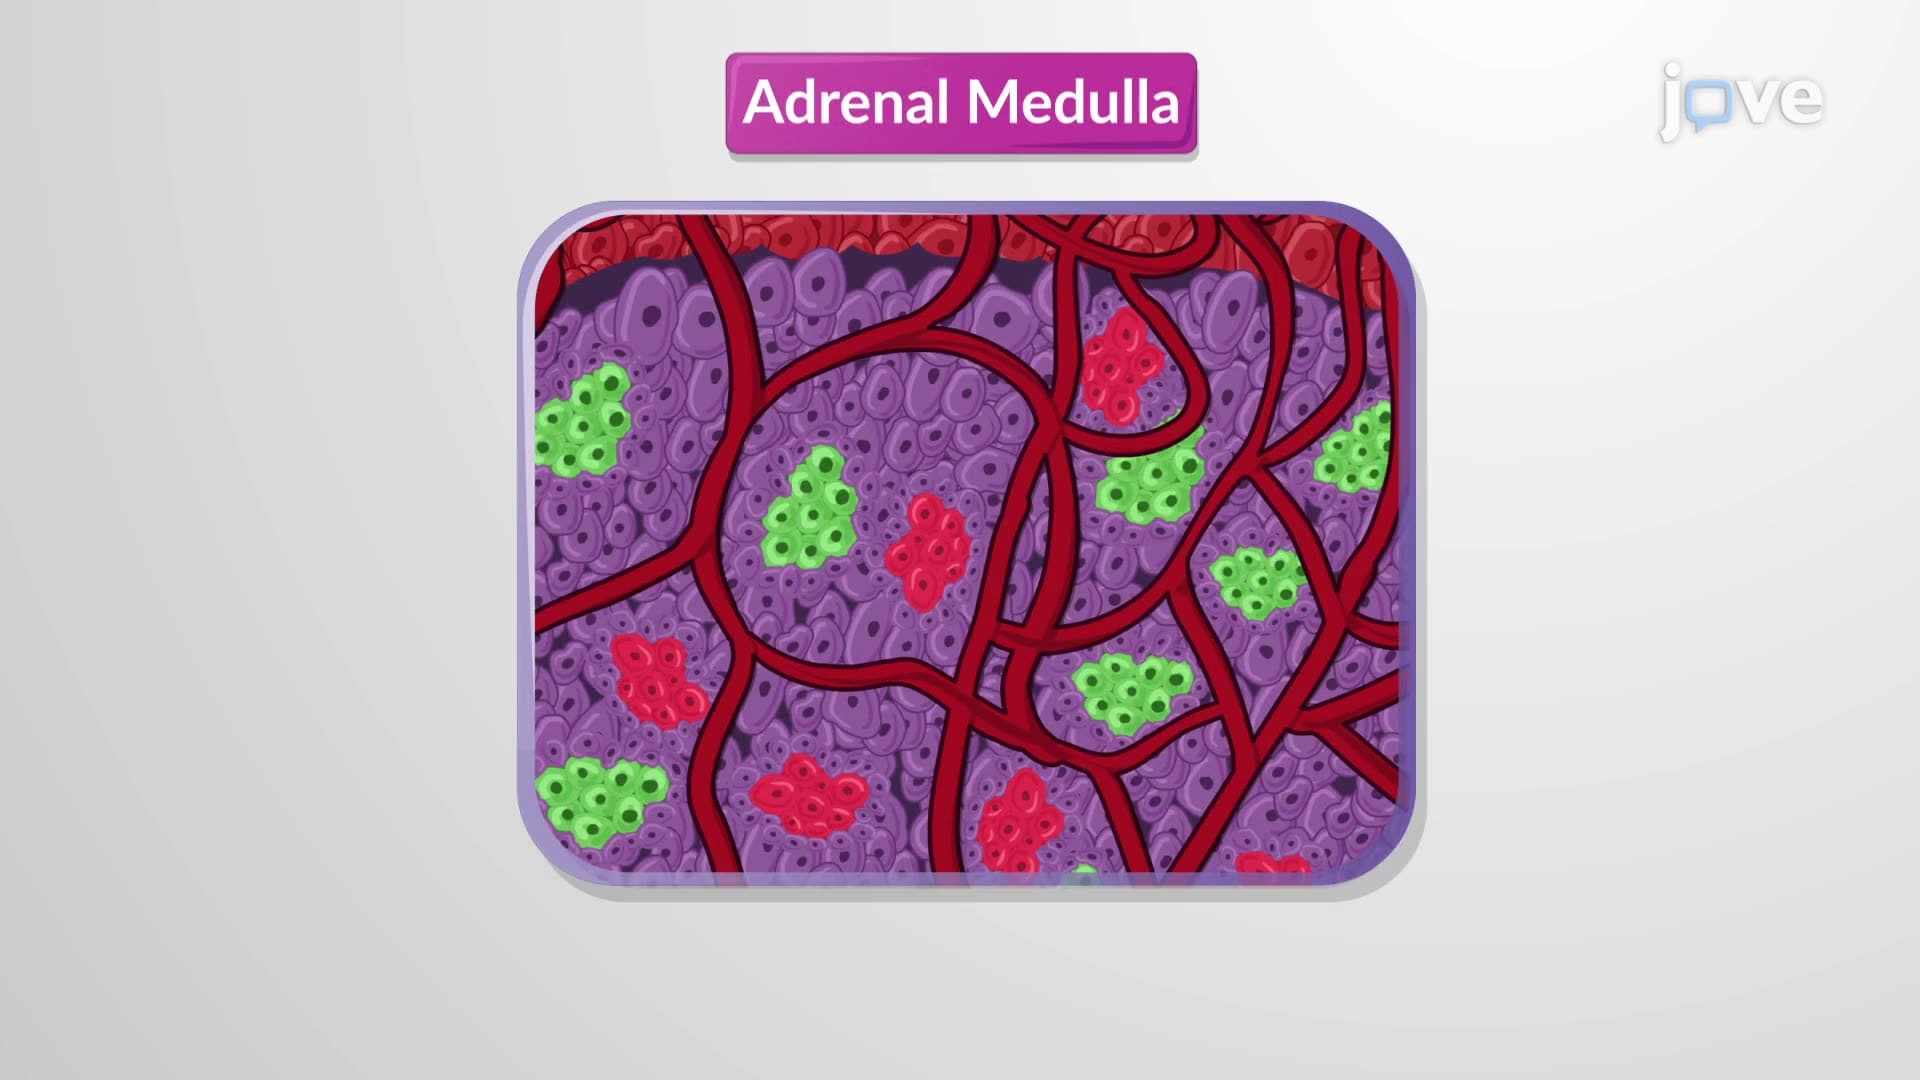
Hormones of the Adrenal Glands
The adrenal cortex, a powerhouse of hormone synthesis, generates over two dozen corticosteroid hormones. The zona glomerulosa produces mineralocorticoids, exemplified by aldosterone, influencing the electrolyte composition of body fluids. The synthesis of glucocorticoids such as cortisol and corticosterone...
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and anaphylaxis:...