Related Experiment Video
Updated: Jun 22, 2026

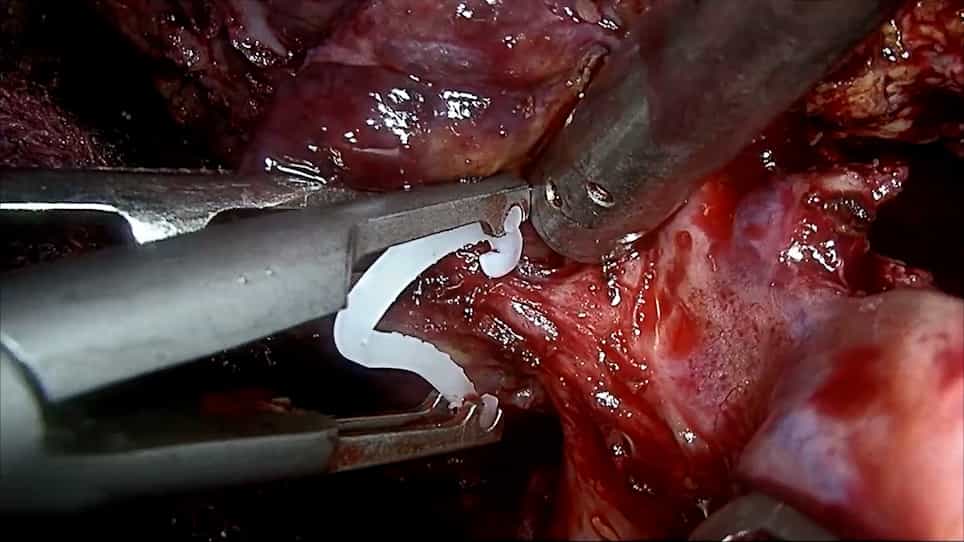
Laparoscopic Anatomic S7+S8d Resection Preserving Inferior Right Hepatic Vein and S6 with Right Hepatic Vein Transection
Published on: December 30, 2025
[Hepatic surgery. What progress? What future?]
1Service de Chirurgie Digestive, Hôpital Henri-Mondor, Université Paris-12, 94010 Créteil cedex, France.

Abstract:
Progress in liver surgery has increased the safety of all types of anatomical liver resections and has, in association with chemotherapy and interventional radiology, extended the limits of resectability for many primary and secondary liver tumors. This progress has been achieved thanks to a better method of vascular clamping, vascular reconstruction and better techniques and instruments to achieve more precise liver transection of this extremely vascular organ with a good haemostasis on the cut surface. These technical advances have allowed the procurement of partial liver grafts from living donors for transplantation and have also extended the scope of laparoscopic access to practically all types of hepatic resections. Preoperative manipulation of the liver volume with hypertrophy of the future liver remnant has made complex and extended hepatectomies feasible. These major hepatic resections are often performed in the background of damaged liver parenchyma due to chronic liver disease, steatosis and chemotherapy-induced lesions. A better knowledge of the functional anatomy with a clearer understanding of the role of venous drainage in the recovery of liver function and the process of regeneration have been the major factors which have facilitated these extended resections. The future of hepatic surgery, which is constantly influenced by the continuous technical progress with computer-aided reconstruction of the tumor zones and vascular and biliary anatomy, is certainly going to see a robotic-assisted surgical approach. Indications will change. While major and complex resections will still be required for advanced tumors, very few benign lesions will be operated in the future. Huge changes will happen in the management of malignant lesions where surgery will become a part of a combined therapeutic strategy where oncologic and radiointerventional treatments will have a major role. Surgery could then be limited to the resection of residual nodules susceptible to harbour persistent viable tumor cells.