Related Experiment Video
Updated: Jun 22, 2026

Real-Time Cardiac Mapping with a Noninvasive Imageless Electrocardiographic Imaging System
Published on: April 11, 2025
Misleading ECG appearance of AV block due to concealed AV nodal conduction caused by interpolated ventricular ectopic
Hasan Ari1, Selma Ari, Vedat Koca
1Department of Cardiology, Bursa Postgraduate Hospital, Bursa, Turkey. hasanari03@yahoo.com

Insights
Premature ventricular complexes can cause concealed conduction, leading to atrioventricular block. Metoprolol effectively treated a patient experiencing fatigue and palpitations due to this condition.
Area of Science:
- Cardiology
- Electrophysiology
Background:
- Concealed conduction, often due to interpolated ectopic impulses, affects atrioventricular (AV) node function.
- This can result in non-conduction or prolonged PR intervals of subsequent sinus beats due to AV conduction system refractoriness.
Observation:
- A 67-year-old male presented with exertional fatigue and palpitations.
- Electrocardiogram showed frequent premature ventricular complexes (PVCs) with right bundle branch block morphology.
- Holter monitoring revealed interpolated PVCs, progressive PR prolongation, and Mobitz type I atrioventricular block.
Findings:
- The patient's symptoms were directly linked to frequent interpolated PVCs causing concealed conduction and subsequent AV block.
- Treatment with metoprolol led to a significant reduction in PVCs and resolution of AV block and symptoms.
Implications:
- This case highlights the clinical significance of concealed conduction from PVCs in causing symptomatic AV block.
- Pharmacological management with beta-blockers can be effective in managing such conditions.
- Understanding this mechanism is crucial for diagnosing and treating arrhythmias involving AV nodal function.
Abstract:
Concealed conduction commonly occurs when a retrogradely conducted interpolated ectopic impulse enters the atrioventricular (AV) node; thus, the next sinus beat is not conducted to the ventricle or conducted with a prolonged PR interval because of increased refractoriness of AV conduction system. A 67-year-old man had complaints of exertional fatigue and palpitations at rest. His blood pressure was 110/70 mmHg and heart rate was 78 beats/min. Auscultation revealed a mild systolic murmur at the apex and an irregular rhythm. His electrocardiogram was normal, except for the presence of frequent premature ventricular complexes (PVC) of right bundle branch block morphology. Echocardiographic examination showed only grade-1 mitral regurgitation. Further evaluation with 24-h Holter monitoring showed frequent interpolated PVCs in bigeminal rhythm. Progressive prolongation of the PR interval was observed after each PVC, which ended with Mobitz type I AV block. The patient was treated with metoprolol which resulted in immediate and marked improvement in the symptoms. Control Holter recording showed very rare PVCs, without PR prolongation or AV block.
More Related Videos
 08:05
Optimization of Transesophageal Atrial Pacing to Assess Atrial Fibrillation Susceptibility in Mice
Published on: June 29, 2022
 06:57
Ablation of Ischemic Ventricular Tachycardia Using a Multipolar Catheter and 3-dimensional Mapping System for High-density Electro-anatomical Reconstruction
Published on: January 31, 2019
Related Concept Videos
 01:18
Dysrhythmias IV: Characteristics of Bradyarrhythmias
 01:29
Disturbances in Heart Rhythm
Arrhythmias are categorized by their speed, rhythm, and origin. A slow heart...
 01:25
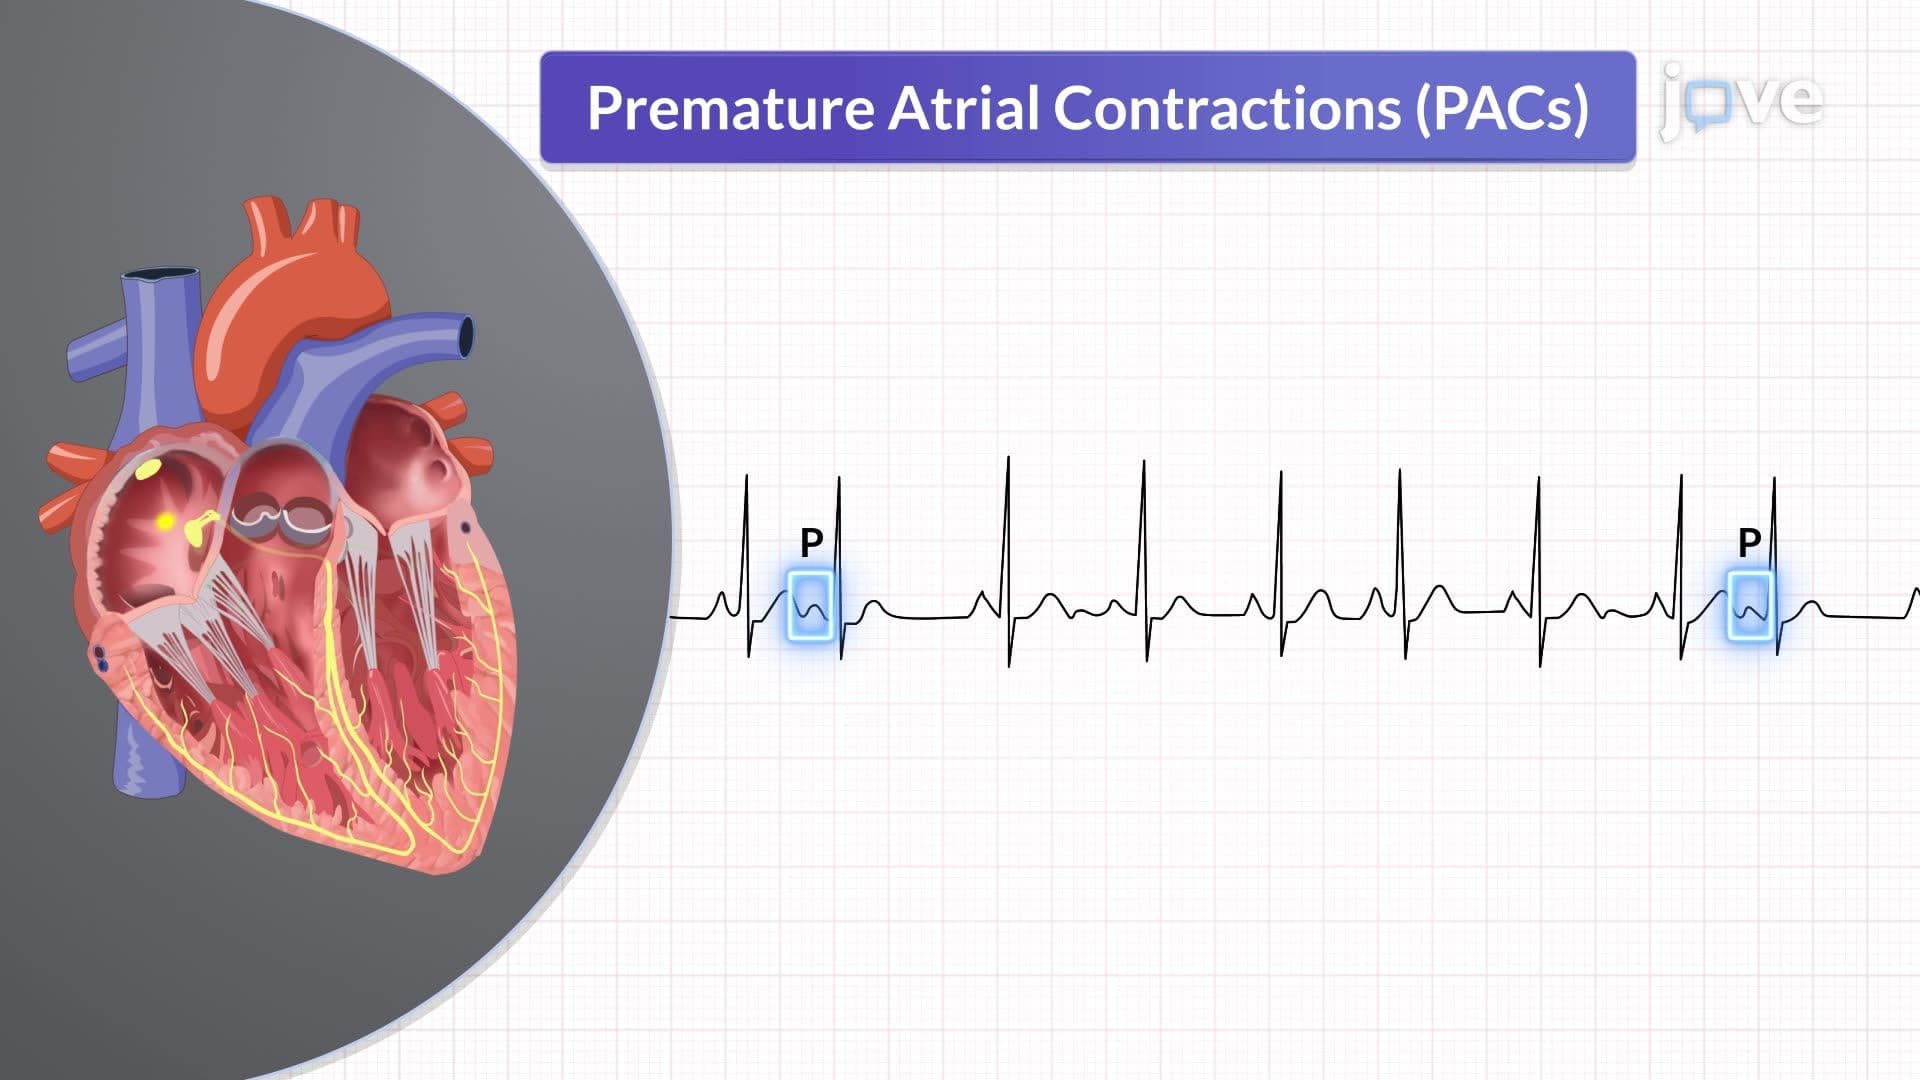
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias
 01:25
Correlation between ECG and Cardiac Cycle
A cardiac action potential originates in the SA node and spreads throughout the atria and the AV node in approximately 0.03 seconds. This results in the P wave in an ECG and triggers atrial contraction. The action potential is then briefly slowed at the AV node, allowing the atria to contract and fill the ventricles with blood before...
 01:29
Dysrhythmias III: Characteristics of Dysrhythmias
 01:28
Mechanism of Cardiac Arrhythmias