

Fundamental differences in electrophysiologic and electroanatomic substrate between ischemic cardiomyopathy patients
Haris M Haqqani1, Jonathan M Kalman, Kurt C Roberts-Thomson
1Department of Cardiology, Royal Melbourne Hospital, Grattan Street, Parkville, Victoria, Australia.

Insights
Patients with ischemic cardiomyopathy (ICM) and sustained monomorphic ventricular tachycardia (SMVT) have larger low-voltage scar areas and more conducting channels than those without SMVT. These electrophysiologic differences may explain why SMVT develops in some ICM patients but not others.
Area of Science:
- Cardiology
- Electrophysiology
- Cardiac Arrhythmias
Background:
- Ischemic cardiomyopathy (ICM) patients often have left ventricular (LV) scarring, a substrate for arrhythmias.
- The reasons why most ICM patients do not develop sustained monomorphic ventricular tachycardia (SMVT) remain unclear.
Purpose of the Study:
- To compare the electrophysiologic substrate in ICM patients with and without SMVT.
- To identify factors differentiating ICM patients who develop SMVT from those who do not.
Main Methods:
- Detailed electroanatomic mapping of the LV endocardium was performed in 17 ICM patients with SMVT and 17 control ICM patients without SMVT.
- Standard definitions for low-voltage zones and scar-related electrograms (fractionated, isolated, very late potentials) were utilized.
Main Results:
- ICM patients with SMVT had significantly larger total low-voltage areas (<1.5 mV) and very low-voltage areas (<0.5 mV) compared to controls.
- SMVT patients exhibited higher density of scar-related electrograms and more frequent conducting channels within scar tissue.
- Control patients had fewer fractionated, isolated, and very late potentials per unit low-voltage area.
Conclusions:
- ICM patients with SMVT possess a more extensive arrhythmogenic substrate characterized by larger low-voltage zones and increased scar complexity.
- Fewer conducting channels and lower scar-related electrogram density in control ICM patients may contribute to their lack of SMVT development.
- These findings provide insights into the substrate responsible for SMVT in ICM and explain inter-patient variability.
Objectives:
The aim of this study was to compare the electrophysiologic substrate in ischemic cardiomyopathy (ICM) patients with and without sustained monomorphic ventricular tachycardia (SMVT).
Background:
Despite the universal presence of potentially arrhythmogenic left ventricular (LV) scarring, it is not clear why the majority of ICM patients never develop SMVT.
Methods:
Detailed electroanatomic mapping of the LV endocardium was performed in 17 stable control ICM patients (16 males) without clinical SMVT. They were compared with 17 ICM patients (15 males) with spontaneous SMVT. Standard definitions of low-voltage zones and fractionated, isolated, and very late potentials were used.
Results:
There were no significant baseline differences between the groups in terms of LV diameter, ejection fraction (27% vs. 28%), infarct territory, or time from infarction. However, control patients had smaller total low-voltage area < or =1.5 mv (30% of surface area vs. 55%, p < 0.001); smaller very low-voltage area <0.5 mv (7.3% vs. 29%, p < 0.001); higher mean voltage of low-voltage zones; fewer fractionated, isolated, and very late potentials with lower density of these scar-related electrograms per unit low-voltage area; and less SMVT inducibility. Potential conducting channels within dense scar and adjacent to the mitral annulus were more frequent in SMVT patients.
Conclusions:
Compared with ICM patients with SMVT, an otherwise similar control group demonstrated markedly smaller endocardial low-voltage zones, lower scar-related electrogram density, and fewer conducting channels with faster conduction velocity. These findings may explain why some ICM patients develop SMVT and others do not.


Related Concept Videos
 01:29
Dysrhythmias III: Characteristics of Dysrhythmias
 01:19
Electrophysiology of Normal Cardiac Rhythm
 01:30
Cardiac Action Potential
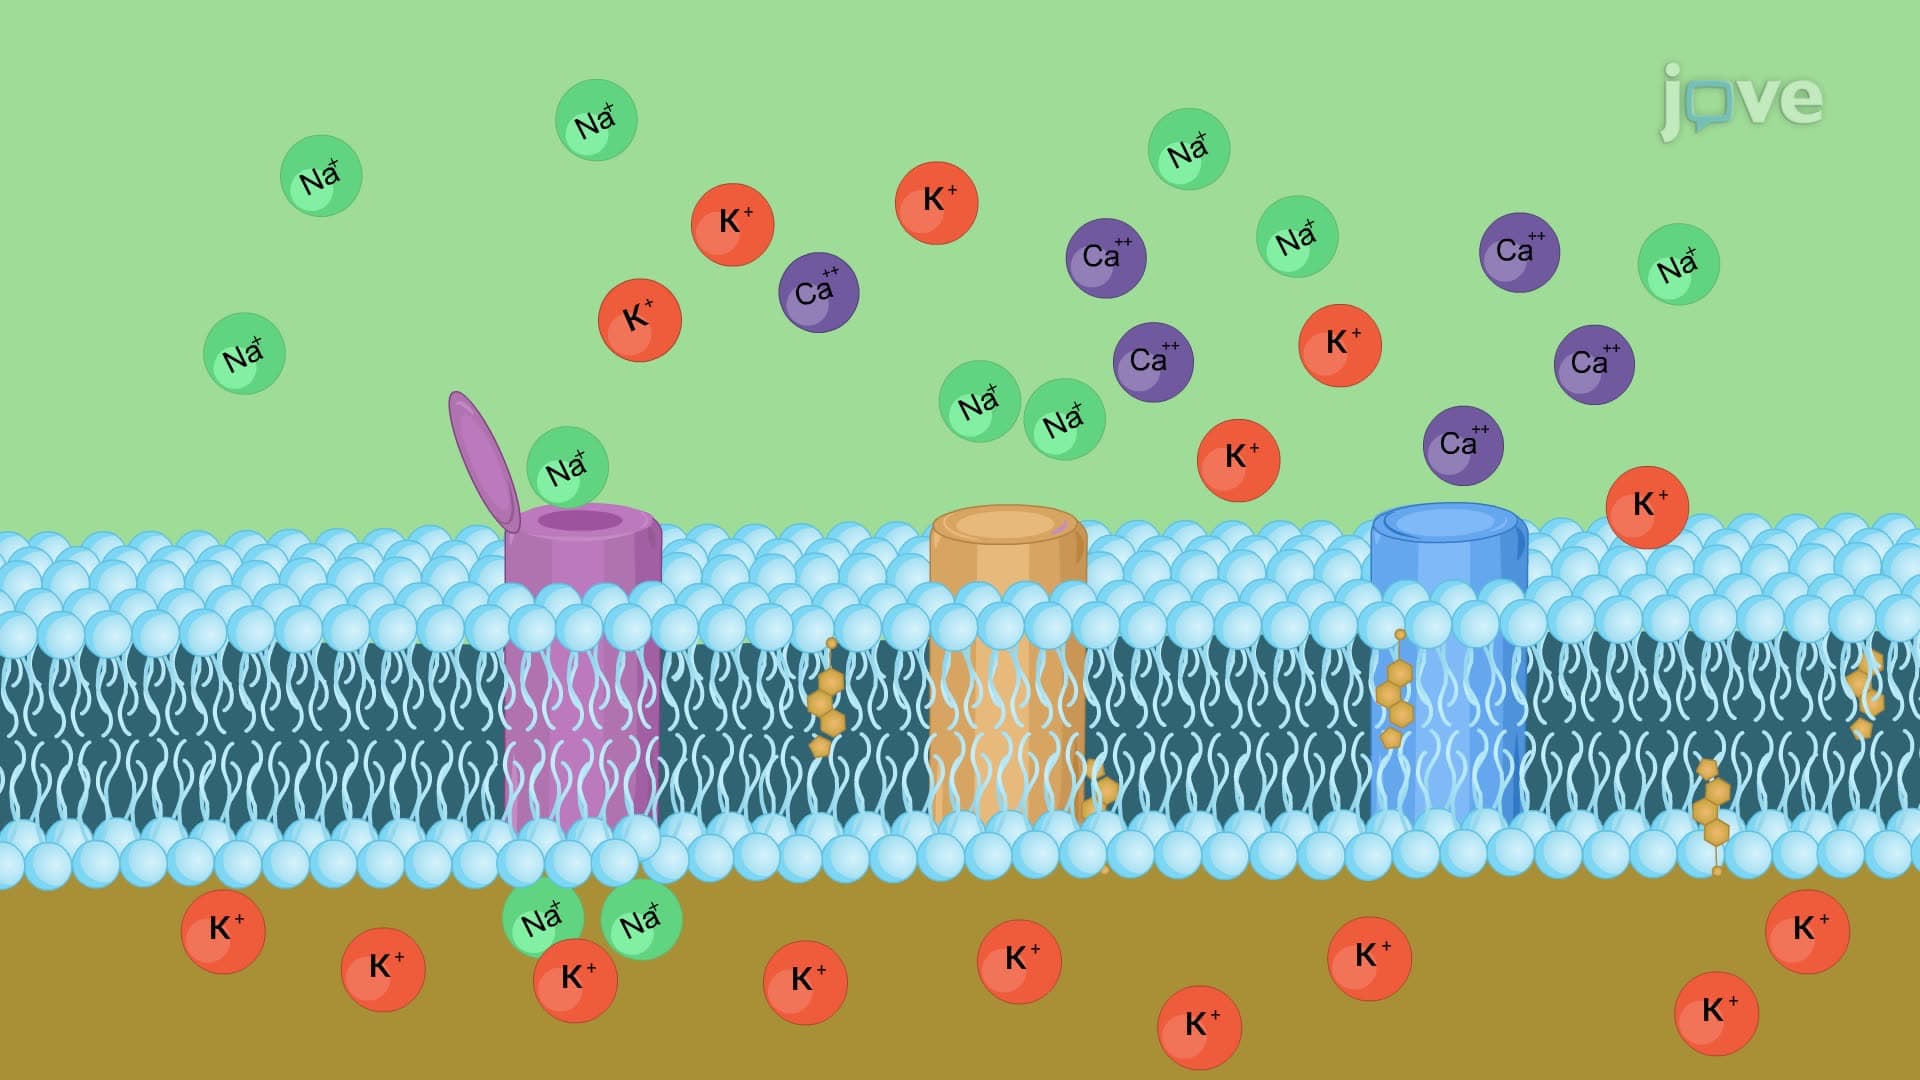
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials
 01:28
Mechanism of Cardiac Arrhythmias
 01:28
Dysrhythmias II: Classification of Tachyarrhythmias
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias