Related Experiment Video
Updated: Jun 21, 2026
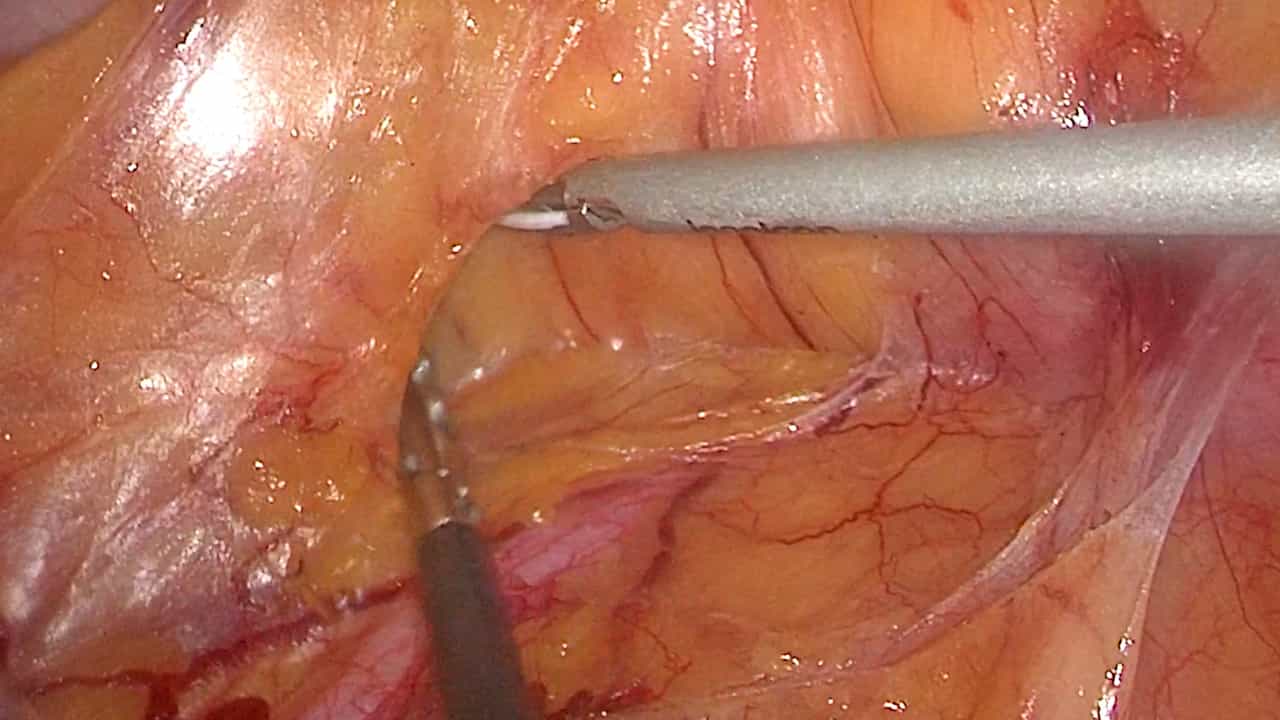

Caudal-to-cranial Approach in Laparoscopic Right Hemicolectomy with Complete Mesocolon Excision and D3 Lymph Node Dissection
Published on: January 9, 2026
Optimizing the approach for lymph node dissection during laparoscopic radical cystectomy
Ahmed Ghazi1, Reinhold Zimmermann, Amjad Al-Bodour
1Urology Department, Krankenhaus der Elisabethinen, Linz, Austria. ahmed_ghazimd@yahoo.com

Background:
Lymph node dissection (LND) for muscle-invasive bladder cancer is one of the integral steps of radical cystectomy. In addition to staging, adequate LND has been found to alter both the prognosis for and the course of the disease after radical cystectomy.
Objective:
To point out several essential steps that provide optimal exposure for LND during laparoscopic radical cystectomy for muscle-invasive bladder cancer.
Design, Setting And Participants:
From August 2006 to September 2008, we performed 10 laparoscopic cystectomies with an extended LND using this approach at our institution. Patient and tumor characteristics, the anatomic extent of the LND, the number of lymph nodes examined, and the postoperative complications encountered were evaluated.
Surgical Procedure:
Essential steps include (1) a modified five-trocar arrangement; (2) use of a 30 degrees telescope during LND; (3) prior complete mobilization of the sigmoid colon, allowing its retraction using an umbilical tape; (4) accomplishment of most of the bilateral LND from the right side; and (5) performance of LND after removal of the specimen.
Measurements:
The primary end points were adequate intraoperative exposure of the template and number of lymph nodes retrieved. The secondary end point was evaluation of postoperative lymph node recurrence as an assessment of a complete LND.
Results And Limitations:
Mean total operative time was 512.5 min (range: 420-660), with a mean operative time of 143 min (range: 115-165) for the extended LND. Adequate exposure was successful in all 10 patients. The average number of lymph nodes examined was 25.5 (range: 19-32), with 4 nodes positive for metastasis. No patients had pelvic or lymph node metastasis at a mean follow-up of 14.8 mo (range: 4-30). Limitations included an analysis of a small series of patients.
Conclusions:
This new approach provides optimal exposure for an adequate laparoscopic LND during radical cystectomy, without any compromise.