Related Experiment Video
Updated: Jun 21, 2026


Endoscopic Ultrasound-Guided Biliary Drainage: Endoscopic Ultrasound-Guided Hepaticogastrostomy in Malignant Biliary Obstruction
Published on: March 25, 2022
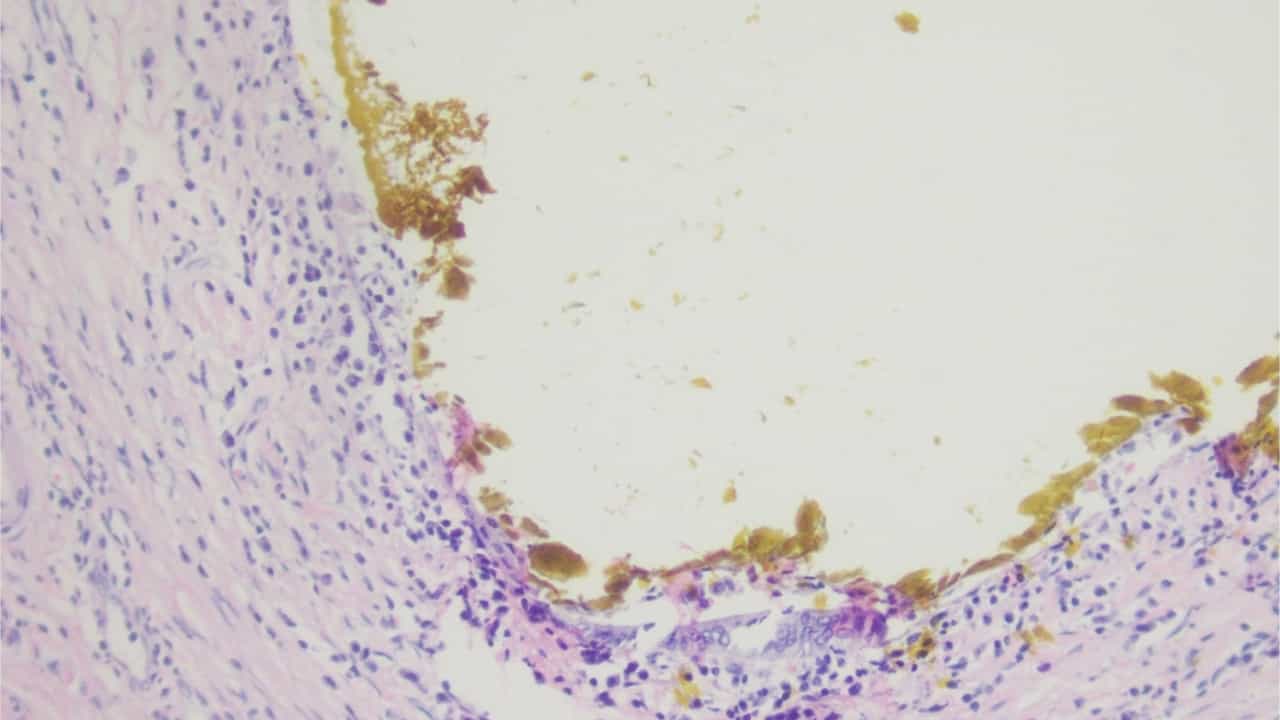
Inflammatory pseudotumor in the liver associated with intrahepatic bile duct stones mimicking malignancy
Junji Ueda1, Hiroshi Yoshida, Nobuhiko Taniai
1Surgery for Organ Function and Biological Regulation, Graduate School of Medicine, Nippon Medical School, Tokyo, Japan.

Abstract:
We describe a 71-year-old man with an inflammatory tumor arising in segment 5 of the liver. The patient was admitted because of acute pain in the right upper quadrant of the abdomen and fever. Initial laboratory tests revealed the following: serum alkaline phosphatase concentration, 634 IU/L; serum gamma glutamic transpeptidase concentration, 1,378 IU/L; serum C-reactive protein concentration, 0.89 mg/dL; and total bilirubin concentration, 8.9 mg/dL. Abdominal ultrasonography, computed tomography (CT), and magnetic resonance imaging showed a mass, 3 cm in diameter, in segment 5 of the liver. Magnetic resonance cholangiopancreatography showed a lesion of moderate-to-high signal intensity on T2-weighted images of segment 5. Endoscopic retrograde cholangiopancreatography revealed a common bile duct stone. The intrahepatic bile ducts of segment 5 could not be visualized after the use of contrast material. Endoscopic sphincterotomy was performed to remove the common bile duct stone. Antibiotics were administered soon after stone removal, and fever gradually resolved. Positron emission tomography revealed hot spots in segment 5 of the liver. Three weeks after discharge, the patient was readmitted with an acute pain in the right upper quadrant of the abdomen. Abdominal ultrasonography, CT, and magnetic resonance imaging showed enlargement of this area. Inflammatory changes of segment 5 due to cholangitis with intrahepatic bile duct stones was diagnosed. Because malignant disease could not be completely ruled out, segment 5 of the liver was resected. Macroscopic examination of the resected specimen revealed a gray, fibrotic, solid tumor associated with intrahepatic bile duct stones. Microscopic examination of the tumor showed proliferation of spindle-shaped myofibroblastic cells in a mixed myxoedematous, dense fibrotic stroma, associated with infiltration by various acute and chronic inflammatory cells. The postoperative course was uneventful, and the patient was discharged on postoperative day 16.
More Related Videos
 05:22
Intraoperative Strategy under Complex Vascular Adhesion for Laparoscopic Radical Resection of Bismuth-Corlette Type IIIb Perihilar Cholangiocarcinoma
Published on: February 13, 2026
 03:33
Laparoscopic Left Lateral Sectionectomy: Guided by the Ligamentum Teres Hepatis and the Umbilical Fissure Vein
Published on: September 27, 2024
Related Concept Videos
 01:20
Cholecystitis
 01:19
Appendicitis
 01:26
Diseases of the Liver and Gallbladder
Cirrhosis is characterized by the scarring of hepatic lobules in the liver, which are replaced by fibrous tissue, affecting the liver's normal functioning. NAFLD, on the other hand, is caused by an excessive build-up of fat in the liver, not related to...
 01:17
Chronic Bowel Disorders: Introduction
Irritable Bowel Syndrome (IBS) is a common disorder affecting the gastrointestinal tract. The distinctive feature is recurrent abdominal pain associated with altered bowel movements, manifesting as constipation, diarrhea, or fluctuating between both. The...
 01:24
Cirrhosis II: Pathophysiology
 01:27
Inflammatory Bowel Disease I: Ulcerative Colitis
Inflammatory bowel disease, or IBD, encompasses a group of disorders characterized by chronic inflammation or ulceration of the gastrointestinal tract.
Risk Factors
The exact cause of IBD remains unclear, although it is believed to be due to a mix of genetic, environmental, microbial, and immune factors. Genetic factors are significant in determining susceptibility to IBD, with family history being a critical risk factor. Individuals with a first-degree relative who has IBD are at...