Related Experiment Video
Updated: Jun 21, 2026
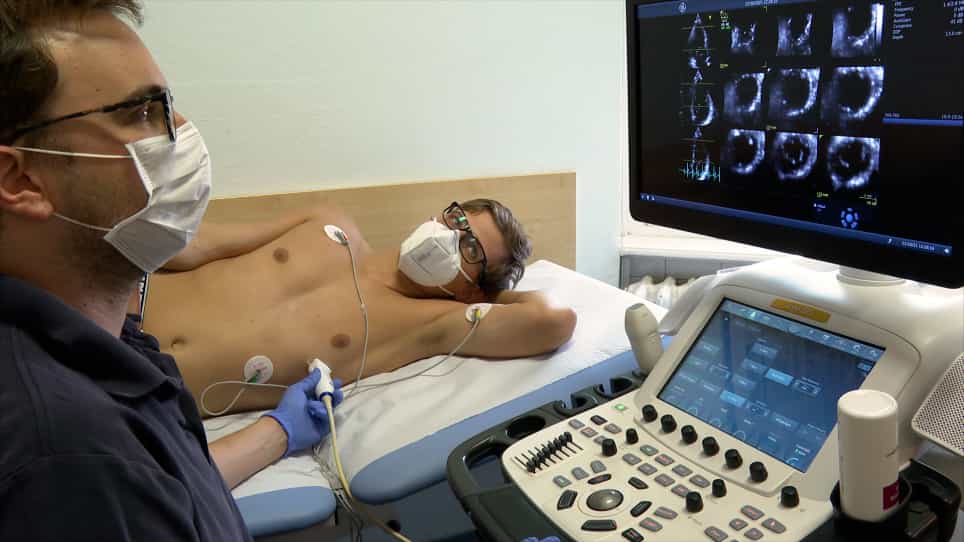
Evaluation of Left Ventricular Structure and Function using 3D Echocardiography
Published on: October 28, 2020
Real-time 3-dimensional echocardiographic assessment of left ventricular dyssynchrony: pitfalls in patients with
Carolin Sonne1, Lissa Sugeng, Masaaki Takeuchi
1University of Chicago Medical Center, Chicago, Illinois 60637, USA.

Insights
Real-time 3-dimensional echocardiography (RT3DE) derived left ventricular (LV) dyssynchrony index (LVDI) values are age-dependent and differ between normal subjects and dilated cardiomyopathy (DCM) patients. Current RT3DE-LVDI assessment needs critical reassessment for patients with reduced LV function.
Area of Science:
- Cardiology
- Medical Imaging
- Echocardiography
Background:
- Cardiac resynchronization therapy (CRT) is ineffective in a significant portion of heart failure patients.
- There is a need for improved methods to assess left ventricular (LV) dyssynchrony.
- Real-time 3-dimensional echocardiography (RT3DE) offers potential for LV dyssynchrony assessment.
Purpose of the Study:
- Establish normal values for RT3DE-derived LV dyssynchrony index (LVDI).
- Determine the age dependency of LVDI.
- Compare LV dyssynchrony in patients with normal LV function and dilated cardiomyopathy (DCM), with and without left bundle branch block (LBBB).
Main Methods:
- RT3DE datasets were analyzed to calculate LVDI using 16- and 17-segment models.
- 135 normal subjects were studied to establish LVDI abnormality thresholds and age-related changes.
- Three patient groups (DCM with/without LBBB, normal LV function with LBBB) were compared to age-matched controls.
Main Results:
- The 16-segment model yielded a lower LVDI abnormality threshold than the 17-segment model (4.0% vs. 4.5%).
- LVDI was significantly lower in patients with normal LV function compared to DCM patients, regardless of LBBB.
- LBBB increased LVDI in normal LV function but not in DCM; all DCM patients with ejection fraction <35% had abnormally high LVDI.
Conclusions:
- Established normal LVDI values led to indiscriminate diagnosis of abnormal dyssynchrony in patients with reduced LV function.
- RT3DE-derived LVDI's utility in evaluating dyssynchrony in reduced LV function requires reassessment due to end-ejection detection issues.
- Development of alternative dyssynchrony indices is necessary to overcome current limitations.
Objectives:
This study sought to establish normal values for real-time 3-dimensional echocardiography (RT3DE)-derived left ventricular (LV) dyssynchrony index (LVDI) and determine its age dependency, and to compare dyssynchrony in patients with normal LV function and patients with dilated cardiomyopathy (DCM), with and without left bundle branch block (LBBB).
Background:
Cardiac resynchronization therapy is known to be ineffective in one-third of patients with heart failure, highlighting the need for alternative techniques to assess LV dyssynchrony.
Methods:
Datasets from RT3DE were analyzed to calculate LVDI using 16- and 17-segment models. First, 135 normal subjects were studied to establish LVDI abnormality threshold (mean + 2 SD) and to study the relationship with age. Then, 3 groups of patients (N = 16 each: DCM with and without LBBB, normal LV function with LBBB) were compared with 50 age-matched normal control subjects.
Results:
In normal subjects, the 16-segment model resulted in a lower LVDI abnormality threshold than the 17-segment model (4.0% vs. 4.5%). In patients with normal LV function, LVDI was significantly lower than in those with DCM, irrespective of LBBB. Although LBBB resulted in a nearly 2-fold increase in LVDI in patients with normal LV function, its effects were nonsignificant in DCM. All patients with DCM and ejection fraction <35% had abnormally high LVDI, likely as a result of low signal-to-noise ratio in low-amplitude regional volume curves hampering accurate determination of regional ejection time.
Conclusions:
Normal values established in this study resulted in indiscriminate diagnosis of abnormal dyssynchrony in all patients with reduced LV function. The value of RT3DE-derived LVDI in the evaluation of dyssynchrony in patients with reduced LV function needs to be critically reassessed because of the inability to accurately detect end-ejection in low-amplitude regional volume curves. Alternative indices of dyssynchrony need to be developed to address this limitation.
Related Concept Videos
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:17
Imaging Studies for Cardiovascular System I:Echocardiography
Indications: Echocardiography is utilized to diagnose heart failure, valve disorders, and myocardial infarction. It also assesses cardiac structures' size, shape, and motion, evaluates...
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:30
Dysrhythmias V: Evaluating Dysrhythmias