[The clinical and pathological characteristics of a patient with glycogen storage disease IV]

Sheng Yao1, Xiao-kun Qi, Bin Xiong

  • 1Department of Neurology, Navy General Hospital, Beijing 100037, China.

Abstract

Related Concept Videos

Type I Diabetes III: Clinical Manifestations01:19

Type I Diabetes III: Clinical Manifestations

Type 1 diabetes mellitus typically presents with rapid-onset symptoms due to the body’s inability to utilize glucose in the absence of insulin. Since insulin is required for glucose uptake into cells, its deficiency leads to hyperglycemia and cellular energy deprivation, resulting in characteristic clinical features.Polyuria and PolydipsiaOne of the earliest, most prominent symptoms is polyuria (excessive urination). When blood glucose concentrations rise above the renal threshold, the kidneys...
Type II Diabetes Mellitus III: Clinical Manifestations and Diagnosis01:25

Type II Diabetes Mellitus III: Clinical Manifestations and Diagnosis

Type 2 diabetes mellitus develops gradually and is often asymptomatic in early stages.Clinical ManifestationsWhen symptoms appear, they include fatigue, blurred vision, pruritus, delayed wound healing, and recurrent infections, particularly candidal infections. Peripheral neuropathy may present as numbness or tingling in the extremities. Classic hyperglycemia symptoms—polyuria, polydipsia, and polyphagia—are less common. Most patients are overweight and frequently have associated hypertension...
Lysosomal Hydrolases01:22

Lysosomal Hydrolases

Lysosomes are the site for the degradation of macromolecules and biological polymers released during membrane trafficking events such as secretory, endocytic, autophagic, and phagocytic pathways. The membrane-enclosed area of the lysosome, called the lumen, contains hydrolytic enzymes active in an acidic environment. These acid hydrolases are functional at a pH between 4.5 and 5 and are involved in cellular processes such as cell signaling, energy metabolism, restoration of the plasma membrane,...
Type I Diabetes II: Pathophysiology01:26

Type I Diabetes II: Pathophysiology

Type 1 diabetes mellitus arises from an immune-mediated destruction of pancreatic β-cells, resulting in an absolute deficiency of insulin. This process develops in genetically susceptible individuals when autoimmunity, environmental exposures, and immunologic dysregulation converge to trigger a targeted attack on the insulin-producing cells of the pancreas. The β-cells are located within the islets of Langerhans and are essential for regulating blood glucose by facilitating cellular uptake of...
Type II Diabetes II: Pathophysiology01:24

Type II Diabetes II: Pathophysiology
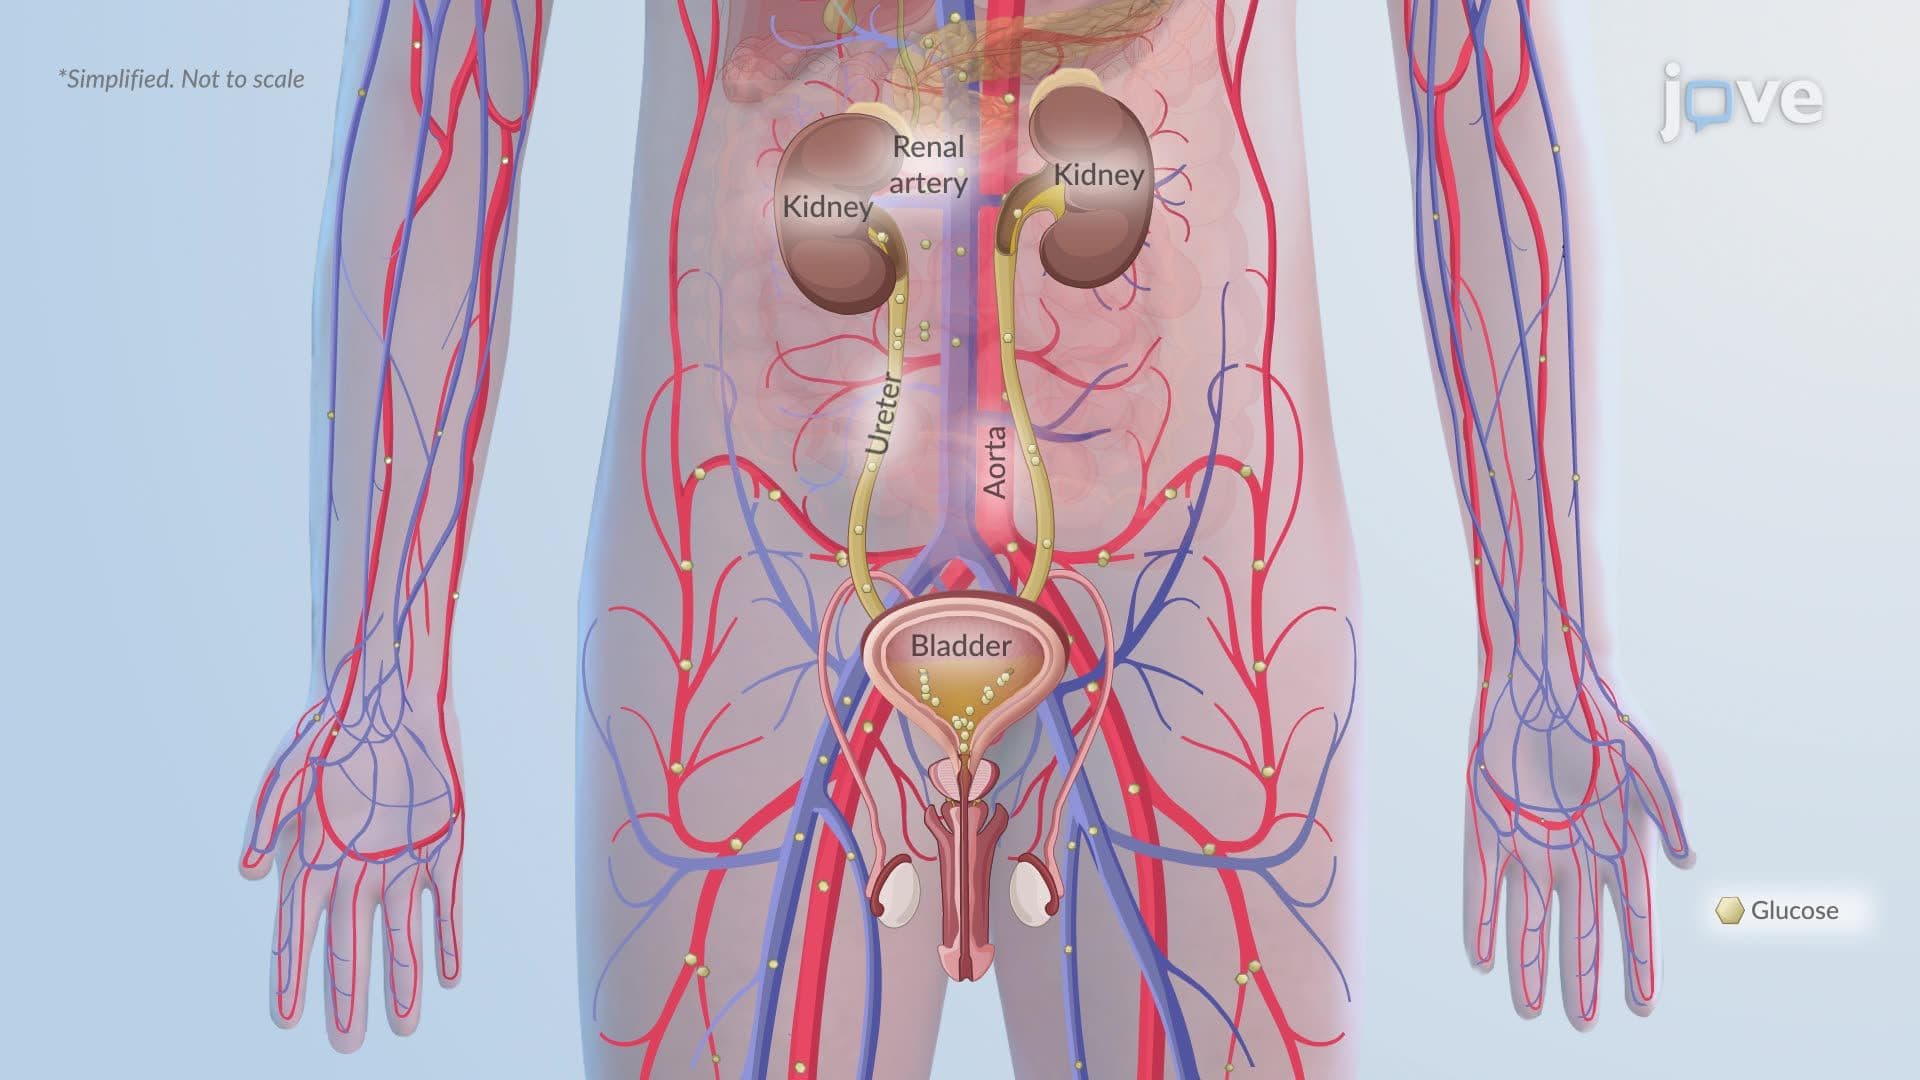
PathophysiologyType 2 diabetes mellitus (T2DM ) is a chronic metabolic disorder characterized by insulin resistance and progressive pancreatic β-cell dysfunction, leading to impaired glucose homeostasis. It results from interactions among genetic predisposition, environmental factors, and metabolic stressors, such as overnutrition and a sedentary lifestyle.Insulin Resistance and Glucose DysregulationEarly T2DM involves insulin resistance in skeletal muscle, adipose tissue, and the liver.
Diabetic Ketoacidosis ll: Pathophysiology01:22

Diabetic Ketoacidosis ll: Pathophysiology

Diabetic ketoacidosis (DKA) is a metabolic emergency characterized by hyperglycemia, ketonemia, and metabolic acidosis. It results from severe insulin deficiency and an excess of counterregulatory hormones, leading to uncontrolled lipolysis, ketogenesis, and widespread electrolyte and fluid disturbances.Pathophysiology The central event in DKA is a profound loss of insulin action. Without insulin, glucose uptake in insulin-dependent tissues is impaired, while hepatic glucose production...