Related Experiment Video
Updated: Jun 21, 2026

Assessment of the Metabolic Effects of Isocaloric 2:1 Intermittent Fasting in Mice
Published on: November 27, 2019
Fasting and postprandial relationships among plasma leptin, ghrelin, and insulin in prepubertal obese children
M Gil-Campos1, C M Aguilera, M C Ramirez-Tortosa
1Unit of Paediatric Endocrinology, Reina Sofia University Hospital, Avda Menéndez Pidal s/n, 14004 Córdoba, Spain. mercedes_gil_campos@yahoo.es

Background:
Leptin is involved in the long-term regulation of body weight and dietary intake, while ghrelin plays an essential role in appetite control. High levels of leptin have been associated with adiposity and the suppression of ghrelin levels with increased dietary intake.
Aims:
To evaluate fasting and postprandial concentrations of plasma leptin and ghrelin after intake of a standardised breakfast and to study the relationship of these hormones with adiposity and insulin resistance in obese prepubertal children.
Methods:
34 obese and 20 normal-weight prepubertal children aged 6-12 years were selected. Plasma leptin and ghrelin were measured by ELISA and radioimmunoassay, respectively. The general linear model of variance, principal-component factor, and Pearson's analyses correlation were performed.
Results:
Baseline and postprandial leptin levels were higher in obese versus normal-weight children. In obese, ghrelin showed an altered pattern during the postprandial period, recovering to baseline levels at 3h after the intake. Insulin resistance was associated with leptin and independently with ghrelin.
Conclusion:
The association of ghrelin with insulin resistance provides further evidence on the regulation of ghrelin in glucose homeostasis in childhood obesity at the prepubertal age. Changes in ghrelin after dietary intake may be related to an earlier recovery of appetite in prepubertal obese children.
More Related Videos


Related Concept Videos
 01:25
Pharmacokinetics in Obese Patients: Drug Absorption and Distribution
 01:24
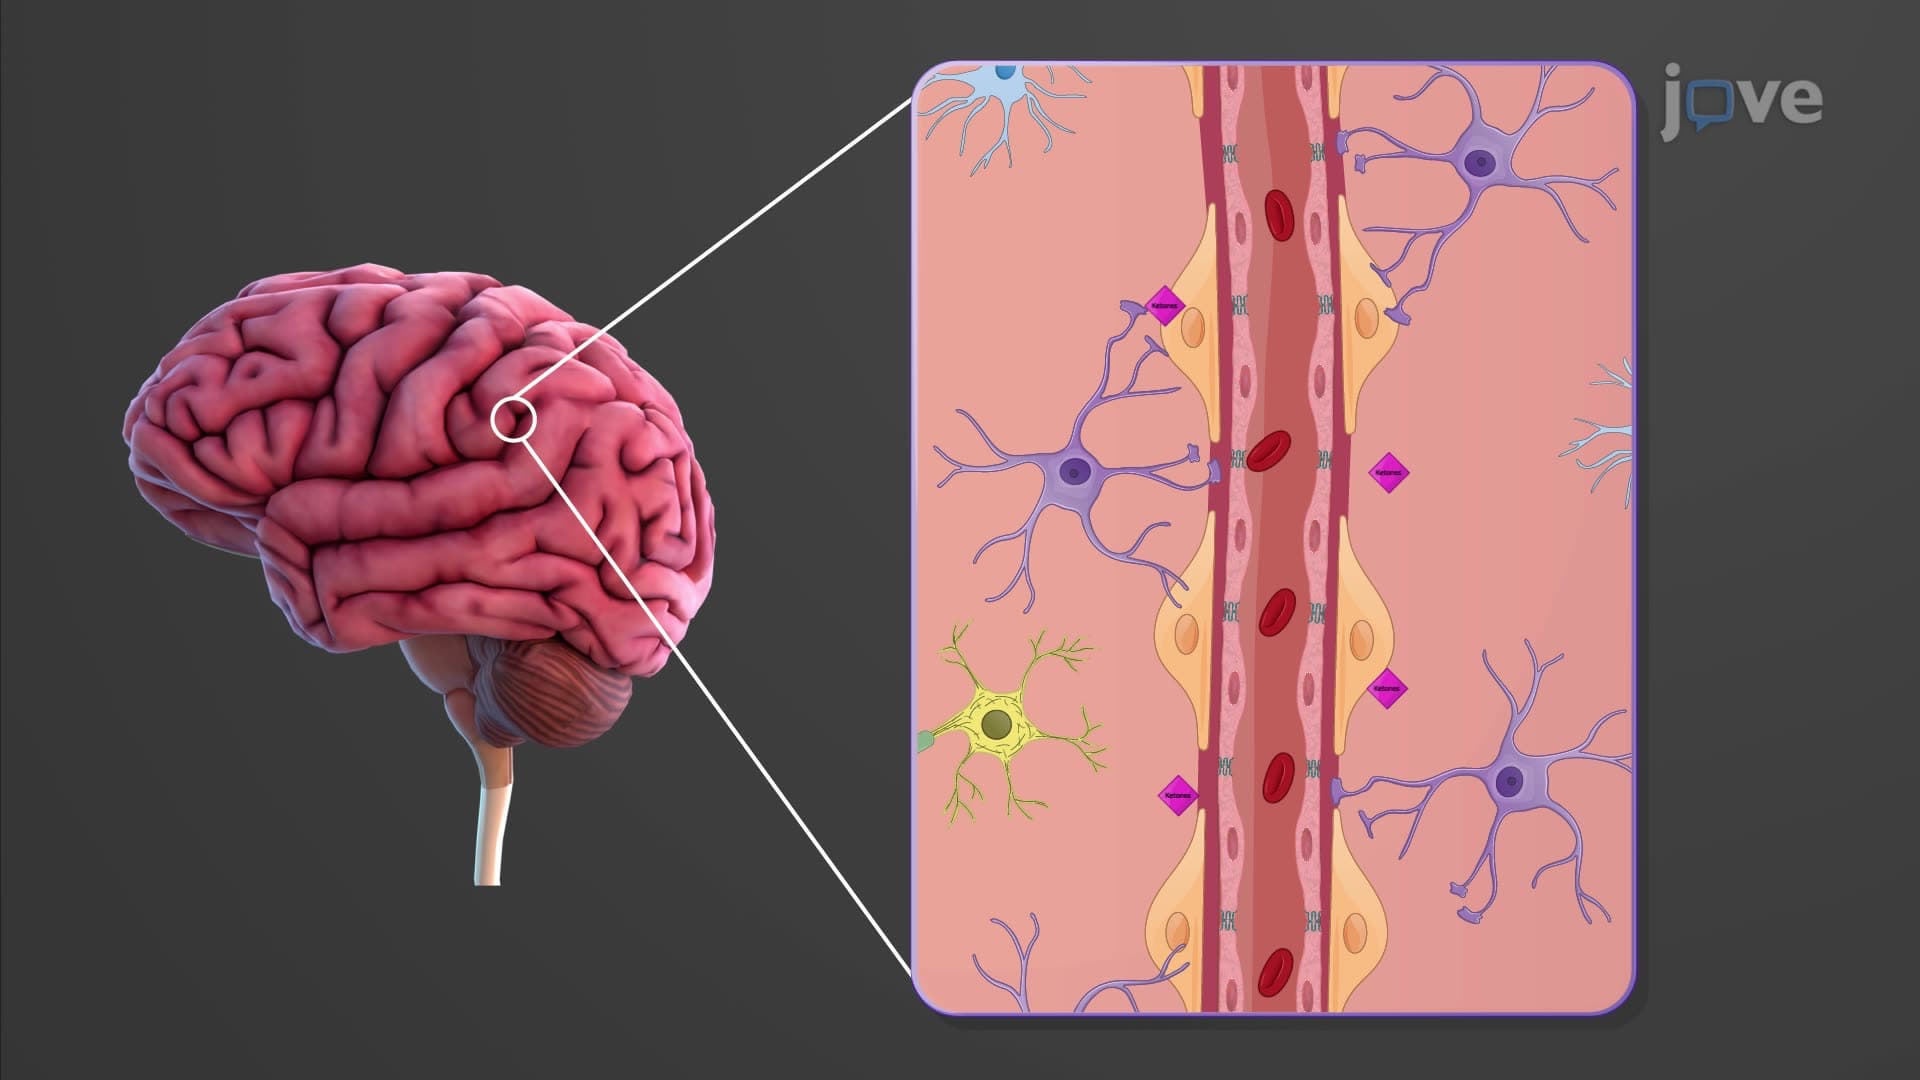
Metabolic States of the Body: Fasting and Starvation
 01:18
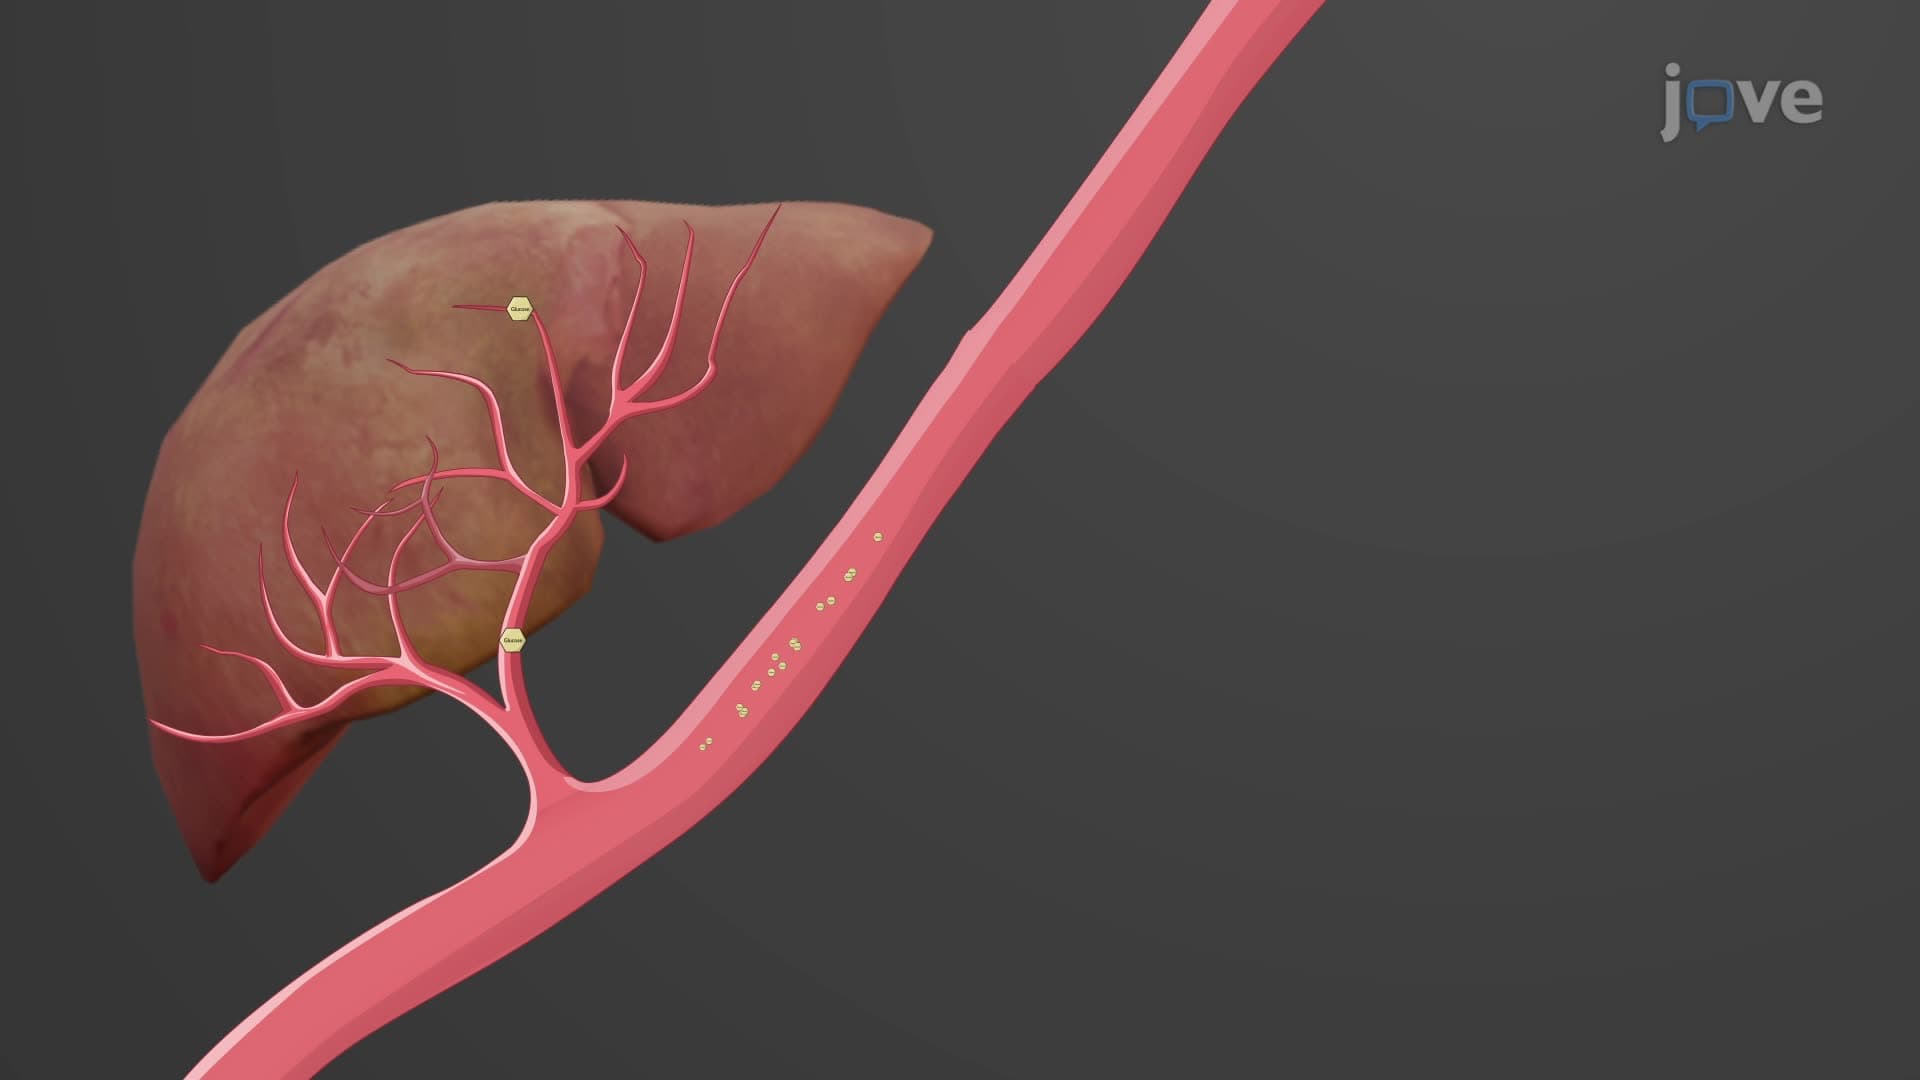
Metabolic States of the Body: The Postabsorptive State
Initially, glycogen stored in the liver is broken down to release glucose into the bloodstream, while glycogen in the muscles is broken down to supply glucose for energy directly within the muscle cells. As glycogen stores diminish,...
 01:20
Pharmacokinetics in Obese Patients: Drug Metabolism and Excretion
 01:24
Obesity
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...