Related Experiment Video
Updated: Jun 21, 2026
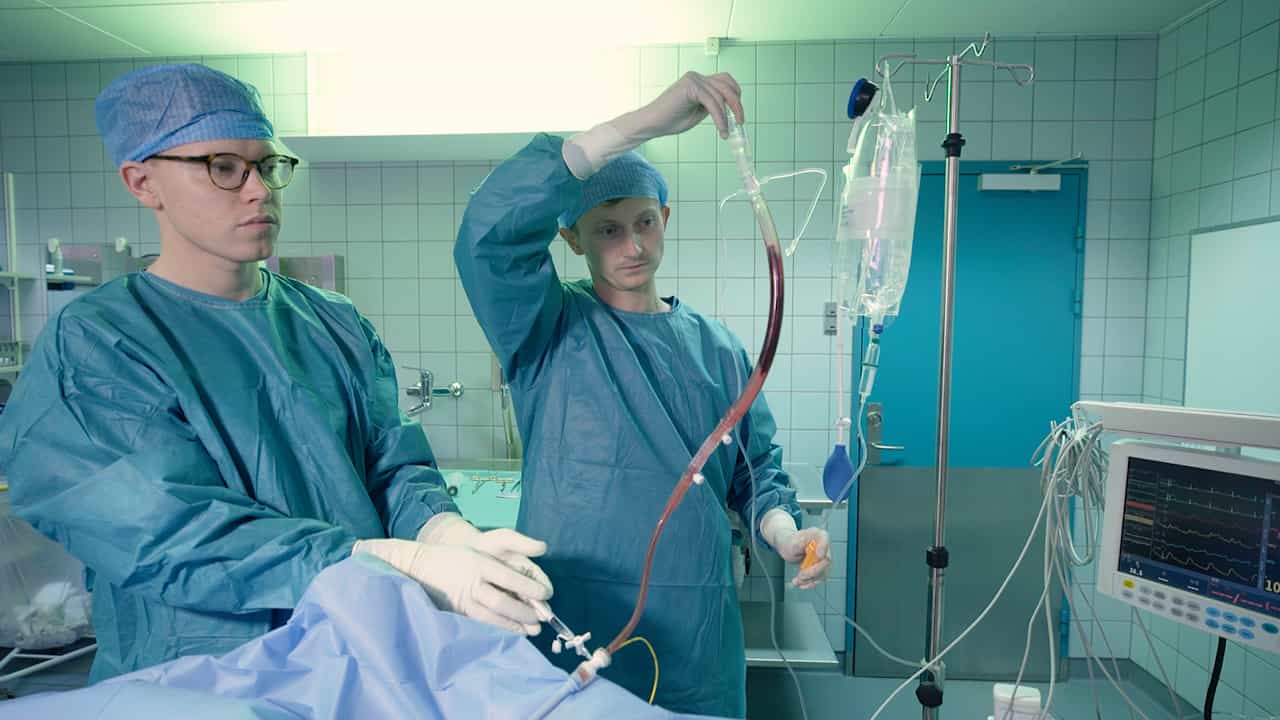

A Porcine Model of Acute Autologous Pulmonary Embolism
Published on: September 6, 2024
D-dimers and efficacy of clinical risk estimation algorithms: sensitivity in evaluation of acute pulmonary embolism
Rajan T Gupta1, Rajesh K Kakarla, Kevin J Kirshenbaum
1Department of Radiology, Duke University Medical Center, DUMC Box 3808, Durham, NC 27710, USA. rajan.gupta@duke.edu

Objective:
The goal of this study was to test the efficacy of clinical risk algorithms and a quantitative immunoturbidimetric D-dimer assay in the evaluation of patients undergoing pulmonary CT angiography for suspected acute pulmonary embolism.
Subjects And Methods:
From April 1, 2007, to March 31, 2008, emergency department evaluations for clinically suspected pulmonary embolism were performed with the revised Geneva score, a quantitative D-dimer assay, and pulmonary CT angiography.
Results:
Evaluations for pulmonary embolism were performed for 745 consecutively registered patients, 627 of whom were included in the study. The other 118 patients were excluded because a d-dimer assay was not performed. According to the revised Geneva score, 281 patients had low clinical probability of having pulmonary embolism; 330, intermediate probability; and 16, high probability. CT angiography showed that 28 patients had pulmonary embolism (six in the low-probability group, 17 in the intermediate-probability group, and five in the high-probability group). The sensitivity, negative predictive value, and specificity of the D-dimer assay were 100%, 100%, and 25% (low-clinical-probability group); 100%, 100%, and 33% (intermediate-probability group); and 80%, 80%, and 37% (high-probability group).
Conclusion:
The data appear to support the use of a quantitative D-dimer assay as a first-line test in evaluation for pulmonary embolism when the clinical probability of the presence of pulmonary embolism is low or intermediate. The sensitivity and negative predictive value were 100% for these cases. More than 26% of CT angiographic examinations might have been avoided if the D-dimer assay had been used as a first-line test in the care of patients at low or intermediate risk. Because of the small sample size, the D-dimer assay is not recommended as a first-line test in the evaluation of patients at high risk.

Related Concept Videos
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:29
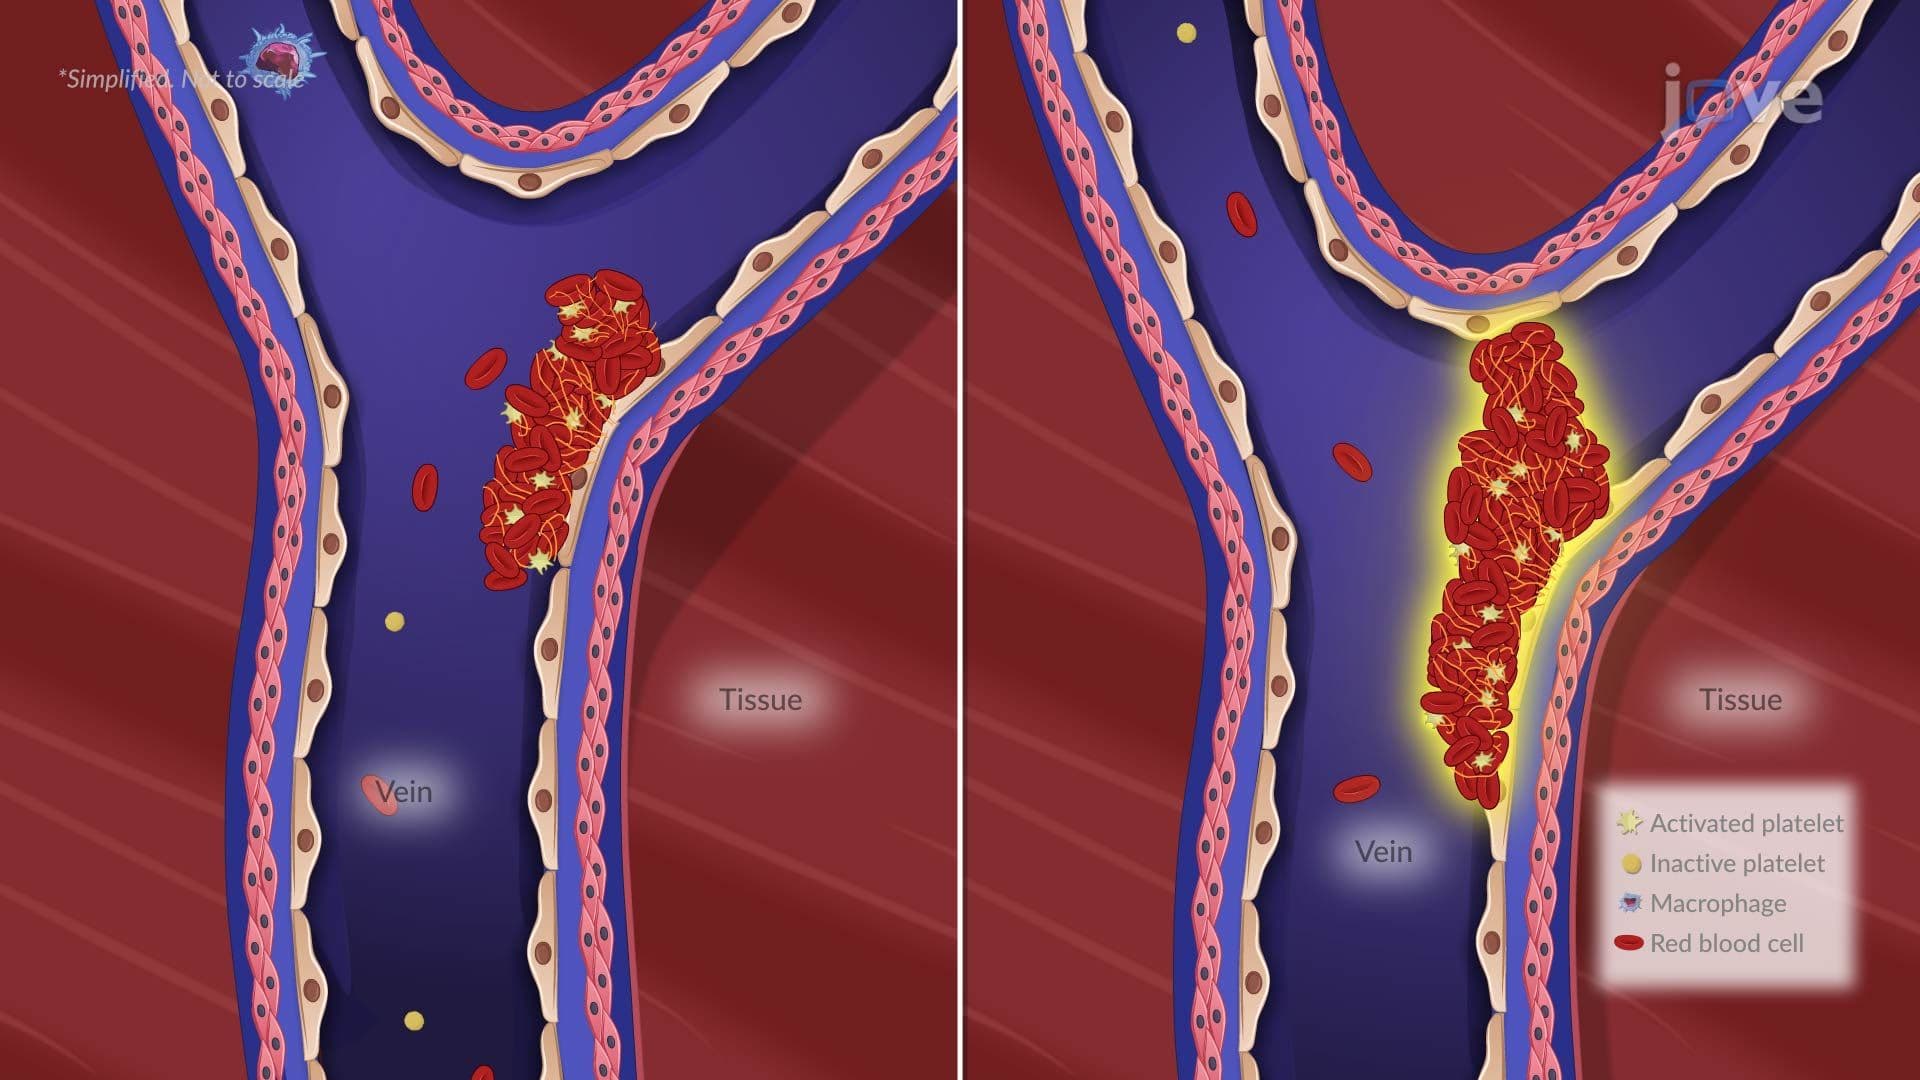
Pulmonary Embolism I: Introduction
 01:19
Pulmonary Embolism I: Introduction
 01:27
Pulmonary Embolism III: Nursing Management
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies