Related Experiment Video
Updated: Jun 21, 2026


Multimodality Diagnosis of Mesenteric Ischemia
Published on: July 21, 2023
Clinical diagnosis of intra-abdominal infections

Abstract:
Abdominal sepsis results in high morbidity and mortality. Intra-abdominal infectious complications are one of the most common infectious pathologies seen in critically ill patients. Approximately 30% of patients admitted to an ICU with intra-abdominal infection succumb to their illness, and when peritonitis arises as a complication of a previous surgical procedure, or recurs during ICU admission, mortality rates exceed 50%. Thus early detection and treatment are essential to minimize patient complications.Critically ill patients are often clinically unevaluable due to distracting injuries, respiratory failure, obtundation, or other pathology. even when patients can be examined, the clinical exam is frequently unreliable and/or misleading. the diagnostic approach to identifying abdominal problems will differ, depending upon the hemodynamic stability of the patient. Patients who have low systolic blood pressures, who are pressor-dependent, may be too unstable to undergo analyses that require trips away from the ICU or emergency department. intra-abdominal pathology may be detected by ultrasound or diagnostic peritoneal lavage. When critically ill patients are stable enough to undergo some diagnostic evaluation of their abdomen, the approach is somewhat simpler. Overall, computerized tomography (CT) is the imaging modality of choice for most intra-abdominal processes. for diagnosis of intra-abdominal conditions using CT scanning it is optimal if patients receive both oral and intravenous contrast. An exception to the use of CT scanning is evaluation of suspected biliary pathology, which is best imaged by ultrasound. it will identify calculous and acalculous cholecystitis and may show changes in the gallbladder or common bile duct associated with biliary obstruction.
Insights
Early detection of intra-abdominal infections in critically ill patients is crucial. Diagnostic approaches vary based on patient stability, with CT scans optimal for most conditions, while ultrasound excels in evaluating biliary pathology.
Area of Science:
- Critical Care Medicine
- Surgical Pathology
- Diagnostic Imaging
Background:
- Intra-abdominal sepsis presents a significant challenge in critical care, leading to high morbidity and mortality rates, especially when complicated by peritonitis.
- Up to 30% of intensive care unit (ICU) patients with intra-abdominal infections die, with mortality exceeding 50% for peritonitis post-surgery or recurrent cases.
- Early detection and prompt treatment are vital for improving outcomes in patients with intra-abdominal infections.
Purpose of the Study:
- To outline diagnostic strategies for intra-abdominal pathology in critically ill patients.
- To emphasize the importance of tailoring diagnostic approaches based on hemodynamic stability.
- To highlight the roles of different imaging modalities in identifying abdominal conditions.
Main Methods:
- Diagnostic approaches are stratified based on patient hemodynamic stability, distinguishing between unstable patients in the ICU and those stable enough for further evaluation.
- For unstable patients, bedside methods like ultrasound or diagnostic peritoneal lavage are considered.
- For stable patients, computed tomography (CT) scanning with oral and intravenous contrast is the preferred imaging modality for most intra-abdominal processes, with ultrasound being optimal for suspected biliary pathology.
Main Results:
- Clinical examination in critically ill patients can be unreliable due to various confounding factors.
- Ultrasound is effective for diagnosing calculous and acalculous cholecystitis and identifying biliary obstruction.
- CT scanning provides comprehensive evaluation of most intra-abdominal conditions when contrast is administered.
Conclusions:
- The diagnostic pathway for intra-abdominal pathology must be individualized, considering patient stability and the specific clinical question.
- CT scanning is the gold standard for evaluating most intra-abdominal conditions in stable critically ill patients.
- Ultrasound remains indispensable for the specific evaluation of gallbladder and biliary tract diseases.
Related Concept Videos
 01:30
Urinary Tract Infection III: Diagnostic Studies and Interprofessional Care
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:19
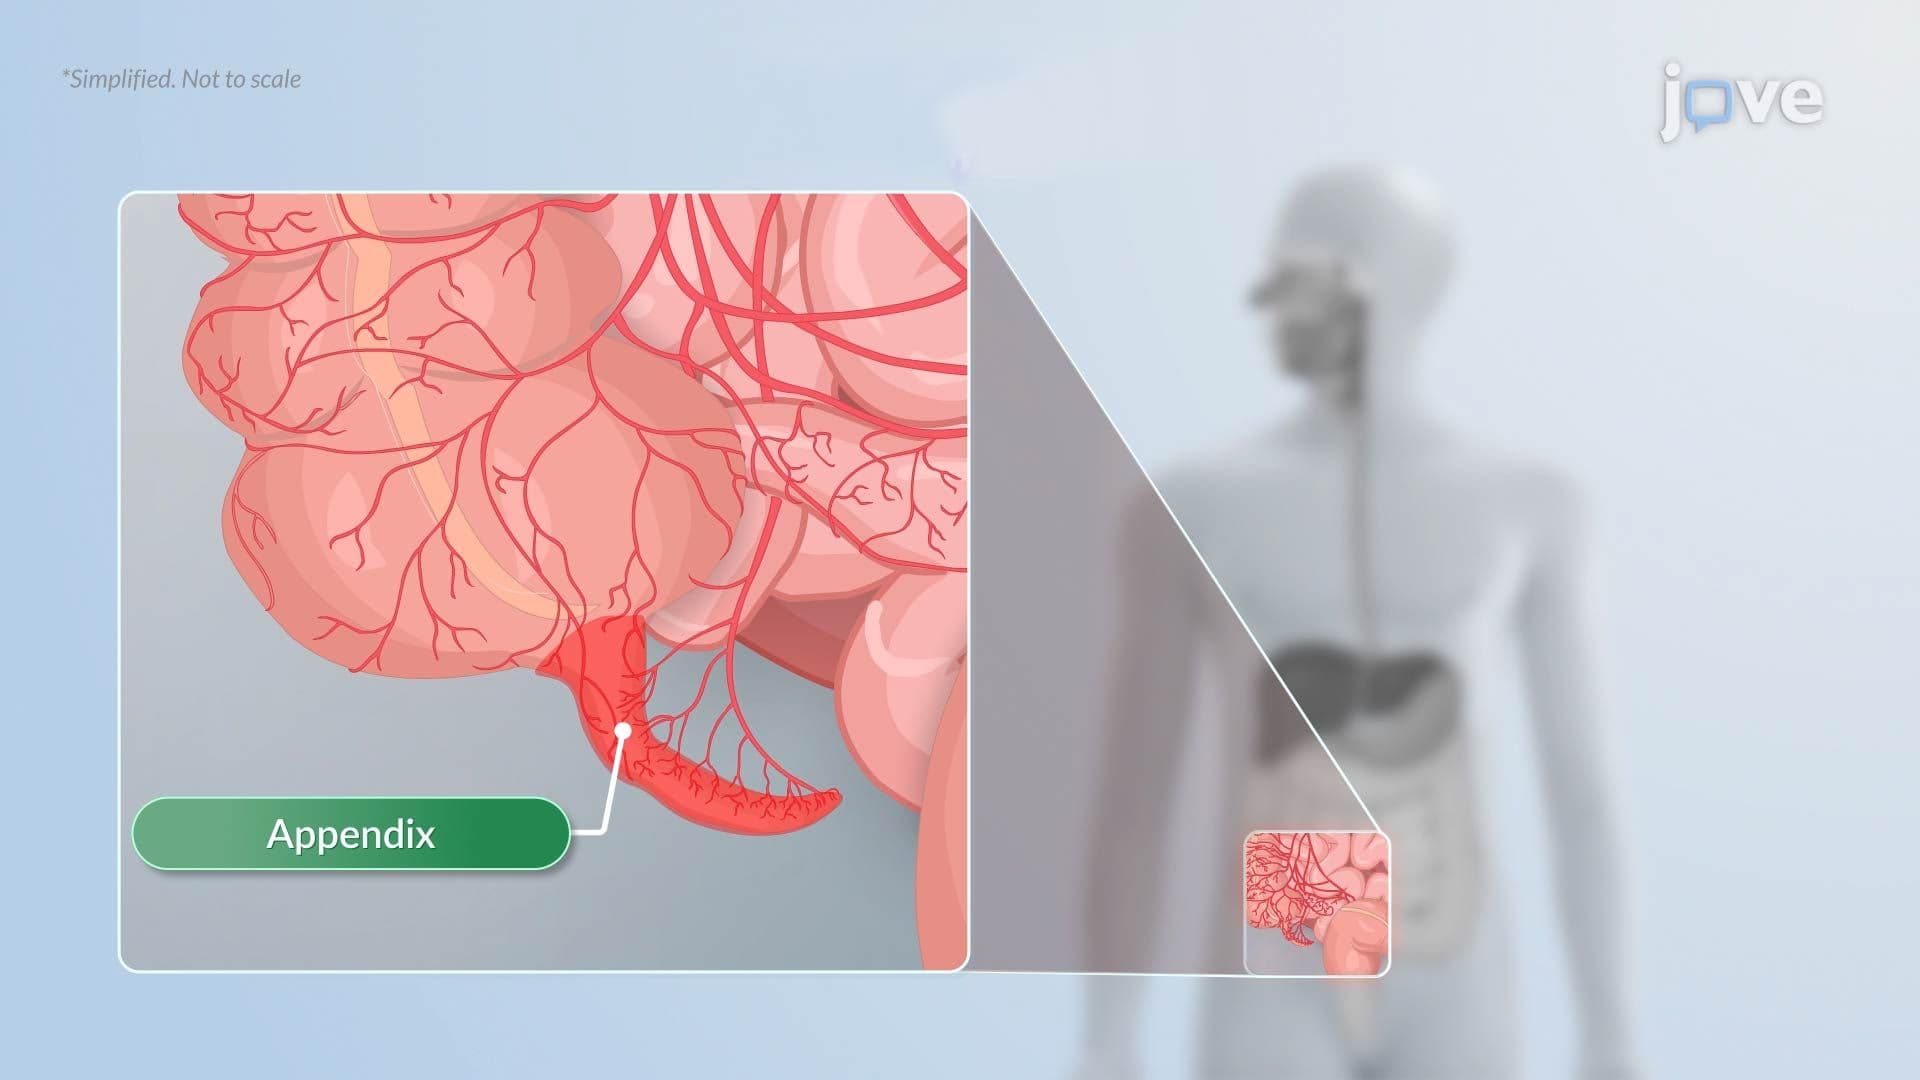
Appendicitis
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.