Related Experiment Video
Updated: Jun 21, 2026


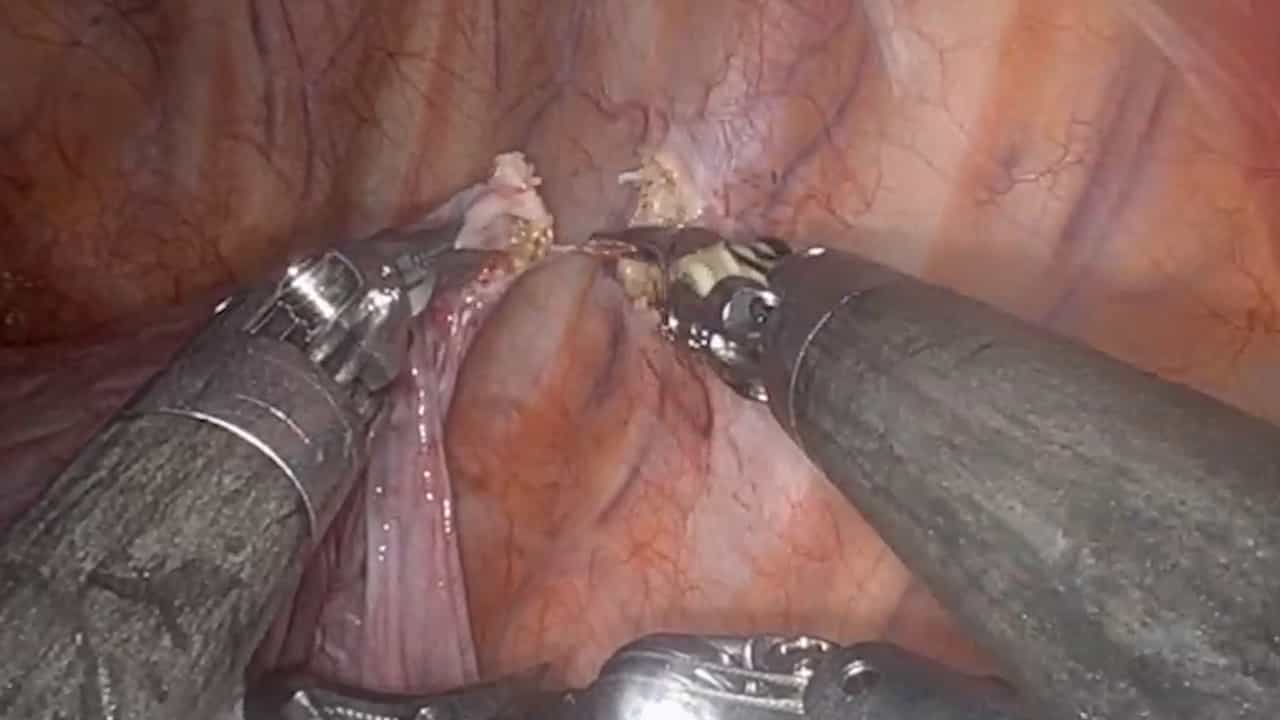
Subcostal Specimen Removal in Completely Portal Robotic Lobectomy
Published on: April 19, 2024
Robot-assisted lobectomy for early-stage lung cancer: report of 100 consecutive cases
Farid Gharagozloo1, Marc Margolis, Barbara Tempesta
1Washington Institute of Thoracic and Cardiovascular Surgery, George Washington University Medical Center, Washington, DC 20037, USA. gharagozloo@aol.com

Background:
Robotics can facilitate dissection during video-assisted thoracoscopic (VATS) lobectomy. This study describes a hybrid minimally invasive lobectomy procedure consisting of two phases: robotic vascular, hilar, and mediastinal dissection, and then VATS lobectomy.
Methods:
Over a 54-month period, 100 consecutive patients with stage I and II (T1 or T2N0, and T1 or T2N1) lung cancer (42 men, 58 women; mean age 65 +/- 8 years) underwent robotic VATS lobectomy.
Results:
Lobectomies were right upper (29), right middle (7), right lower (17), left upper (31), and left lower (16). Mean operating room time was 216 +/- 27 minutes. Tumor type was adenocarcinoma (57), squamous cell carcinoma (25), 7 adenosquamous carcinoma (7), bronchoalveolar (3), large cell (1), poorly differentiated (3), carcinoid (2), mucoepidermoid (1), spindle cell (1). Pathologic upstaging was noted in 17 patients (10 to stage IIB, 7 to stage IIIA). There was no emergent conversion to a thoracotomy. Median hospitalization was 4 days. Complications included atrial fibrillation (13), atelectasis (5), prolonged air leak (4), pleural effusion (3), pulmonary embolus (3), incisional bleeding (1), hydropneumothorax (1), dural leak (1), liver failure (1), pneumonia (1), respiratory failure (1), and cardiopulmonary arrest (1). There was no intraoperative death. Postoperative mortality was 3%. There were no deaths among the last 80 patients. At a median follow-up of 32 months (range, 1 to 59), 1 patient (1%) died of his cancer, 6 (6%) had distant metastases, and 2 (2%) had a second lung primary cancer. There was no local recurrence.
Conclusions:
Robotics are feasible for mediastinal, hilar, and pulmonary vascular dissection during VATS lobectomy.