Related Experiment Video
Updated: Jun 21, 2026

Improved Rodent Model of Myocardial Ischemia and Reperfusion Injury
Published on: March 7, 2022
Adenosine receptors and reperfusion injury of the heart
John P Headrick1, Robert D Lasley
1Heart Foundation Research Centre, School of Medical Science, Griffith University, Southport, Queensland, 4217, Australia. j.headrick@griffith.edu.au

Abstract:
Adenosine, a catabolite of ATP, exerts numerous effects in the heart, including modulation of the cardiac response to stress, such as that which occurs during myocardial ischemia and reperfusion. Over the past 20 years, substantial evidence has accumulated that adenosine, administered either prior to ischemia or during reperfusion, reduces both reversible and irreversible myocardial injury. The latter effect results in a reduction of both necrosis or myocardial infarction (MI) and apoptosis. These effects appear to be mediated via the activation of one or more G-protein-coupled receptors (GPCRs), referred to as A(1), A(2A), A(2B) and A(3) adenosine receptor (AR) subtypes. Experimental studies in different species and models suggest that activation of the A(1) or A(3)ARs prior to ischemia is cardioprotective. Further experimental studies reveal that the administration of A(2A)AR agonists during reperfusion can also reduce MI, and recent reports suggest that A(2B)ARs may also play an important role in modulating myocardial reperfusion injury. Despite convincing experimental evidence for AR-mediated cardioprotection, there have been only a limited number of clinical trials examining the beneficial effects of adenosine or adenosine-based therapeutics in humans, and the results of these studies have been equivocal. This review summarizes our current knowledge of AR-mediated cardioprotection, and the roles of the four known ARs in experimental models of ischemia-reperfusion. The chapter concludes with an examination of the clinical trials to date assessing the safety and efficacy of adenosine as a cardioprotective agent during coronary thrombolysis in humans.
Related Concept Videos
 01:31
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:26
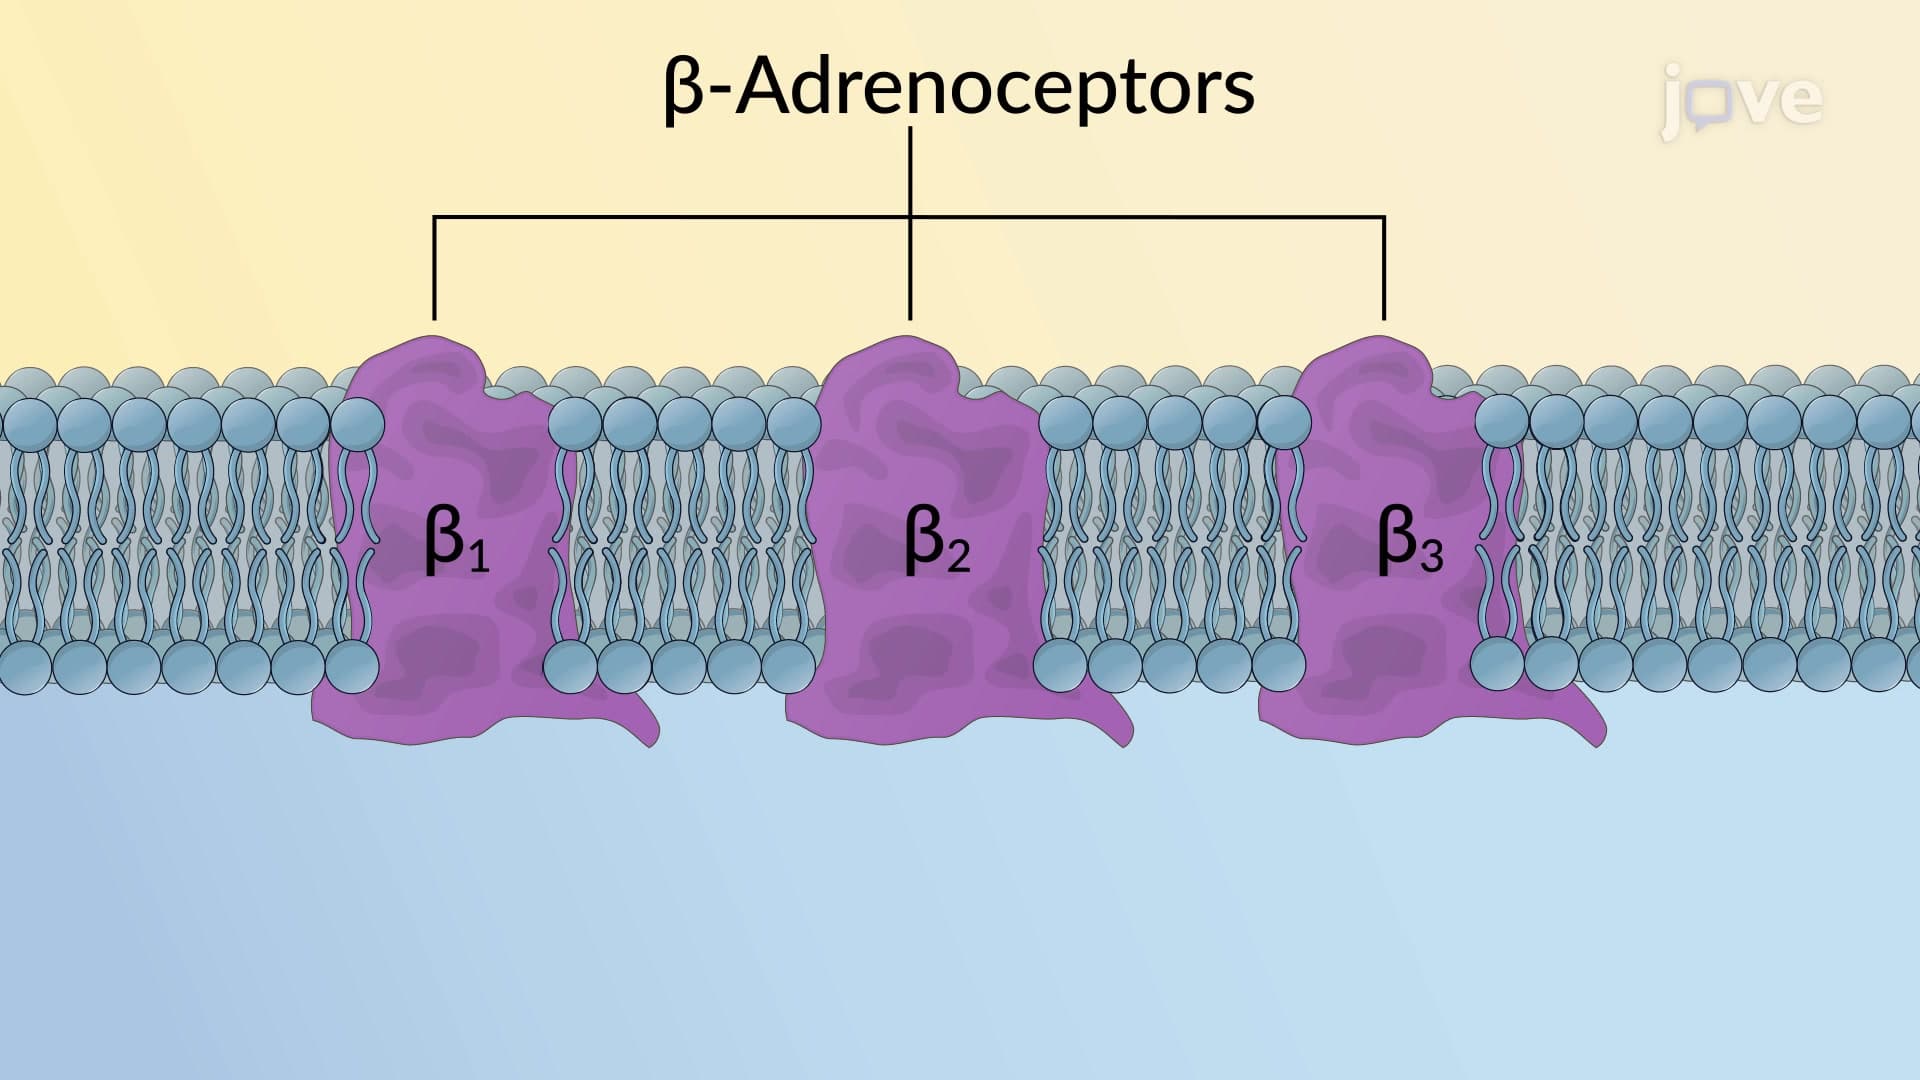
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...
 01:27
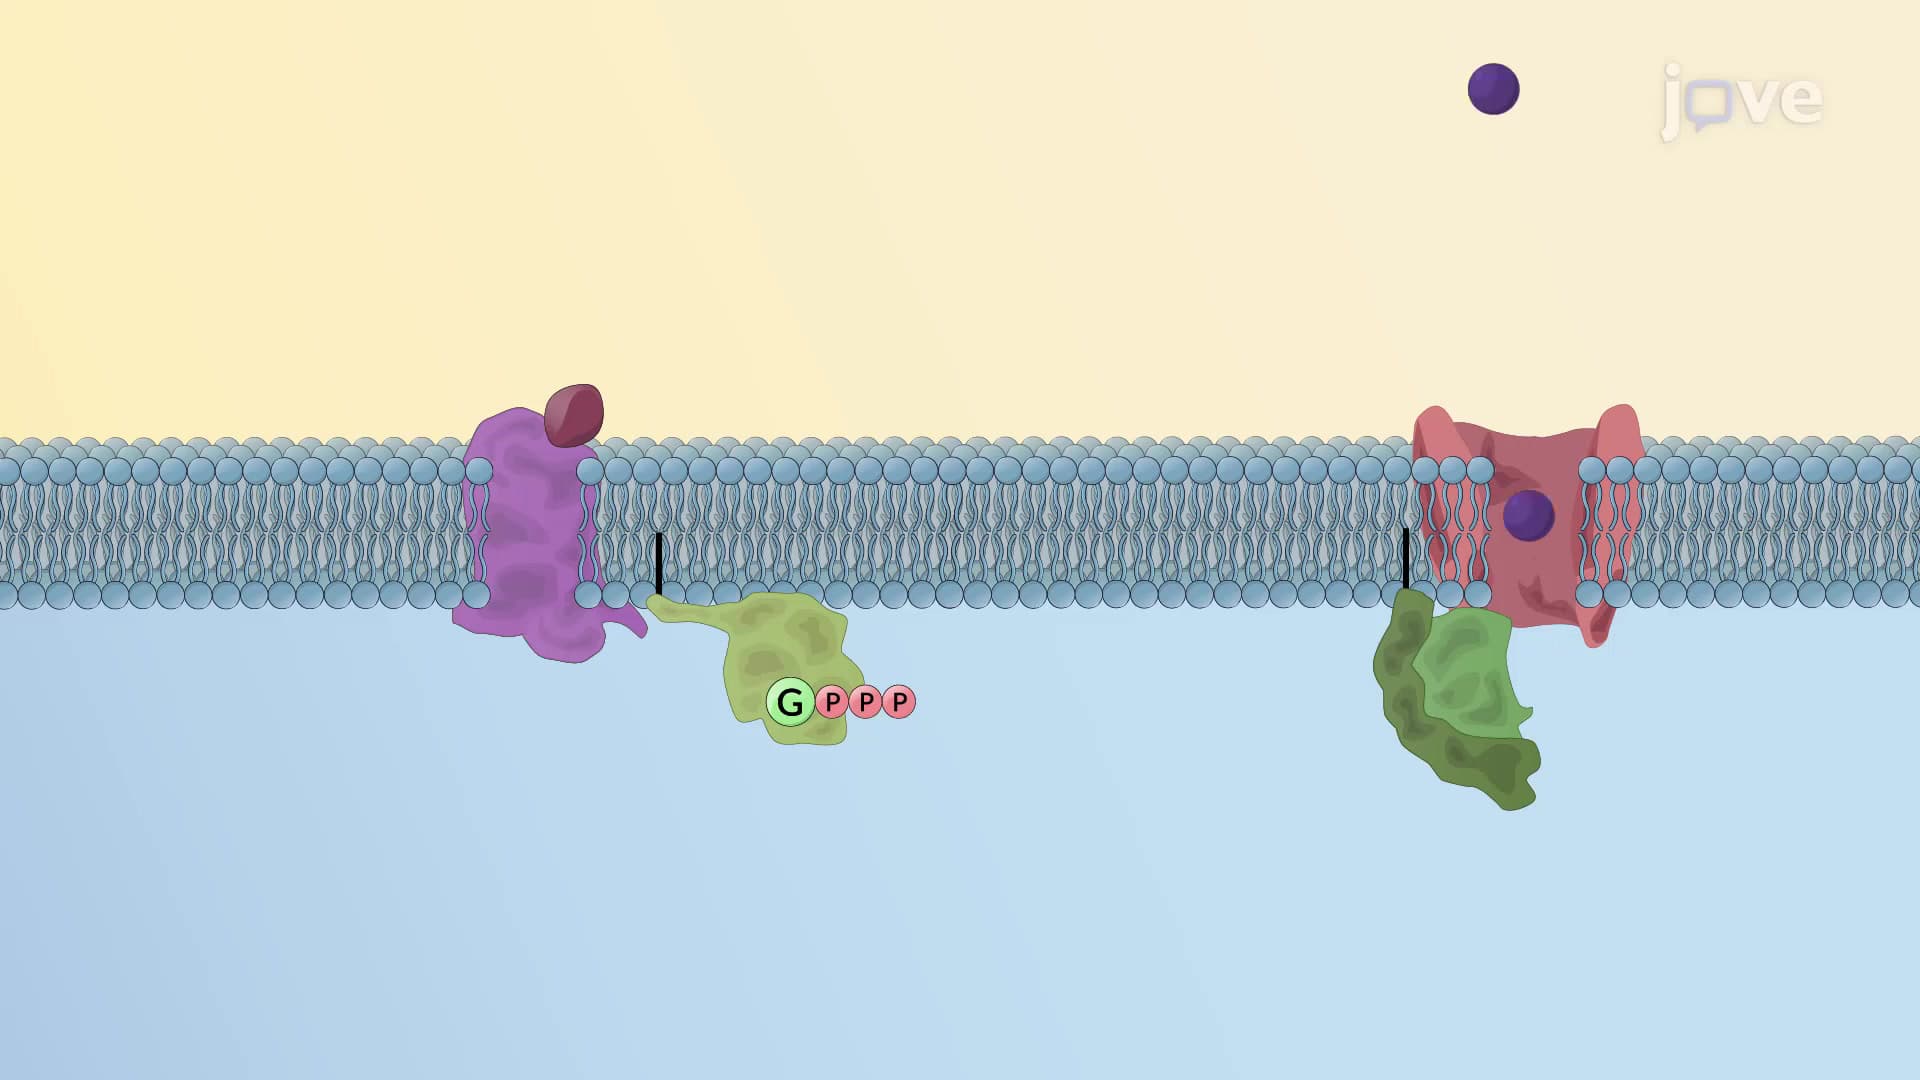
Transducer Mechanism: Enzyme-Linked Receptors
Major types that are helpful drug targets include:
 01:21
G-Protein Gated Ion Channels
Sensory organs,...