Related Experiment Video
Updated: Jun 21, 2026


Anogenital Distance and Perineal Measurements of the Pelvic Organ Prolapse (POP) Quantification System
Published on: September 20, 2018
Complex pelvic floor failure and associated problems
1University College London Hospital, London, UK. sohier.elneil@uclh.nhs.uk

Abstract:
The pelvic floor is a highly complex structure made up of skeletal and striated muscles, support and suspensory ligaments, fascial coverings and an intricate neural network. Its dual role is to provide support for the pelvic viscera (bladder, bowel and uterus) and maintain functional integrity of these organs. In order to maintain good pelvic floor function, this elaborate system must work in a highly integrated manner. When this system if damaged, pelvic floor failure ensues. The aetiology is inevitably multi-factorial, and seldom as a consequence of a single aetiological factor. It can affect one or all the three compartments of the pelvic floor, often resulting in prolapse and functional disturbance of the bladder (urinary incontinence and voiding dysfunction), rectum (faecal incontinence), vagina and/or uterus (sexual dysfunction). This compartmentalisation of the pelvic floor has resulted in the partitioning of patients into urology, colo-rectal surgery or gynaecology, respectively, depending on the patients presenting symptoms. In complete pelvic floor failure, all three compartments are inevitably damaged resulting in apical prolapse, with associated organ dysfunction. It is clear that in this state, the patient needs the clinical input of at least two of the three pelvic floor clinical specialities. Whilst the primary clinical aim is to correct the anatomy, it must also be to preserve or restore pelvic floor function. As a consequence, these patients need careful clinical assessment, appropriate investigations, and counselling before embarking on a well-defined management pathway. The latter includes behavioural and lifestyle changes, conservative treatments (pelvic support pessaries, physiotherapy and biofeedback), pharmacotherapy, minimally invasive surgery (intravaginal slingoplasty, sacrospinous fixation and mid-urethral tapes) and radical specialised surgery (open or laparoscopic sacrocolpopexy). It is not surprising that in this complex group of patients, a multi-disciplinary approach is not only essential, but also critical, if good clinical care and governance is to be ensured.

Related Concept Videos
 01:26
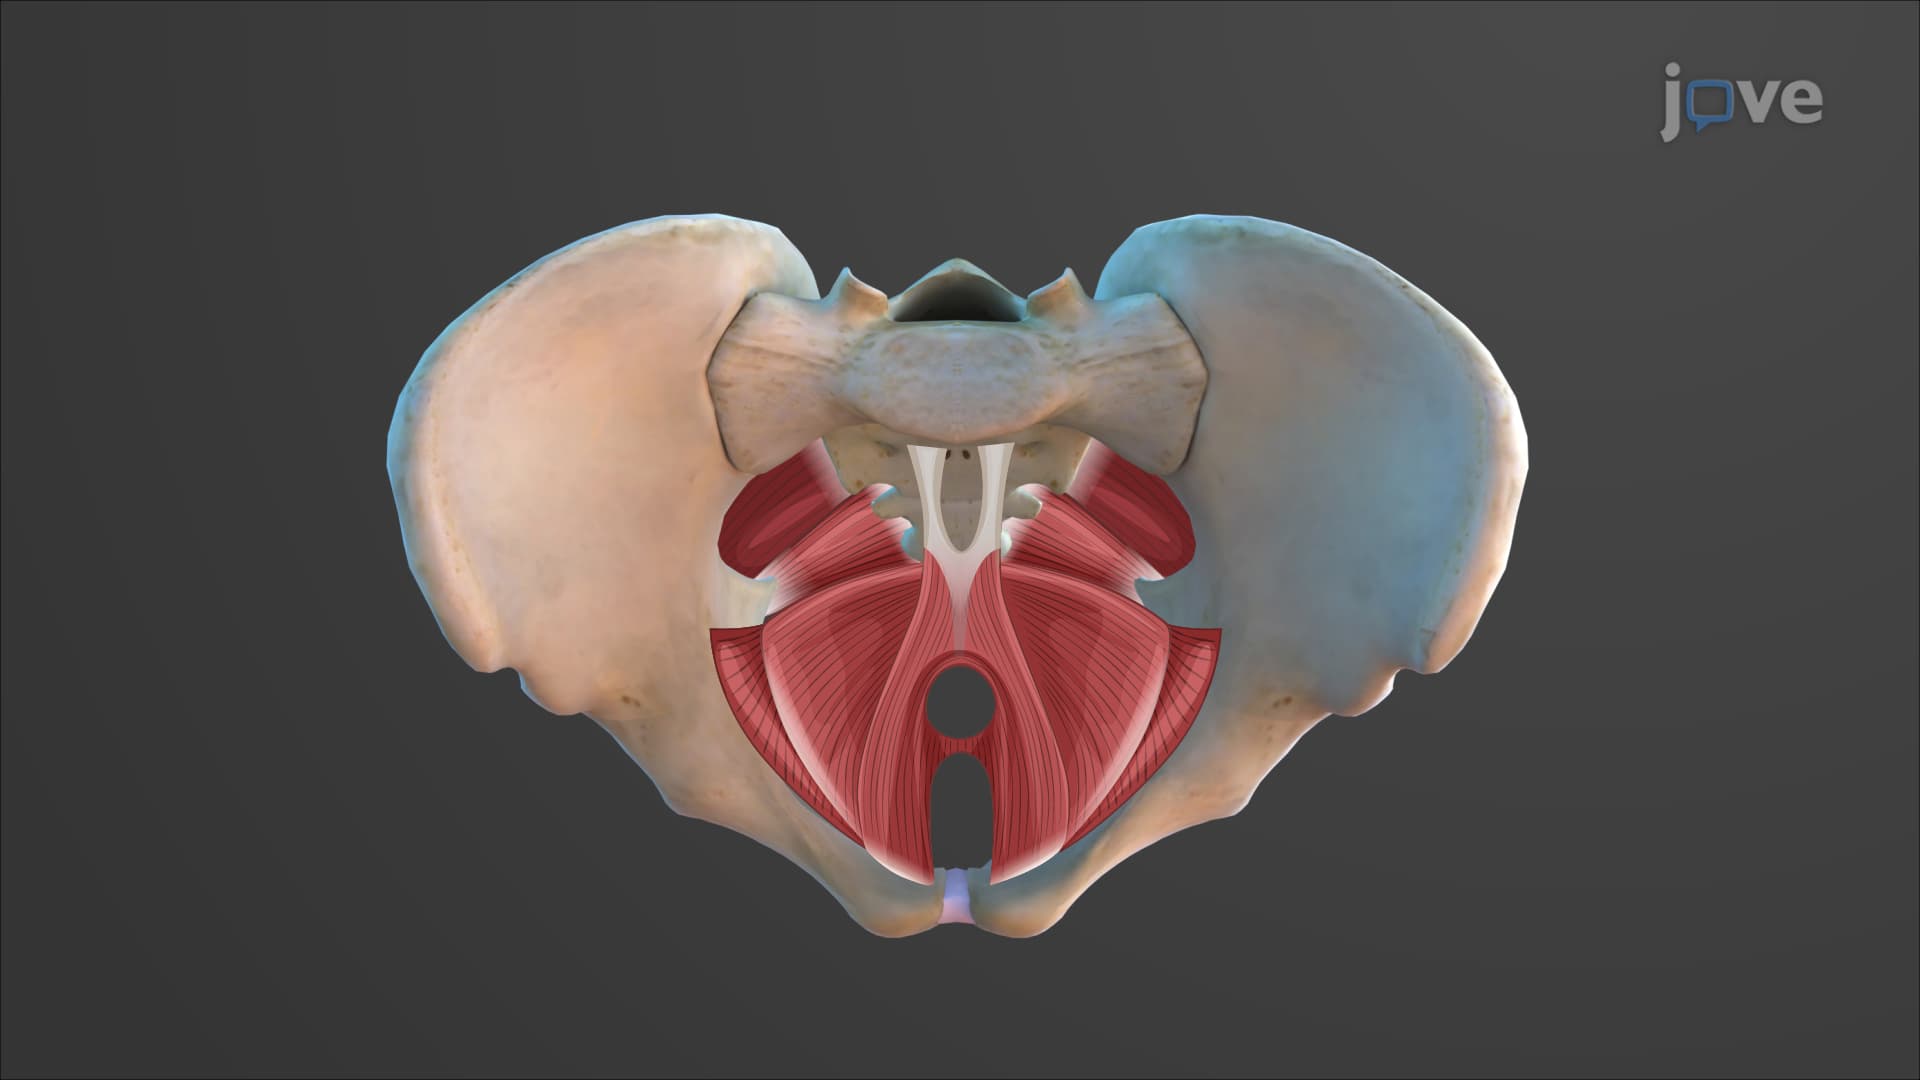
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:20
Disorders of the Urinary System
Urinary tract infections (UTIs) are one of the most common urinary system disorders. They are caused by bacteria that enter the urethra and can spread to the bladder resulting in cystitis. Pyelonephritis is the result of a UTI that has ascended to the level of the...
 01:23
Urinary Bladder
In males, the bladder is situated in front of the rectum, while in females, it is positioned anterior to the vagina and uterus. The bladder floor contains an inverted triangular area called the trigone, defined by the two ureteric...
 01:25
Peritoneal Dialysis II: Peritoneal Dialysis Systems and Complications
 01:19
Anatomy of the Genitourinary System II: Bladder and Urethra
 01:27
Diverticular Disease of the Colon