Related Experiment Video
Updated: Jun 21, 2026


Handheld Metal Detector Screening for Metallic Foreign Body Ingestion in Children
Published on: September 11, 2018
Tracheobronchial foreign bodies in infants
1Department of Neonatal and Paediatric Surgery, St. John's Medical College Hospital, St. John's National Academy of Health Sciences, Johnnagara, Bangalore 560034, India.

Insights
This study highlights that tracheobronchial foreign body aspiration (FBA) in infants often presents with cough, respiratory distress, and stridor. Prompt diagnosis and bronchoscopic intervention lead to favorable outcomes with no mortality.
Area of Science:
- Pediatric Pulmonology
- Otolaryngology
- Emergency Medicine
Background:
- Tracheobronchial foreign body aspiration (FBA) is a frequent cause of respiratory distress in young children.
- Existing literature primarily focuses on toddlers, with limited data on infants.
- This study specifically addresses FBA in infants, a vulnerable population.
Purpose of the Study:
- To review the clinical presentation of FBA in infants.
- To analyze the management strategies employed for infant FBA.
- To evaluate the outcomes of infants treated for tracheobronchial foreign bodies.
Main Methods:
- Retrospective review of 102 infants undergoing bronchoscopy for suspected FBA (1997-2007).
- Analysis of demographic data, clinical features, and diagnostic findings.
- Evaluation of post-bronchoscopy events and patient outcomes.
Main Results:
- The commonest foreign body was a peanut cotyledon.
- The clinical triad of cough, respiratory distress, and stridor was highly predictive.
- Despite challenges like normal initial findings, bronchoscopy ensured successful retrieval with no mortality.
- Average hospital stay was 1.4 days, with all infants asymptomatic at follow-up.
Conclusions:
- A high index of suspicion is crucial for diagnosing FBA in infants.
- Combining history, physical signs, and radiology improves diagnostic accuracy.
- Expertise and endoscopic equipment are vital for favorable outcomes in infant FBA.
Objective:
Tracheobronchial foreign body aspiration (FBA) is a common cause of respiratory distress between 1 and 3 years of age. Literature on airway foreign bodies in this age group is abundant; however no study has addressed this problem in infants exclusively. This study aimed to review the clinical presentation, management and outcome of infants with tracheobronchial foreign bodies at a referral tertiary care hospital over a decade.
Methods:
102 infants who underwent bronchoscopy for suspected FBA from 1997 to 2007 were retrospectively reviewed. Details of demographic data, clinical features, radiologic and bronchoscopic findings, postbronchoscopy events and eventual outcome were analysed.
Results:
The mean age was 10.5 months. 8 (7.8%) were 0-6 months of age, the youngest being 2 months. Males outnumbered (72:30) females. 10 (9.8%) presented secondarily after treatment elsewhere, 6 of them were initially misdiagnosed. The onset-presentation interval ranged from 1 day to 3 months, 41 (40.2%) reporting within a day and 19 (18.6%) a week after onset. 20 (19.6%) had no history suggestive of FBA but harboured airway FBs at bronchoscopy. The clinical triad of cough, respiratory distress and stridor was highly predictive of FBA. 8 (7.84%) had no abnormal physical findings while 8 (10.81%) had grossly normal chest radiographs. All the patients underwent emergency/elective rigid bronchoscopy (Karl Storz system) under general anesthesia as in-patients. The physical findings did not always correlate with radiology or bronchoscopic location of the FB. A peanut cotyledon was the commonest FB retrieved across infancy; in 5 (4.9%) no FB was found/identifiable. 2 required postbronchoscopy mechanical ventilation and 1 a repeat bronchoscopy. There were 6 complications but no mortality in the series. The average hospital stay was 1.4 days. At a week's follow-up, all were asymptomatic and well.
Conclusions:
The clinical presentation, diagnosis and management of FBA in 102 infants are presented and certain peculiar features are described. A high index of suspicion coupled with a combination of history, physical signs and radiology is more conclusive than any of them in isolation. Availability of expertise and endoscopic equipment ensures a favourable outcome without significant morbidity and mortality.

Related Concept Videos
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of the...
 01:23
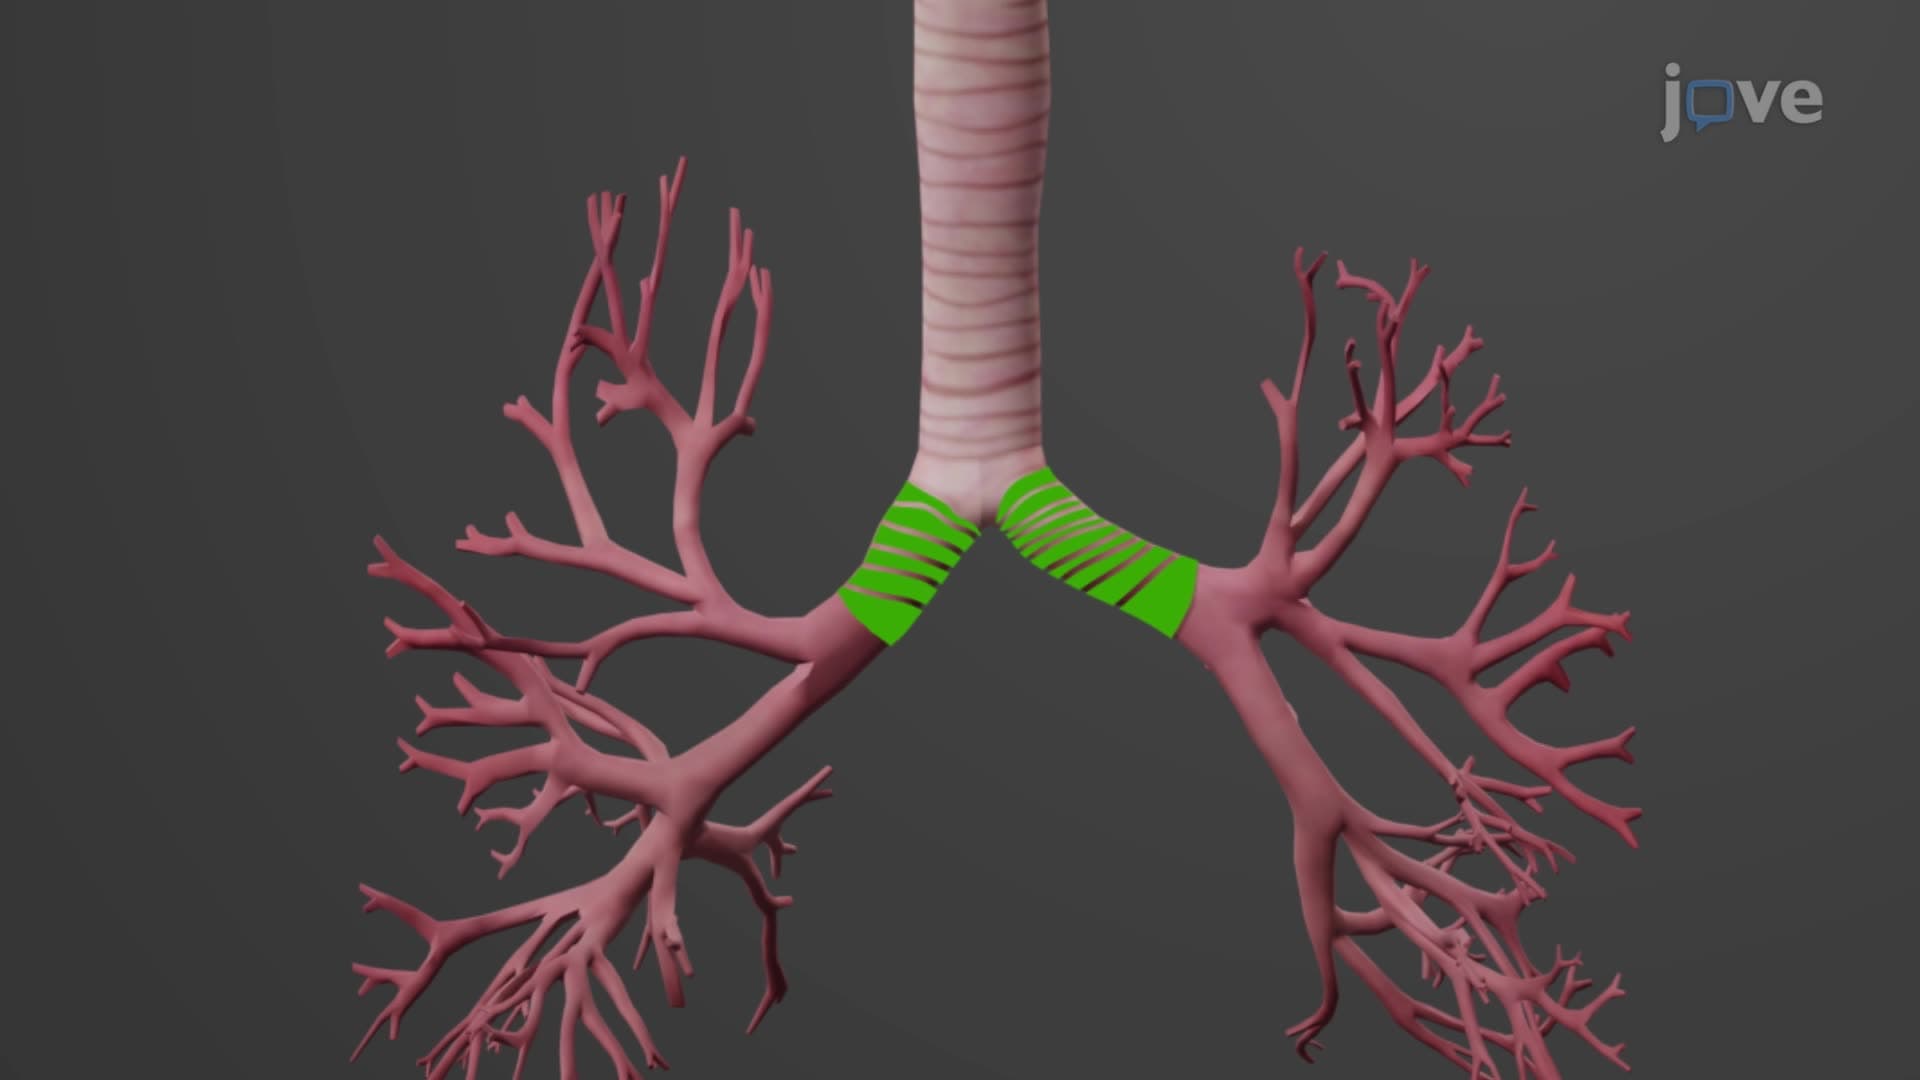
The Bronchial Tree
The trachea, commonly known as the windpipe, is a tube that connects the larynx (voice box) to the bronchi. At a point called the carina, it bifurcates into two primary bronchi. The right primary bronchus is wider, shorter, and more vertical than the left primary...
 01:17
Pulmonary Cycle: Exhalation
 01:29
Microbiota of the Respiratory Tract
 01:31
Anatomy of Respiratory System II: Lower Respiratory Tract
The Larynx
It is located between the pharynx and the trachea, acts as a passageway for air, and hosts several critical structures, such as the epiglottis, vocal cords, and glottis. The epiglottis acts as a gateway, guiding food to the...
 01:05
Breathing