Related Experiment Video
Updated: Jun 21, 2026

Renal Subcapsular Transplantation of 2'-Deoxyguanosine-Treated Murine Embryonic Thymus in Nude Mice
Published on: July 19, 2019
Basiliximab induced non-cardiogenic pulmonary edema in two pediatric renal transplant recipients
Niamh Dolan1, Mary Waldron, Marie O'Connell
1Department of Nephrology, Children's University Hospital, Dublin, Ireland. dolanniamh@eircom.net

Abstract:
We report two cases of non-cardiogenic pulmonary edema as a complication of basiliximab induction therapy in young pediatric renal transplant patients identified following a retrospective review of all pediatric renal transplant cases performed in the National Paediatric Transplant Centre, Childrens University Hospital, Temple Street, Dublin, Ireland. Twenty-eight renal transplantations, of which five were living-related (LRD) and 23 were from deceased donors (DD), were performed in 28 children between 2003 and 2006. In six cases, transplantations were pre-emptive. Immunosuppression was induced pre-operatively using a combination of basiliximab, tacrolimus and methylprednisolone in all patients. Basiliximab induction was initiated 2 h prior to surgery in all cases and, in 26 patients, basiliximab was re-administered on post-operative day 4. Two patients, one LRD and one DD, aged 6 and 11 years, respectively, developed acute non-cardiogenic pulmonary edema within 36 h of surgery. Renal dysplasia was identified as the primary etiological factor for renal failure in both cases. Both children required assisted ventilation for between 4 and 6 days. While both grafts had primary function, the DD transplant patient subsequently developed acute tubular necrosis and was eventually lost within 3 weeks due to thrombotic microangiopathy and severe acute antibody-mediated rejection despite adequate immunosuppression. Non-cardiogenic pulmonary edema is a potentially devastating post-operative complication of basiliximab induction therapy in young pediatric patients following renal transplantation. Early recognition and appropriate supportive therapy is vital for patient and, where possible, graft survival.
Related Concept Videos
 01:26
Kidney Transplant II: Surgical Procedure
 01:28
Kidney Transplant I: Introduction
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:18
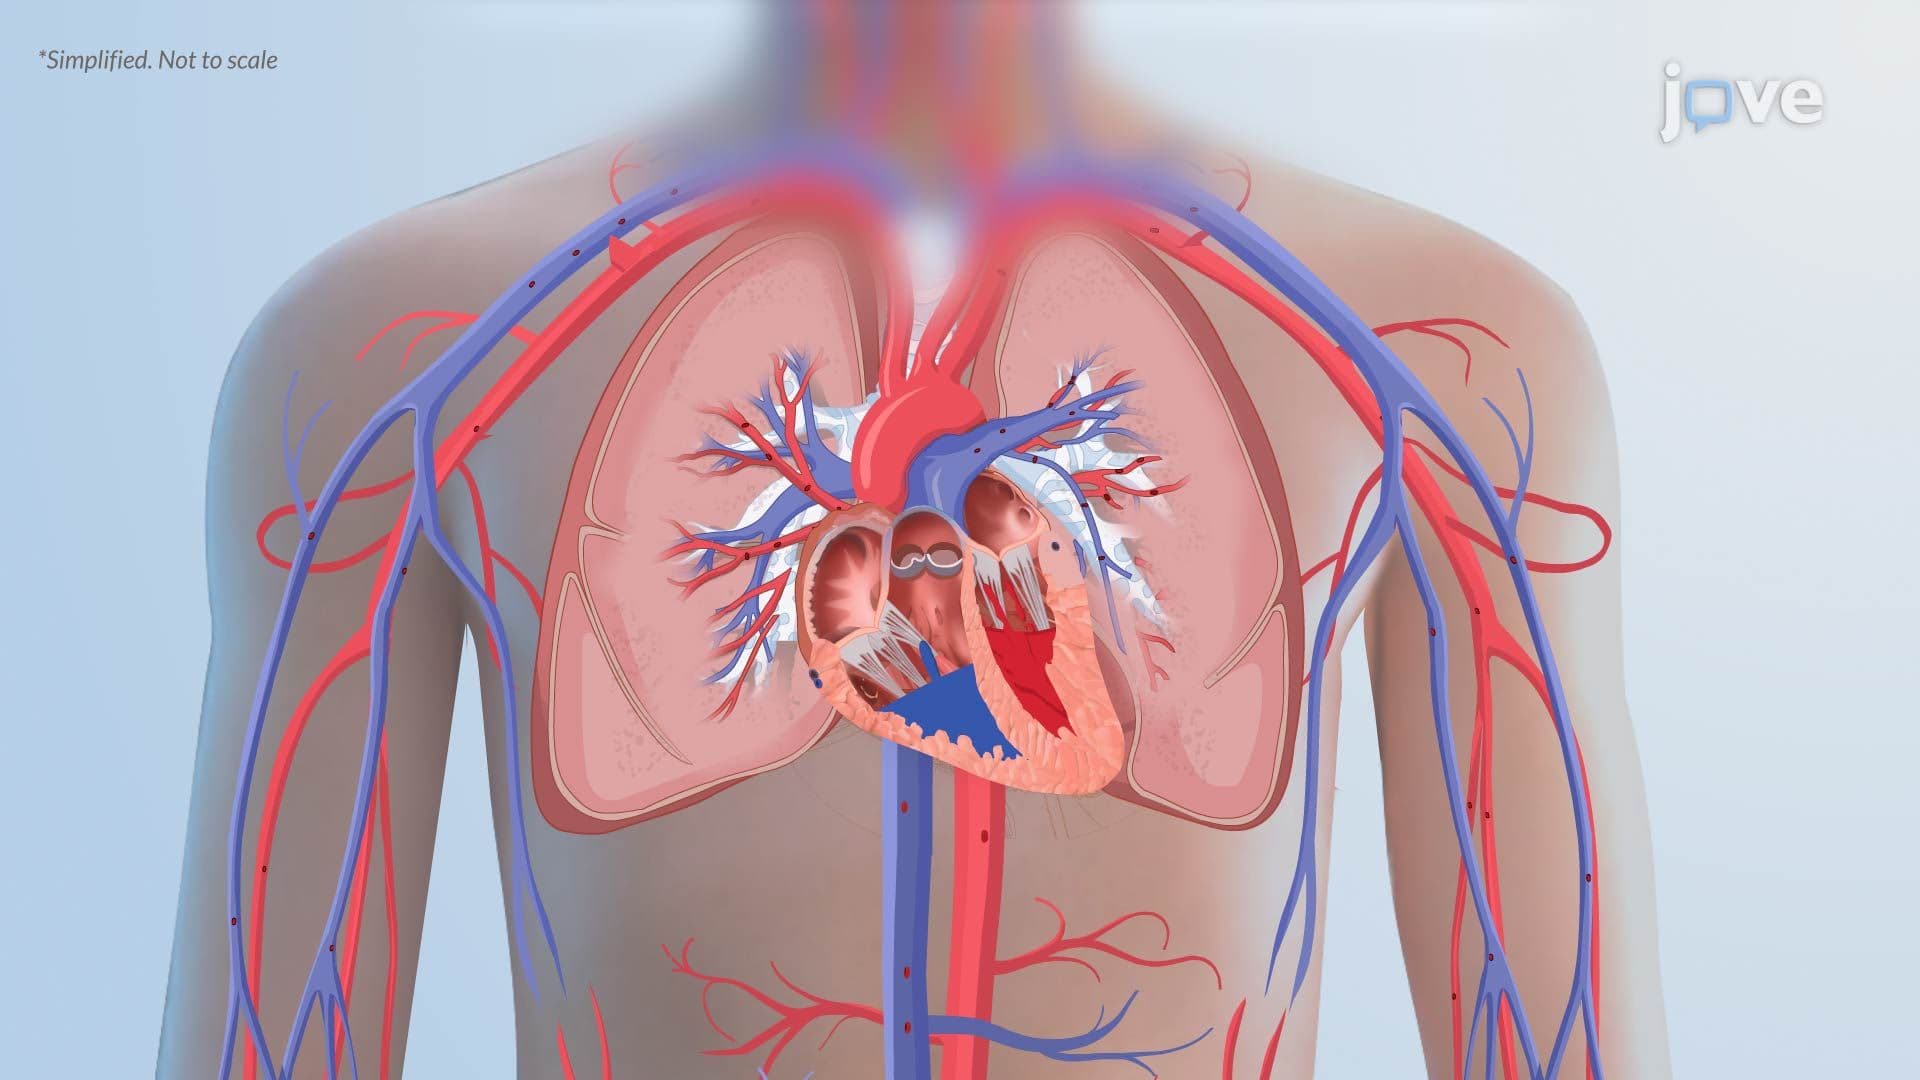
Pulmonary Edema II: Pathophysiology
 01:16
Kidney Transplant III: Nursing Management
 01:15
Impact of Pharmacokinetic–Pharmacodynamic Models: Regulatory Decisions