Related Experiment Video
Updated: Jun 21, 2026
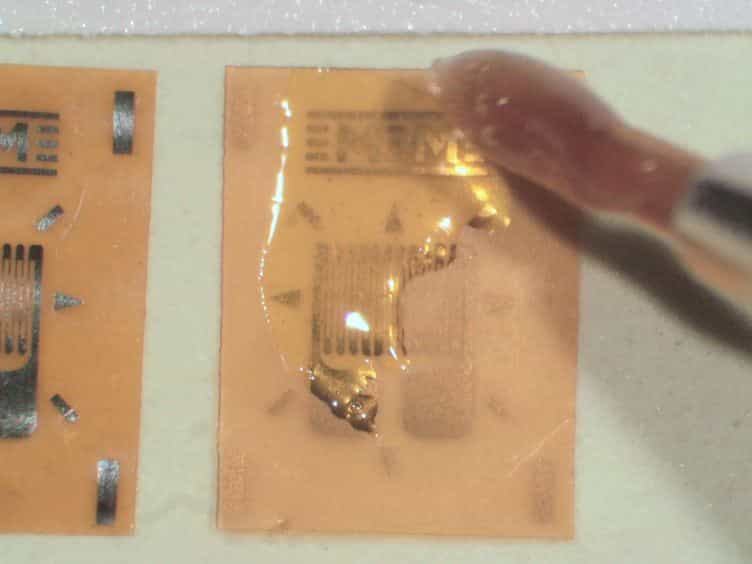

Fabrication and Implantation of Miniature Dual-element Strain Gages for Measuring In Vivo Gastrointestinal Contractions in Rodents.
Published on: September 18, 2014
Differential effect of PYY1-36 and PYY3-36 on gastric emptying in man
A-B Witte1, P Grybäck, J J Holst
1Department of Medicine, Unit of Gastroenterology and Hepatology, Karolinska University Hospital Solna, Karolinska Institutet, 171 76 Stockholm, Sweden.

Abstract:
Peptide tyrosine-tyrosine (PYY) is a prandially controlled hormone in endocrine ileal and colonic mucosa cells. In plasma, PYY appears as full-length PYY1-36 and truncated PYY3-36. Both have different pharmacological profile, and PYY3-36 seems to inhibit food intake. We aimed at investigating the effect of intravenously administered PYY1-36 and PYY3-36 on gastric emptying and short-term metabolic control. Eight healthy adults were studied in single-blinded, randomized design. At separate occasions, intravenous infusion of saline, PYY1-36 or PYY3-36 (0.8 pmol kg(-1) min(-1)) and a radio-labelled omelette were given. Gastric emptying (scintigraphy), appetite ratings (VAS), and plasma concentrations of insulin, glucose, GLP-1 and PYY were measured. PYY3-36 and PYY1-36 both inhibited gastric emptying, PYY3-36 most effectively. Half-emptying time was prolonged from 63.1+/-5.2 (saline) to 87.0+/-11.5 min (PYY3-36), whereas retention at 120 min was 2.5+/-1.4% for saline, 10.7+/-4.4 for PYY1-36 and 15.8+/-4.4 for PYY3-36. Neither form influenced glucose or GLP-1 concentrations, but both decreased the postprandial rise in insulin. PYY3-36 induced nausea (VAS increase 47.5+/-22.6 mm) and decreased prospective consumption (VAS change 39.5+/-7.7 mm). In conclusion, PYY3-36's reducing effect upon food intake might be mediated by a decreased gastric emptying rate.


Related Concept Videos
 01:16
Gastric Emptying
 01:11
Pyloric Obstruction
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:24
Peptic Ulcer Disease II: Pathophysiology
 01:22
Pathophysiology of Peptic Ulcer Disease: Injurious Factors
In the antrum region, G cells secrete the gastrin hormone that binds to gastrin-cholecystokinin-B (CCK2) receptors on parietal and enterochromaffin-like (ECL) cells in the fundic glands. Simultaneously, the vagus nerve releases acetylcholine, which binds to M3...
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...