Related Experiment Video
Updated: Jun 21, 2026
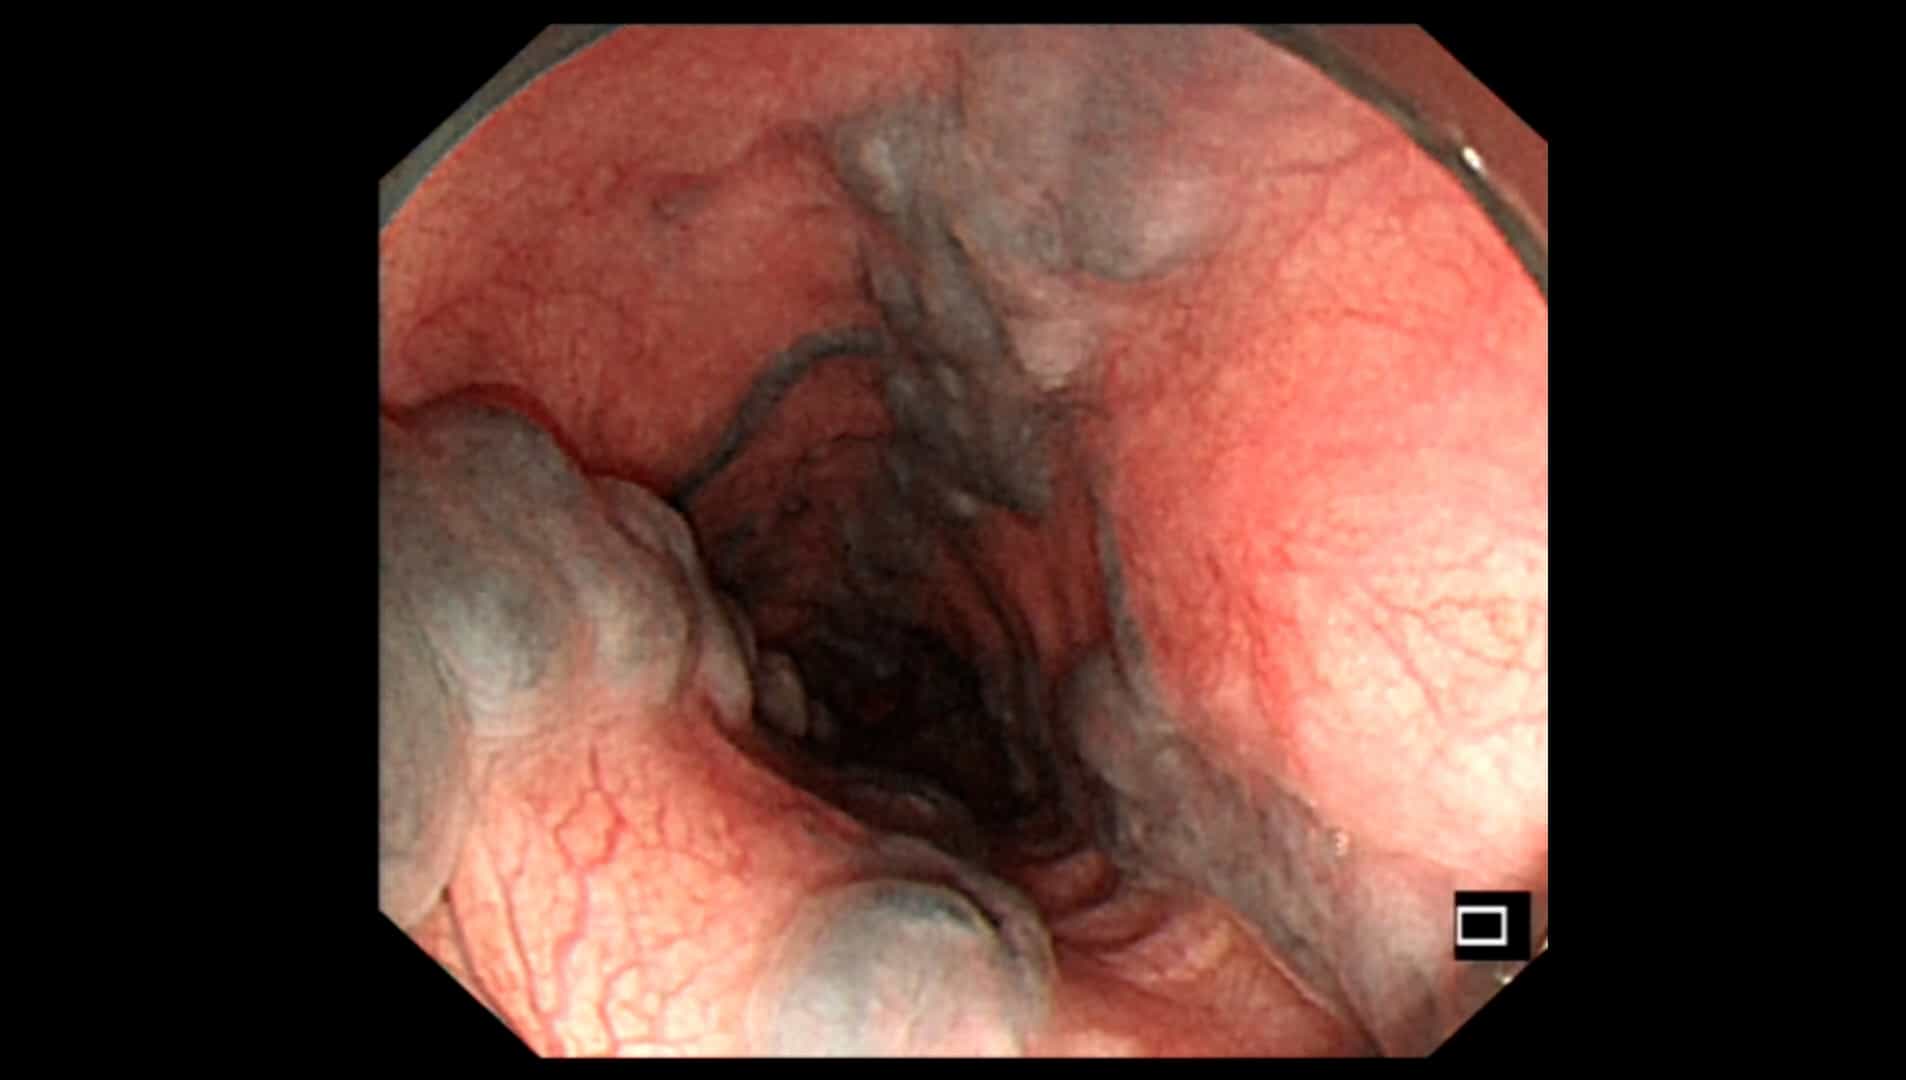
Underwater Endoscopic Injection Sclerotherapy for Gastroesophageal Varices
Published on: August 1, 2025
[Rupture of ileal varices in a type C liver cirrhosis patient: a case report]
Takahisa Suzuki1, Mutsumi Murayama, Masataka Shinoda
1Department of Gastroenterogy, Toyota Memorial Hospital, Japan. takahisa@mail.toyota.co.jp

Insights
Bleeding from small intestinal varices is rare but should be considered in liver cirrhosis patients with unexplained melena. This case highlights ileal varices as a potential source of massive lower gastrointestinal bleeding.
Area of Science:
- Gastroenterology
- Vascular Surgery
Background:
- Liver cirrhosis frequently leads to gastrointestinal bleeding, typically from esophageal varices.
- Non-variceal sources of bleeding in cirrhosis patients can be challenging to diagnose.
Observation:
- A 74-year-old woman with liver cirrhosis presented with recurrent massive lower gastrointestinal bleeding.
- Imaging revealed ileal varices (small intestinal varices) and associated collateral veins.
Findings:
- Ileal varices were surgically resected, with exposed vessels on the mucosal surface identified as the bleeding source.
- This case demonstrates small intestinal varices as a cause of significant gastrointestinal hemorrhage.
Implications:
- Small intestinal varices should be included in the differential diagnosis for obscure gastrointestinal bleeding in patients with liver cirrhosis.
- Advanced imaging and surgical intervention may be necessary for diagnosis and management.
Abstract:
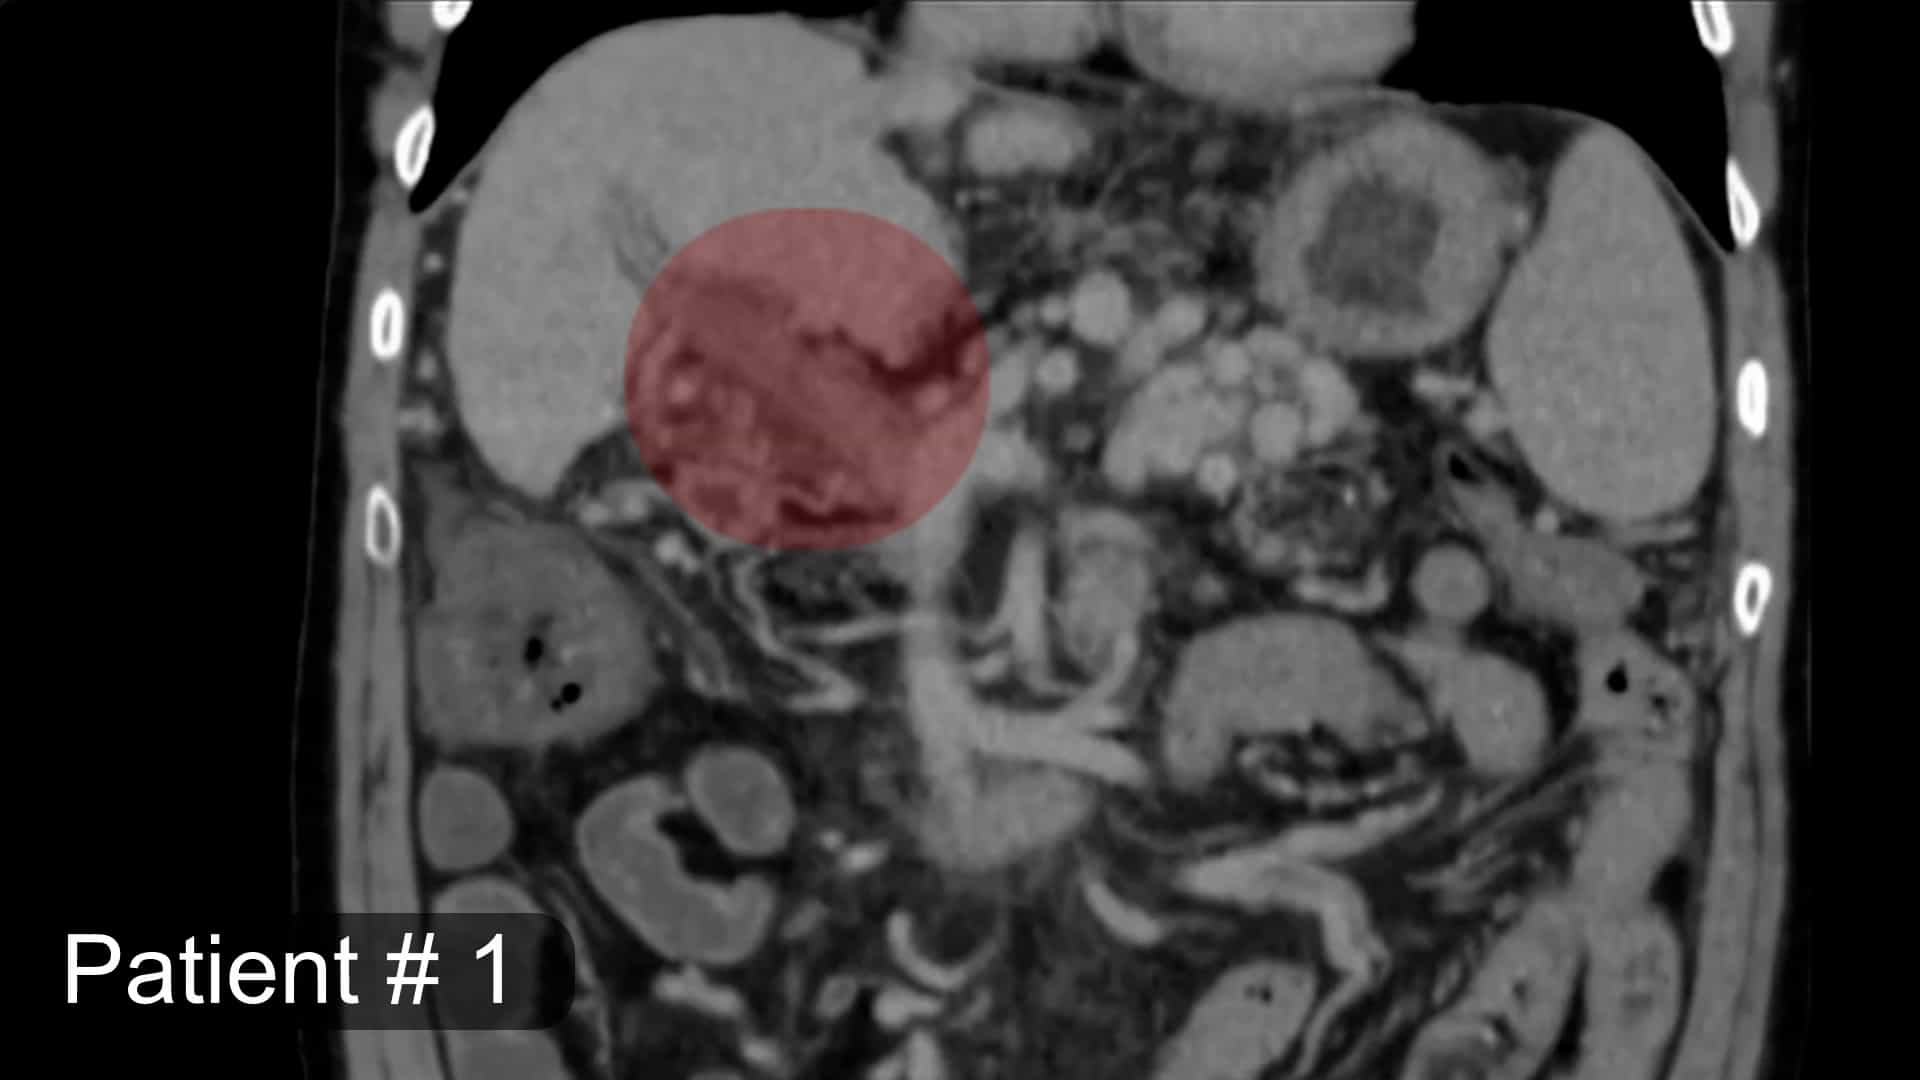
A 74-year-old woman was admitted to our hospital with recurrent massive lower gastrointestinal bleeding. She had a history of type C liver cirrhosis and appendectomy, and had undergone endoscopic ligation of esophageal varices one year before. Three-dimensional CTA revealed ileal varices in the right lower quadrant of the abdomen. Superior mesenteric arteriography demonstrated varices at the corresponding area and collateral veins from the superior mesenteric vein to the right ovarian vein. Ileal varices were diagnosed and ileal resection was performed. At surgery, exposed vessels were present at the mucosal surface of the resected specimen and they were thought to be the origin of hemorrhage. In conclusion, bleeding from small intestinal varices, though uncommon, should be considered when the origin of melena is unidentified in a patient with liver cirrhosis.
Related Concept Videos
 01:24
Esophageal Varices-I: Introduction
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:22
Portal Hypertension
 01:23
Cirrhosis I: Introduction
 01:24
Cirrhosis II: Pathophysiology