Related Experiment Video
Updated: Jun 21, 2026
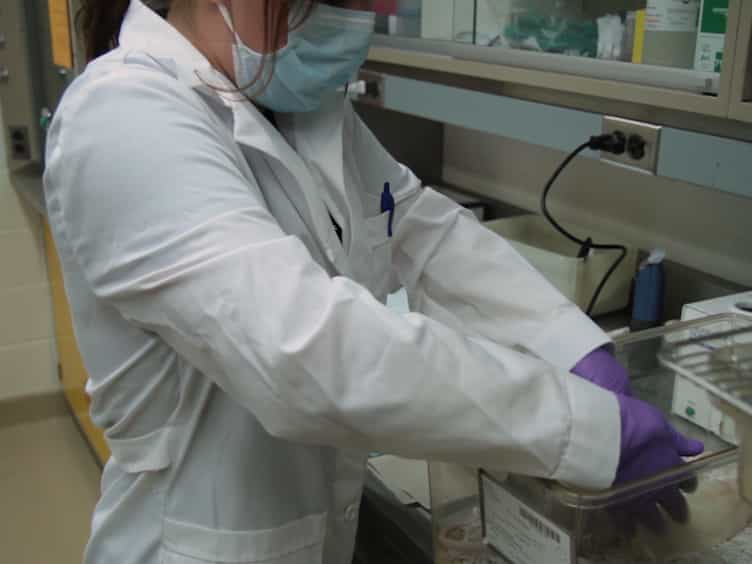

Use of a Rat Model to Study Ventral Abdominal Hernia Repair
Published on: October 2, 2017
Infections associated with prosthetic repairs of abdominal wall hernias: pathology, management and results
M J Tolino1, D E Tripoloni, R Ratto
1Department of Surgery, Sanatorio Franchín, Ciudad Autónoma de Buenos Aires, Buenos Aires, Argentina. marianotolino@yahoo.com.ar

Purpose:
To analyse clinical and demographic factors of patients who suffered infection of the surgical site requiring mesh removal as a complication of prosthetic repairs, details of the hernioplasties in which meshes were implanted and their management and outcomes.
Methods:
Factors related to infection (demographic variables and characteristics of the repairs and mesh utilised) and the management before proceeding to mesh removal were obtained from patient charts. Collected specimens (meshes and tissues) from 32 consecutive patients were cultured and observed microscopically. The outcomes after mesh removal were prospectively evaluated.
Results:
Twenty-two patients underwent incisional hernioplasties and ten inguinal hernioplasties; most of the procedures took a long time, and 28 patients presented early wound complications (seroma or haematoma). During the “implantation–removal” interval, some conservative treatments, such as drainages or sinus resection, were attempted under local anaesthesia. Twenty-two meshes were totally removed (nine after partial extraction); in the remaining ten cases partially removal was successful. Most of the meshes (24) were made of multi-filament polypropylene; microscopic observation of neighbouring tissues showed leucocyte infiltration, giant cell reaction, disorganisation of the collagen fibres and abscedation. Treatment of 32 patients required 51 operations. Following mesh removal, there were six recurrences and two fistulas of the bowel. The average follow-up was 40 months (30–97).
Conclusions:
Most of the infections requiring mesh removal were related to prolonged repair operations that presented untreated early postoperative wound complications. Partial extraction of meshes frequently leads to failures and complications. Surgical exploration should be performed under general anaesthesia to accomplish complete mesh extraction.

Related Concept Videos
 01:25
Peritoneal Dialysis II: Peritoneal Dialysis Systems and Complications
 01:29
Endocarditis IV: Nursing Management
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:18
Endocarditis III: Medical Management
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:26
Healthcare Associated Infections I: Iatrogenic, Exogenic and Endogenic
HAIs significantly increase the cost of health care. Extended stays in healthcare institutions, increased disability, increased costs of medications, including specialized antibiotics, and prolonged recovery times add to the patient's expenses and the healthcare institution and funding bodies. Common...