Related Experiment Video
Updated: Jun 21, 2026


Inducing Acute Liver Injury in Rats via Carbon Tetrachloride (CCl4) Exposure Through an Orogastric Tube
Published on: April 28, 2020
Acute-phase proteins as indicators of bacterial infection in patients with cirrhosis
Aristotelis Tsiakalos1, Aggelos Karatzaferis, Panayiotis Ziakas
1Pathophysiology Department, Laikon General Hospital and Medical School, National and Kapodistrian University of Athens, Athens, Greece. atsiakalos@gmail.com

Background:
Cirrhosis is associated with elevated levels of acute-phase proteins (APP), irrespective of the presence of infection. This condition limits the clinical application of APP determination in cirrhotic patients with bacterial infections.
Aims:
To weigh the diagnostic value of several APP in cirrhotics with or without bacterial infection, and to correlate them with the clinical outcome.
Methods:
We investigated 88 consecutive cirrhotic patients (67 males, 21 females; range 28-85 years) with mean age (SD) 58.9 (13.8) on admission, according to a standard protocol for infection. We measured the following APP: C-reactive protein (CRP), fibrinogen (FIB), haptoglobin (Hpt), ferritin (Fer), beta2-microglobulin (beta2-mg), C3, C4 and C1 inhibitor.
Results:
From the 88 patients, 19 (21.6%) had documented infection at the entry based on clinical, radiological and microbiological data. This group of patients did not differ in basic demographics from those without infection. CRP [17.5 (20.7) vs 77.1 (43.9), P<0.001], beta2-mg [4.4 (4.1) vs 5.6 (2.2), P<0.001] and ferritin [461.2 (776.4) vs 825.8 (870), P=0.03] were significantly higher in infection, whereas C3 was significantly lower. No significant differences were noted in the remaining APP levels between the two groups. After receiver operating characteristic curves were fitted, CRP was the best diagnostic test for infection (area under the curve 0.91), followed by beta2-mg, ferritin, FIB, C1 inhibitor, C4, Hpt and C3.
Conclusions:
Serum CRP is the best test, among the examined APP, to discriminate bacterial infection in cirrhotics. A cut-off value of >55.8 mg/L has high sensitivity (79%) and specificity (96%), with the best diagnostic accuracy (92%).

Related Concept Videos
 01:24
Cirrhosis II: Pathophysiology
 01:23
Cirrhosis I: Introduction
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:25
Acute Pancreatitis I: Introduction
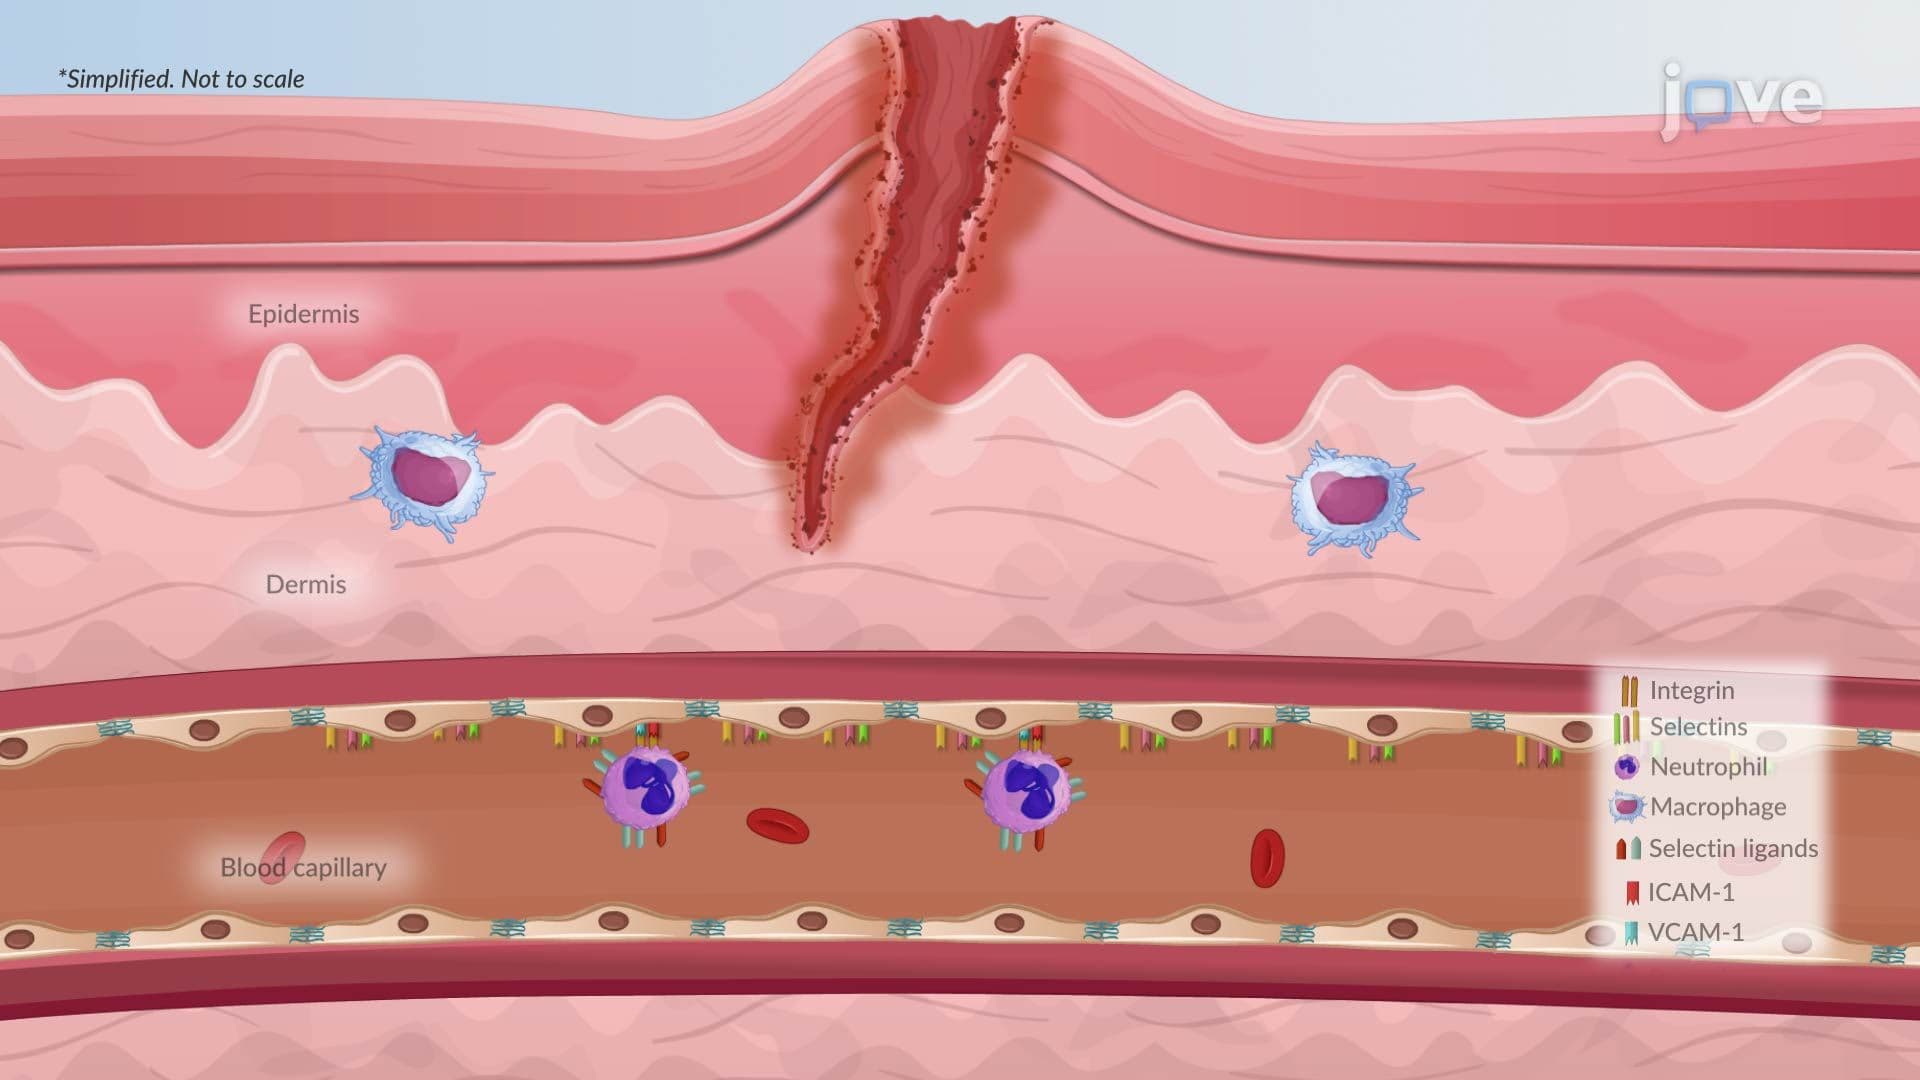 01:26
Acute Inflammation II: Cellular Phase
 01:20
Blood Studies for Cardiovascular System I: Cardiac Biomarkers
The essential diagnostic tools for detecting myocardial necrosis and monitoring individuals suspected of having acute coronary syndrome (ACS) include:
Troponins
Troponins, particularly cardiac troponins I and T, are the most precise and sensitive markers of myocardial injury. They are detectable within 4-6 hours of myocardial injury and remain...