Related Experiment Video
Updated: Jun 21, 2026


The Antihypertensive Effects and Mechanisms of Huotan Jiedu Tongluo Decoction in Rats with H-Type Hypertension
Published on: May 17, 2024
Hypertension and TIA
W W Zhang1, D A Cadilhac, G A Donnan
1National Stroke Research Institute, part of Florey Neuroscience Institutes, Victoria, Australia.

Insights
High blood pressure significantly increases stroke risk after a transient ischemic attack (TIA). Understanding blood pressure
Area of Science:
- Neurology
- Cardiology
- Hypertension Research
Background:
- Transient ischemic attack (TIA) is a critical warning sign for stroke, necessitating immediate medical attention.
- Hypertension is the primary modifiable risk factor for both stroke and TIA.
- Effective management of blood pressure is crucial for preventing secondary strokes after a TIA.
Purpose of the Study:
- To review the current understanding of the relationship between blood pressure and TIA.
- To explore the significance of diurnal blood pressure variations in TIA patients.
- To assess the potential of chronotherapy for optimizing blood pressure control in TIA patients.
Main Methods:
- Literature review synthesizing existing research on hypertension, TIA, and stroke risk.
- Analysis of ambulatory blood pressure monitoring data regarding diurnal patterns.
- Examination of studies on blood pressure control and adherence post-TIA.
Main Results:
- A strong correlation exists between hypertension and TIA incidence, as well as short-term stroke risk.
- Ambulatory blood pressure monitoring reveals diurnal variations that may impact stroke risk.
- Blood pressure control is frequently inadequate in post-TIA patients due to undertreatment and poor adherence.
Conclusions:
- Hypertension is a major risk factor for TIA and subsequent stroke.
- Abnormal diurnal blood pressure patterns may influence stroke risk after TIA, warranting further investigation.
- Chronotherapy presents a potential strategy for improving blood pressure management in TIA patients, though more research is required.
Abstract:
Transient ischemic attack is a medical emergency because early stroke risk after transient ischemic attack is high. Hypertension is the most important modifiable risk factor for stroke and transient ischemic attack. The aims of this review are to provide a summary of the current knowledge concerning the relationship between blood pressure and transient ischemic attack, as well as outline issues regarding diurnal variation and the potential of chronotherapy (timing medications to accord with diurnal patterns of blood pressure). There is a strong relationship between hypertension and the incidence of transient ischemic attack and the subsequent short-term risk for stroke. Ambulatory blood pressure monitoring is a reliable diagnostic and monitoring tool for hypertension and provides additional information about diurnal variation in blood pressure. Different diurnal blood pressure patterns may confer variable stroke risk. Patients with stroke commonly have abnormal diurnal blood pressure patterns and this may relate, in part, to autonomic nervous system dysfunction. However, blood pressure patterns have not been systematically studied in patients with transient ischemic attack. Blood pressure remains poorly controlled in a large proportion of patients after transient ischemic attack and under-treatment and poor adherence are important factors. Chronotherapy for blood pressure may result in more effective blood pressure control. More research is needed in this area. Hypertension is strongly associated with transient ischemic attack. Diurnal blood pressure patterns may influence subsequent stroke risk after transient ischemic attack and more evidence is needed to inform clinical practice to improve blood pressure management for transient ischemic attack patients.
Related Concept Videos
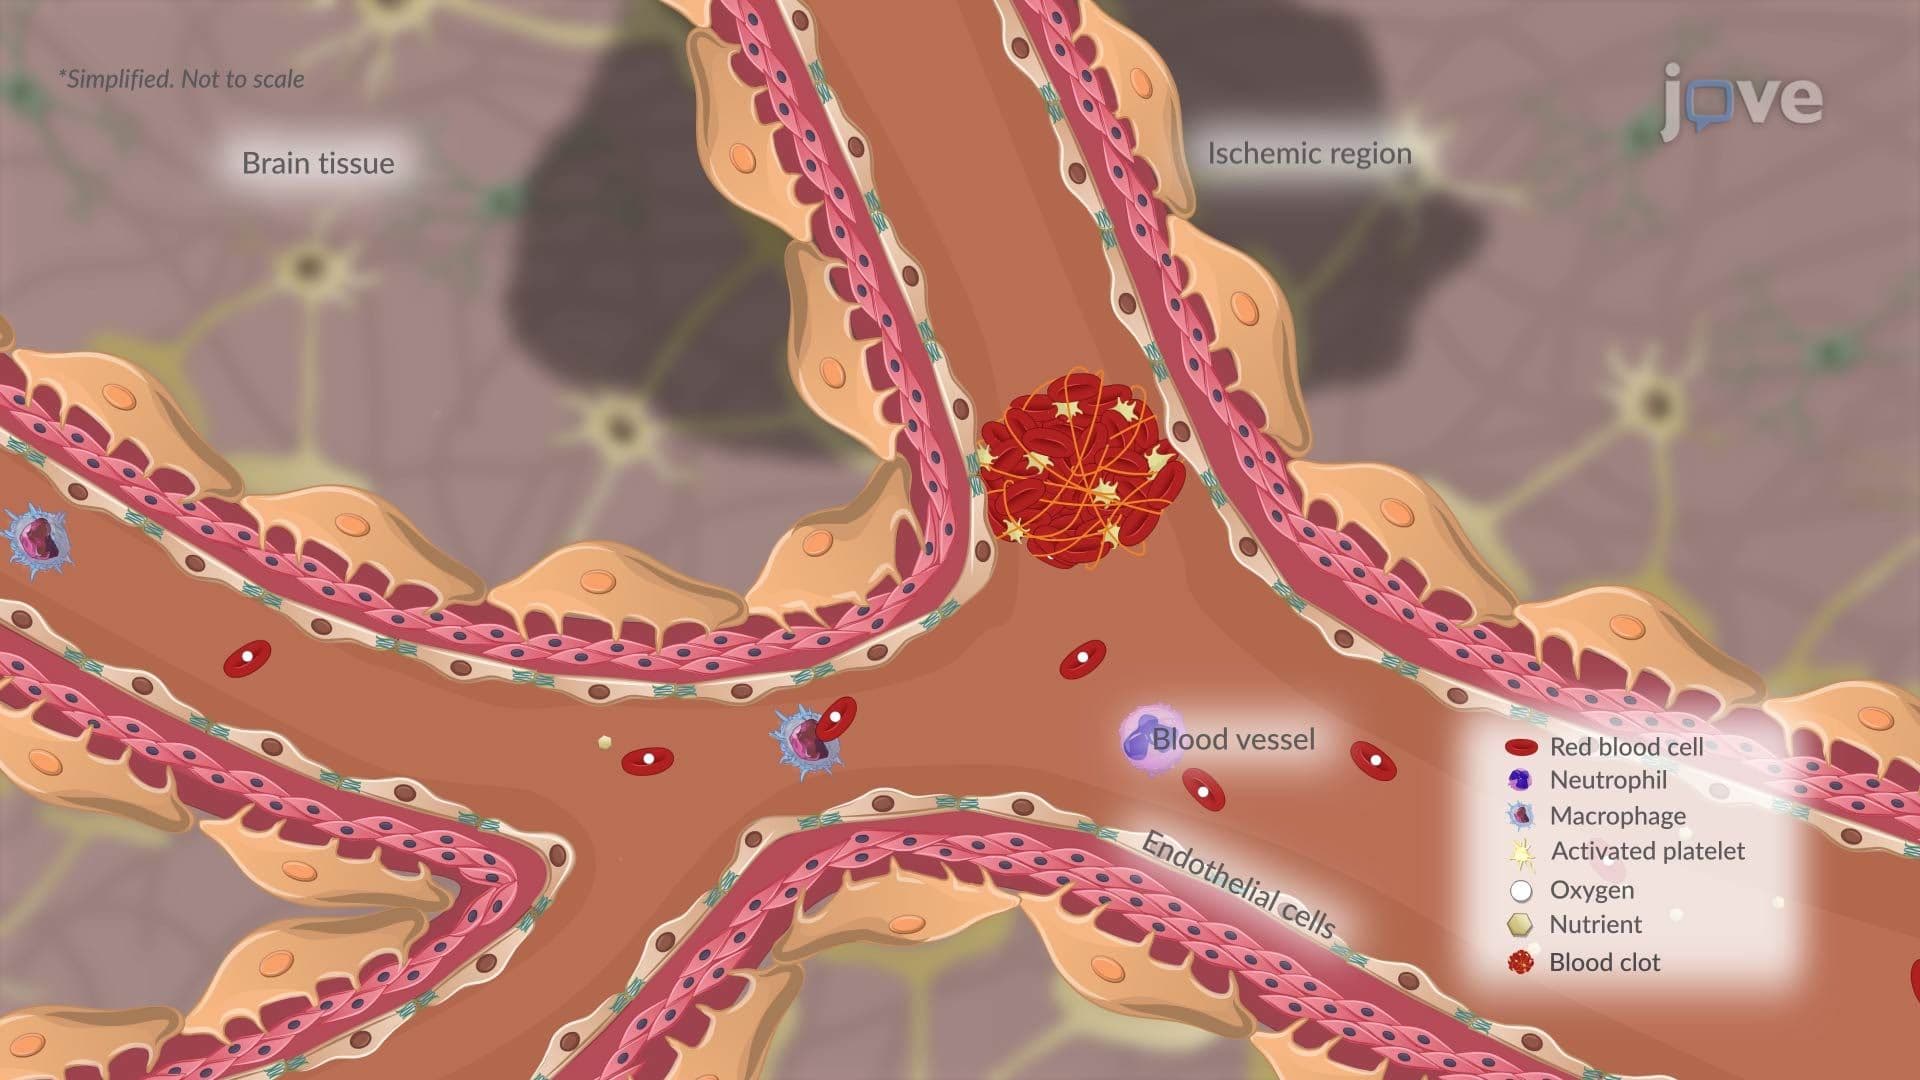 01:26
Transient Ischemic Attack l: Introduction
 01:23
Hypertension V: Nursing Management
 01:28
Hypertension I: Introduction
 01:18
Hypertension and Regulation of Blood Pressure
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:29
Hypertension II: Pathophysiology