Related Experiment Video
Updated: Jun 21, 2026
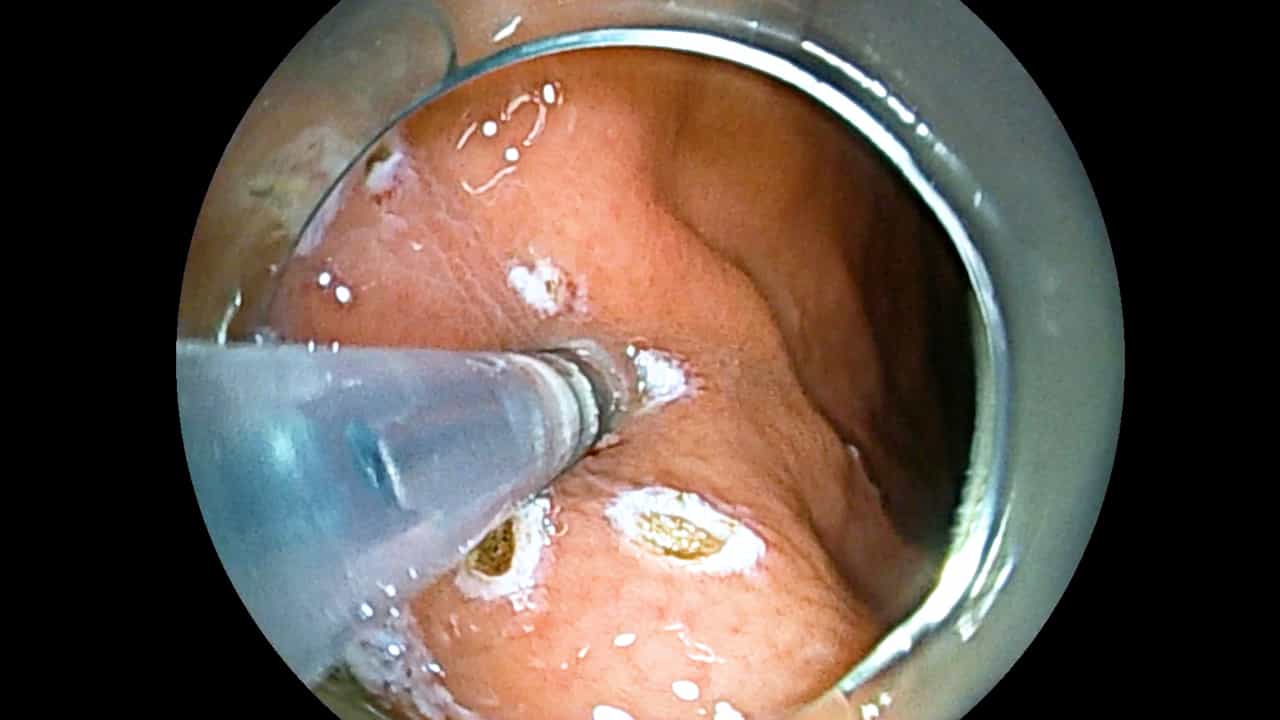
Evaluation of the Effectiveness of Longitudinal Incision for Endoscopic Submucosal Excavation of Gastric Subepithelial Lesions
Published on: April 28, 2026
Prolonged enteral feeding is often required to avoid long-term nutritional and metabolic complications after
Chrystèle Madre1, Lydia Serhal, Laurent Michaud
1Assistance Publique-Hôpitaux de Paris, Université Paris Diderot, Hôpital Robert Debré, Paris, France.

Insights
Total esophagogastric dissociation (TED) effectively treats GERD but can lead to significant nutritional and metabolic issues. Long-term monitoring and prolonged enteral nutrition are crucial for children undergoing this procedure.
Area of Science:
- Pediatric Surgery
- Gastroenterology
- Nutritional Science
Background:
- Total esophagogastric dissociation (TED) is a surgical procedure initially for severe GERD in neurologically impaired children.
- TED is increasingly used for other conditions like esophageal atresia and caustic esophageal injuries.
- Long-term nutritional and metabolic outcomes of TED have not been previously documented.
Purpose of the Study:
- To investigate the long-term nutritional and metabolic status of children undergoing TED without neurological impairment.
- To assess growth, blood vitamin and iron levels, lipid malabsorption, and hyperglycemia after TED.
- To evaluate the incidence of complications such as dumping syndrome and malabsorption.
Main Methods:
- Prospective study of children without neurological impairment who underwent TED between 1999 and 2004.
- Detailed assessment of metabolic and nutritional status, including blood tests for iron and vitamins A, D, E, B12.
- Evaluation of lipid malabsorption, hyperglycemia, and growth parameters.
Main Results:
- Seventeen children underwent TED, with a mean follow-up of 6 years; 12% mortality.
- Seven children were weaned from enteral nutrition, but 5 experienced failure to thrive, steatorrhea, or vitamin malabsorption.
- Dumping syndrome occurred in 8 patients, symptomatic in 6.
Conclusions:
- TED is effective for GERD treatment but frequently causes nutritional and metabolic complications.
- Dumping syndrome and chronic digestive malabsorption are significant concerns post-TED, particularly after enteral nutrition weaning.
- Long-term follow-up and prolonged enteral nutrition support are recommended for patients after TED.
Background:
Total esophagogastric dissociation (TED) was first described in 1997 by Bianchi as a new surgical procedure to treat severe gastroesophageal reflux disease (GERD) in children with neurological impairment. Recently, TED has been proposed in other conditions, such as esophageal atresia, esotracheal cleft, or caustic esophageal lesions. Although the long-term results in terms of GERD control have been previously reported, those regarding the nutritional and metabolic status have never been documented.
Patients And Methods:
All patients without neurological impairment with TED between 1999 and 2004 at Robert Debre Hospital and Jeanne de Flandre Hospital, France, were prospectively investigated, paying particular attention to their metabolic and nutritional status (blood concentration of iron and vitamins A, D, E, and B12; lipid malabsorption; and hyperglycemia test) and growth.
Results:
Seventeen children underwent TED. Six received primary procedures, whereas 11 were operated on because of severe respiratory diseases or failure to thrive. The mean follow-up was 6 years (range 3-8 years). Two children died (12%). Seven children were weaned from enteral nutrition support, but 5 of them had failure to thrive, steatorrhea, and/or malabsorption of vitamin B12 and/or fat-soluble vitamins. Eight patients had dumping syndrome, which was symptomatic in 6 cases.
Conclusions:
TED is an effective procedure for treatment of GERD. However, nutritional and metabolic complications including dumping syndrome and chronic digestive malabsorption are frequent after TED, especially after enteral nutrition weaning. A long-term follow-up of these patients is thus necessary and prolonged enteral nutrition support is recommended.

Related Concept Videos
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube through...
 01:26
Enteral Nutrition I: Orogastric and Nasogastric Feeding
Orogastric (OG) and nasogastric (NG) feeding are two standard methods used for enteral nutrition. Enteral nutrition is often preferred over...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:29
Endoscopic Procedures I: Esophagogastroduodenoscopy
During an EGD, the endoscope can be used to:
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:11
Pyloric Obstruction