Related Experiment Video
Updated: Jun 21, 2026
Spinal Sonography for Ultrasound-Guided Lumbar Neuraxial Anesthesia
Published on: January 31, 2025
Precision of traditional approaches for lumbar plexus block: impact and management of interindividual anatomic
Axel R Heller1, Alexander Fuchs, Thomas Rössel
1Clinic of Anesthesiology and Intensive Care Medicine, Carl Gustav Carus University Hospital, University of Technology, Dresden, Germany. axel.heller@mailbox.tu-dresden.de

Background:
Traditional methods for approaching the lumbar plexus from the posterior rely on finding the intersection of lines that are drawn based on surface landmarks. These methods may be inaccurate in many cases. The aim of this study was to determine the accuracy of these traditional approaches and determine if modifications could increase their accuracy.
Methods:
The lumbar plexus region of 48 cadavers (78 +/- 7 yr; 167 +/- 6 cm; 60 +/- 13 kg; men/women: 29/19) was dissected, and relevant anatomic structures were marked. Needle proximity curves were obtained by triangulation for the five traditional approaches and for vectors from the posterior superior iliac spine directed towards the lumbar spinous processes of L3 and towards L4.
Results:
Proximity curves (mean +/- SD) showed that except Pandin's approach (13 +/- 5 mm too medial), all others were too lateral: Winnie (17 +/- 8 mm), Chayen (8 +/- 5 mm), Capdevila (6 +/- 4 mm), and Dekrey (17 +/- 6 mm). Further, the curves had a narrow parabolic shape and thus a narrow margin of error. Both diagonal vectors had a significantly higher proximity to the lumbar plexus as compared with traditional approaches with a wide parabola, indicating more error tolerance. Using the vector posterior superior iliac spine-L3 with a length between 1/6-1/3 (= 16-22 mm) of the distance posterior superior iliac spine-L3, a proximity to the lumbar plexus < 5.0 +/- 0.3 mm was reached.
Conclusion:
Improvement of both the proximity and the margin of error is possible by using diagonal landmark vectors. Relying on the position of the posterior superior iliac spine eliminates the sex and sided differences and individual body size, which can be problematic if firm metric distances are used in determining the entry point.

Related Concept Videos
 01:11
Local Anesthetics: Clinical Application as Spinal Anesthesia
 01:24
Local Anesthetics: Differential Sensitivity of Nerve Fibers
 01:16
Local Anesthetics: Clinical Application as Intravenous Regional Anesthesia
One of the advantages of...
 01:21
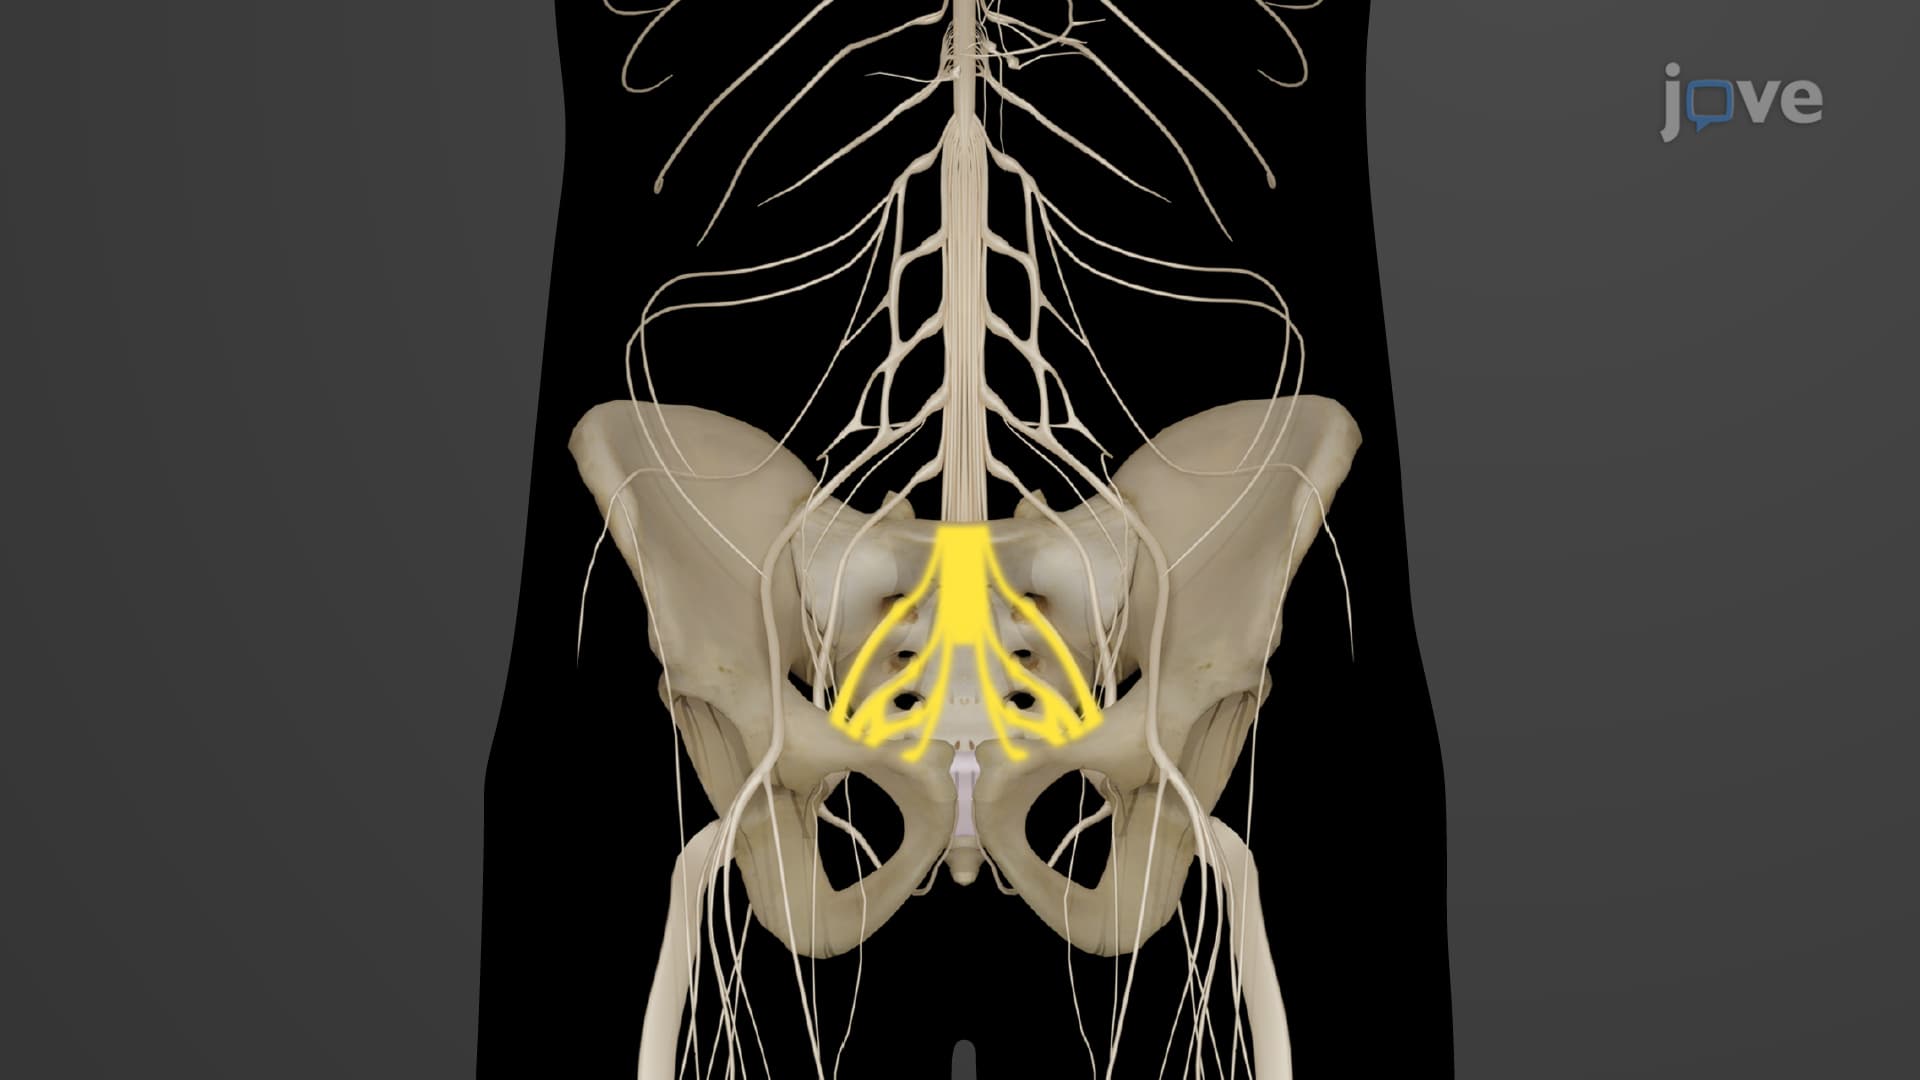
Spinal Nerves: Plexus II
The Lumbar Plexus
The lumbar plexus is situated within the lumbar region of the back and is primarily formed by the first four lumbar spinal nerves (L1 to L4). This plexus extends its branches into several nerves, including the...
 01:29
Local Anesthetics: Clinical Application as Epidural Anesthesia
Since epidural anesthetics can be infused through an epidural catheter, all types of drugs, including short-acting ones, can be administered. Chloroprocaine and lidocaine are examples of short and long-duration anesthetics, respectively. Bupivacaine...
 01:22
Spinal Nerves: Plexus I
The Cervical Plexus
The cervical plexus, formed by the anterior rami of the first four...