Related Experiment Video
Updated: Jun 21, 2026


Non-Intubated Video-Assisted Thoracoscopic Surgery
Published on: May 26, 2023
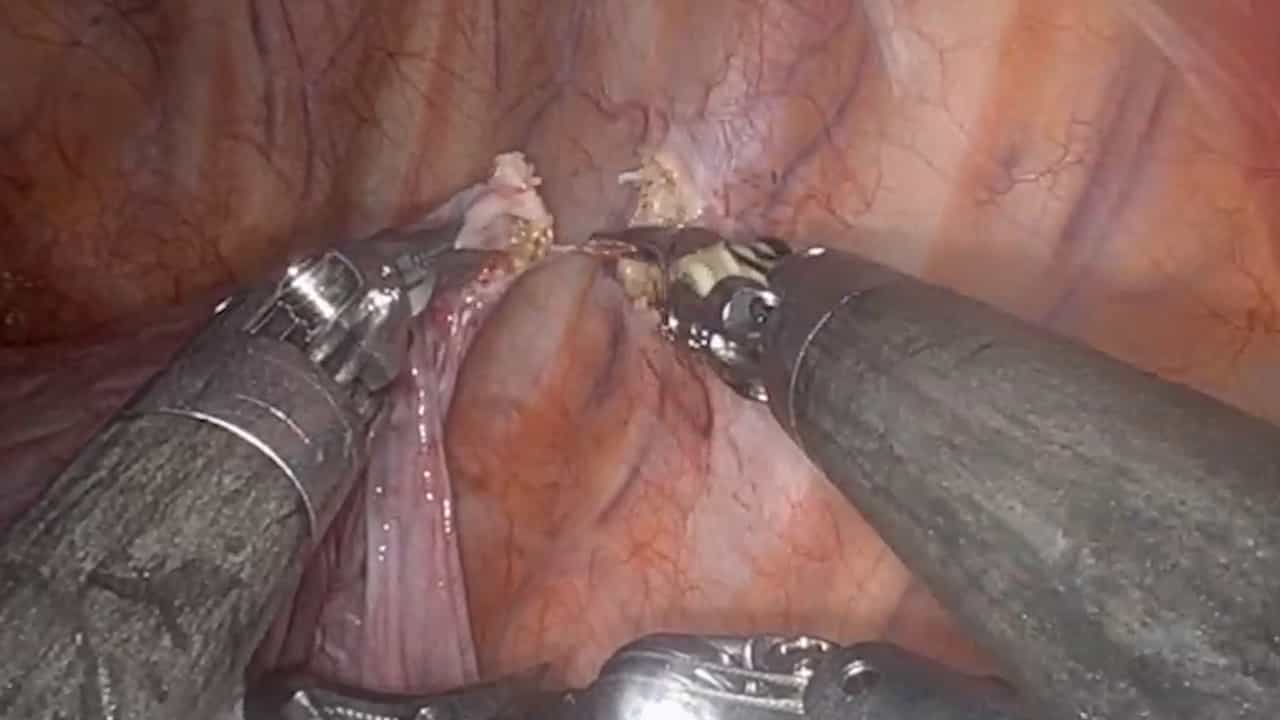
Fast-track video-assisted bullectomy and pleurectomy for pneumothorax: initial experience and description of
1John Radcliffe Hospital, Headington, Oxford, UK.

Objective:
Pleurectomy+/-bullectomy by video-assisted thoracoscopic surgery (VATS) is an established surgical procedure for pneumothorax. Early ambulation and discharge should be a reasonable goal. This study explores the feasibility of day-case surgery and identifies the obstacles requiring further work to facilitate day-case pneumothorax surgery.
Methods:
Between June 2007 and May 2008, 16 consecutive patients underwent video-assisted thoracoscopic surgery bullectomy+/-pleurectomy (under the care of a single surgeon) with immediate connection to an ambulatory drainage system in the theatre following surgery. Analgesia comprised temporary paravertebral with early conversion to oral opiate+/-paracetamol. There were 13 males (81%), average age 23 (range: 17-29) years, and three females (19%), average age 35 (range: 22-46) years. Twelve patients (75%) had left-sided disease, of which nine (56%) underwent elective surgery. All patients had previously suffered at least one primary spontaneous pneumothorax. Patients with probable secondary pneumothorax were excluded from the study. Length of stay (LOS) was compared with a control group of patients conventionally treated prior to the study.
Results:
In 13 patients (81%), early discharge was achieved 1 (range: 1-2 days) day post-op, whilst connected to an ambulatory drainage system. In three patients, early discharge was not achieved. One of these patients had the chest drain removed prematurely and remained an inpatient for 3 days with aspiration and observation for a small pneumothorax. The two remaining patients required extended inpatient admissions due to postoperative non-surgical complications. In the 13 patients discharged immediately, the time to drain removal (in clinic) was electively 7 days (range: 2-11 days). Two patients required re-admission: one for contralateral spontaneous pneumothorax and another for an ipsilateral basal pneumothorax treated with a drain.
Conclusion:
We have shown early discharge with ongoing ambulatory drainage following VATS pleurectomy+/-bullectomy in patients with primary pneumothorax to be feasible with paravertebral in the theatre and rapid conversion to oral analgesia. Patients managed intercostal drains at home. Limiting factors such as postoperative nausea and pain control usually can be sufficiently managed in the outpatient. Shorter stays may have a beneficial financial result. Long-term follow-up and a quantification of the patients experience is warranted.

Related Concept Videos
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:30
Endoscopic Studies I: Bronchoscopy and Thoracoscopy
Bronchoscopy
Description
Bronchoscopy is a procedure that involves direct visualization of the larynx, trachea, and bronchi for diagnostic and therapeutic purposes. A flexible fiber optic or rigid bronchoscope is used to carry out the procedure. The fiber-optic bronchoscope is more frequently used due to...
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:26
Pneumothorax-I
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.