Related Experiment Video
Updated: Jun 20, 2026
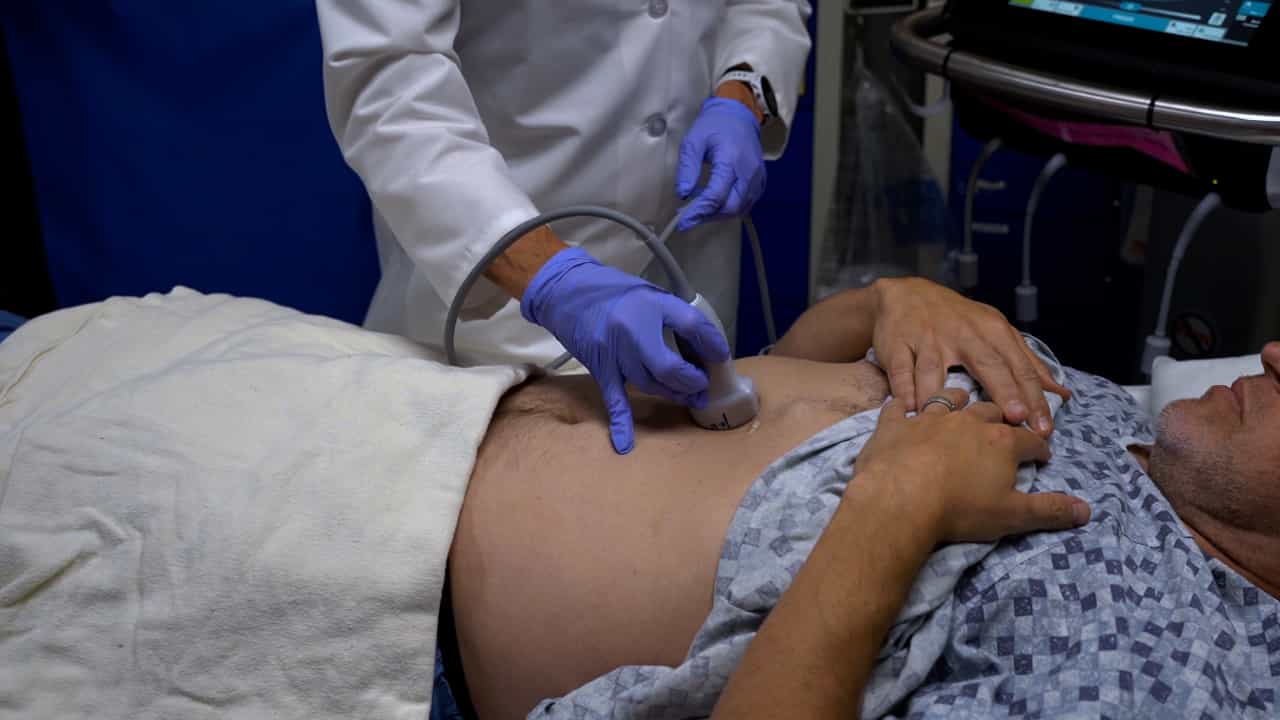
Gastric Point of Care Ultrasound in Adults: Image Acquisition and Interpretation
Published on: September 22, 2023
Overweight/obesity and gastric fluid characteristics in pediatric day surgery: implications for fasting guidelines
Scott D Cook-Sather1, Paul R Gallagher, Lydia E Kruge
1Department of Anesthesiology and Critical Care Medicine, The Children's Hospital of Philadelphia, The University of Pennsylvania School of Medicine, Philadelphia, PA 19104-4399, USA. sather@email.chop.edu

Insights
Pediatric day surgery patients who are overweight or obese can safely fast for 2 hours before procedures. Gastric fluid volumes (GFV) remain low, indicating a reduced risk of pulmonary aspiration in these children.
Area of Science:
- Pediatric Anesthesiology
- Surgical Patient Safety
- Pediatric Gastroenterology
Background:
- The safety of 2-hour preoperative clear liquid fasting in overweight/obese pediatric day surgical patients is not well-established.
- Previous studies in healthy children and obese adults suggest low gastric fluid volumes (GFV) after a 2-hour fast, indicating reduced pulmonary aspiration risk.
- This study aimed to determine the prevalence of overweight/obesity in pediatric day surgery patients and assess its impact on GFV and gastric fluid pH.
Purpose of the Study:
- To measure the prevalence of overweight and obesity in pediatric day surgery patients.
- To evaluate the effect of body mass index (BMI) percentile and fasting duration on gastric fluid volume (GFV) and gastric fluid pH.
- To assess the incidence of emesis and pulmonary aspiration in children allowed clear liquids up to 2 hours before surgery, particularly in overweight/obese individuals.
Main Methods:
- 1000 consecutive pediatric day surgery patients (aged 2-12 years) were enrolled.
- Gastric contents were evacuated via orogastric tube after tracheal intubation to measure GFV and pH.
- Patients were classified by BMI percentile using CDC growth charts; GFV was corrected for ideal body weight (GFV(IBW)).
Main Results:
- 14.0% of patients were overweight and 13.3% were obese.
- GFV(IBW) was similar across all BMI categories (mean 0.96 mL/kg) and did not correlate with fasting duration.
- Decreased gastric fluid acidity was associated with increased BMI percentile; emesis occurred in 8 patients, with no pulmonary aspiration events.
Conclusions:
- 27% of pediatric day surgery patients are overweight/obese.
- Overweight/obese children can safely consume clear liquids up to 2 hours before surgery, with average GFV(IBW) of approximately 1 mL/kg.
- Emesis episodes were rare and not linked to shortened fasting intervals in this population.
Background:
The safety of 2-h preoperative clear liquid fasts has not been established for overweight/obese pediatric day surgical patients. Healthy children and obese adults who fasted 2 h have small residual gastric fluid volumes (GFVs), which are thought to reflect low pulmonary aspiration risk. We sought to measure the prevalence of overweight/obesity in our day surgery population. We hypothesized that neither body mass index (BMI) percentile nor fasting duration would significantly affect GFV or gastric fluid pH. In children who were allowed clear liquids up until 2 h before surgery, we hypothesized that overweight/obese subjects would not have increased GFV over lean/normal subjects and that emesis/pulmonary aspiration events would be rare.
Methods:
Demographics, medical history, height, and weight were recorded for 1000 consecutive day surgery patients aged 2-12 yr. In addition, 1000 day surgery patients (age 2-12 yr) undergoing general endotracheal anesthesia were enrolled. After tracheal intubation, a 14-18F orogastric tube was inserted and gastric contents evacuated. Medications, fasting interval, GFV, pH, and emetic episodes were documented. Age- and gender-specific Center for Disease Control and Prevention growth charts (2000) were used to determine ideal body weight (IBW = 50th percentile) and to classify patients as lean/normal (BMI 25th-75th percentile), overweight (BMI > or = 85th to <95th percentile), or obese (BMI > or = 95th percentile).
Results:
Of all day surgery patients, 14.0% were overweight and 13.3% were obese. Obese children had lower GFV per total body weight (P < 0.001). When corrected for IBW, however, volumes GFV(IBW) were identical across all BMI categories (mean 0.96 mL/kg, sd 0.71; median 0.86 mL/kg, IQR 0.96). Preoperative acetaminophen and midazolam contributed to increased GFV(IBW) (P = 0.025 and P = 0.001). Lower GFV(IBW) was associated with ASA physical status III (P = 0.024), male gender (P = 0.012), gastroesophageal reflux disease (P = 0.049), and proton pump inhibitor administration (P = 0.018). GFV(IBW) did not correlate with fasting duration or age. Decreased gastric fluid acidity was associated with younger age (P = 0.005), increased BMI percentile (P = 0.036), and African American race (P = 0.033). Emesis on induction occurred in eight patients (50% of whom were obese, P = 0.052, and 75% of whom had obstructive sleep apnea, P = 0.061). Emesis was associated with increased ASA physical status (P = 0.006) but not with fasting duration. There were no pulmonary aspiration events.
Conclusions:
Twenty-seven percent of pediatric day surgery patients are overweight/obese. These children may be allowed clear liquids 2 h before surgery as GFV(IBW) averages 1 mL/kg regardless of BMI and fasting interval. Rare emetic episodes were not associated with shortened fasting intervals in this population.
More Related Videos

Related Concept Videos
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:21
Drug Dosing: Obese Patients
 01:11
Pyloric Obstruction
 01:25
Pharmacokinetics in Obese Patients: Drug Absorption and Distribution
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed.
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube through...