Related Experiment Video
Updated: Jun 20, 2026


Vessel-sparing Excision and Primary Anastomosis
Published on: January 7, 2019
What is the optimal surgical strategy for bulbous urethral stricture in boys?
David A Diamond1, Jiang Xuewu, Stuart B Bauer
1Department of Urology, Children's Hospital, Harvard Medical School, Boston, Massachusetts 02115, USA. David.diamond@childrens.harvard.edu

Insights
Open reconstruction offers better outcomes for pediatric bulbous urethral strictures than direct vision internal urethrotomy. For definitive treatment, aggressive end-to-end repair is recommended, with a single urethrotomy attempt if initial open repair is not chosen.
Area of Science:
- Pediatric Urology
- Surgical Reconstruction
- Urethral Stricture Management
Background:
- Bulbous urethral stricture management in children lacks defined optimal strategies.
- Direct vision internal urethrotomy and open repair are common surgical approaches.
Purpose of the Study:
- To compare long-term outcomes of direct vision internal urethrotomy and open repair for pediatric bulbous urethral strictures.
- To define the optimal surgical strategy for these conditions.
Main Methods:
- Retrospective review of 63 pediatric patients undergoing direct vision internal urethrotomy or open repair.
- Analysis of success rates, number of procedures, and follow-up duration (mean 30 months for urethrotomy, 16 months for open repair).
- Procedures included urethroplasty (end-to-end repair, patch graft, or tube) and urethrotomy.
Main Results:
- Initial direct vision internal urethrotomy success rate was 53% (28/53), increasing to 59% (43/73) with multiple procedures.
- Open repair achieved an 80% success rate (8/10) with a single procedure.
- Combined urethrotomy/open approach had a 78% success rate (7/9).
Conclusions:
- Open reconstruction demonstrates superior success rates compared to initial direct vision internal urethrotomy for pediatric bulbous urethral strictures.
- End-to-end urethroplasty is often a definitive solution.
- If direct vision internal urethrotomy is chosen, a single attempt is advised, followed by open repair if needed.
Purpose:
Optimal management for bulbous urethral stricture in children is poorly defined. We compared our long-term experience with direct vision internal urethrotomy and open repair to define the optimal surgical strategy.
Materials And Methods:
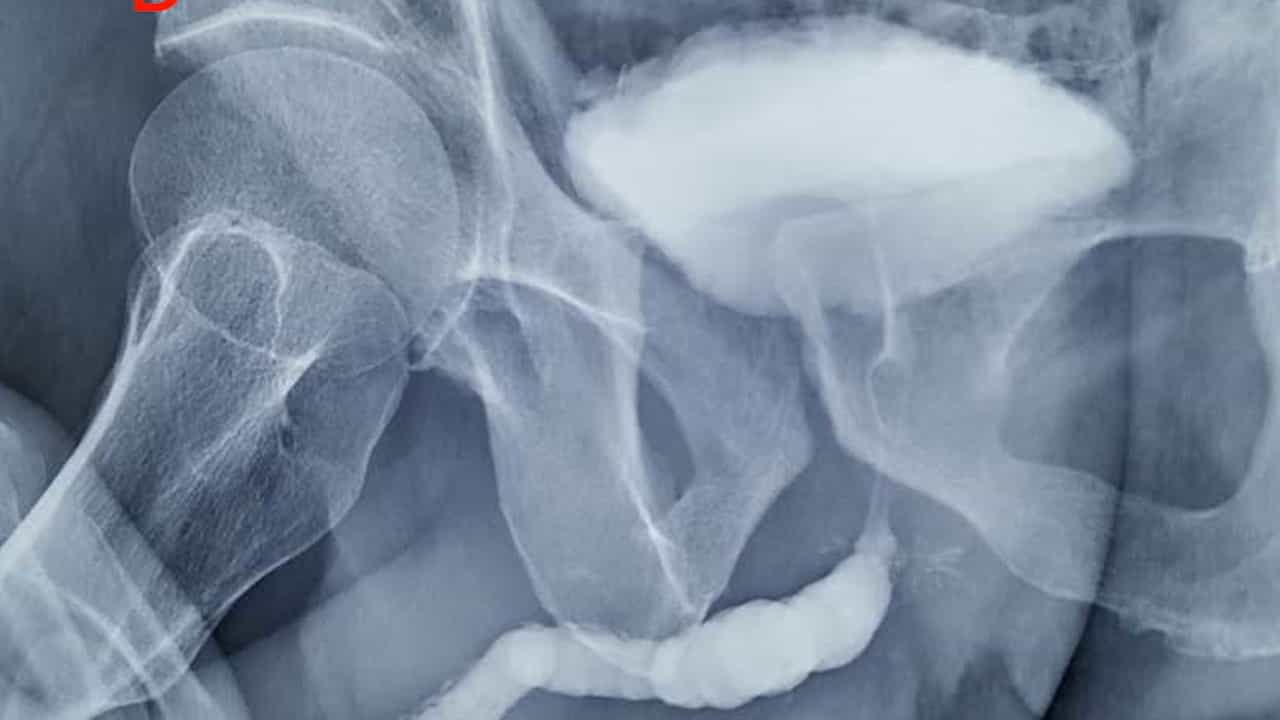
We reviewed the records of 63 patients who underwent direct vision internal urethrotomy or open repair. A total of 46 patients (73%) were treated with 1 or more urethrotomies. Of the patients 17 (27%) underwent urethroplasty, 13 underwent end-to-end repair and 4 received a patch graft or tube. Eight of 17 cases required urethroplasty only, whereas in 9 combined open repair and urethrotomy were done. Mean patient age was 14.1 years (range 5 months to 21 years). Followup included voiding cystourethrogram, retrograde urethrogram and/or cystoscopy, or flow rate. Mean followup was 30 months for urethrotomy and 16 months for open urethroplasty.
Results:
When direct vision internal urethrotomy was the initial approach, 1 procedure was successful in 28 of 53 cases (53%). Multiple urethrotomies increased the success rate to 59% (43 of 73 cases). The 53 patients with urethrotomy required a total of 84 procedures (mean 1.6 each). When open repair was the initial approach, 1 procedure was successful in 8 of 10 cases (80%). A total of 12 procedures (mean 1.2 each) were required in those 10 cases. A combined urethrotomy/open approach with 2 procedures was successful in 78% of cases (7 of 9).
Conclusions:
Open reconstruction is more successful than direct vision internal urethrotomy as the initial approach to bulbous urethral strictures. Although aggressive, end-to-end repair usually provides a definitive solution. Initial direct vision internal urethrotomy is successful in half of the cases and repeat urethrotomy adds little to success. The success of the combined urethrotomy/open approach approximates that of initial open reconstruction. If initial direct vision internal urethrotomy is elected, we advocate only 1 attempt, followed by open end-to-end urethroplasty if necessary.
Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:25
Urinary Tract Calculi VI: Surgical Management