Related Experiment Video
Updated: Jun 20, 2026


Laparoscopic Repair of Para-Esophageal Hernia Using Absorbable Biosynthetic Mesh
Published on: September 11, 2021
Delayed presentation of congenital diaphragmatic hernia with intrathoracic gastric volvulus
Ramazan Karabulut1, Zafer Türkyilmaz, Kaan Sönmez
1Department of Pediatric Surgery, Gazi University Medical Faculty, 06500, Ankara, Turkey. karabulutr@yahoo.com

Insights
Gastric volvulus (GV) is a rare but life-threatening obstruction in children. Prompt diagnosis and surgical intervention are crucial to prevent gastric necrosis and ensure favorable outcomes.
Area of Science:
- Pediatric Surgery
- Gastroenterology
- Radiology
Background:
- Gastric volvulus (GV) is a rare upper gastrointestinal obstruction caused by abnormal stomach rotation.
- Intrathoracic GV, particularly with delayed congenital diaphragmatic hernia, presents unique diagnostic and management challenges in infants.
Observation:
- A 16-month-old infant presented with recurrent projectile vomiting and epigastric pain, initially resolving then recurring.
- Physical examination revealed epigastric fullness and a palpable mass.
- Radiological studies, including barium contrast, confirmed mesenteroaxial gastric volvulus.
Findings:
- Laparotomy revealed non-necrotic intrathoracic gastric volvulus with an intrathoracic spleen and a large left-sided congenital diaphragmatic hernia.
- Surgical repair involved diaphragmatic repair, gastropexy, and splenopexy.
Implications:
- This case highlights the importance of considering intrathoracic gastric volvulus in infants with unexplained vomiting and diaphragmatic abnormalities.
- Timely diagnosis via upper gastrointestinal studies and CT scans is critical.
- Prompt surgical management is essential to prevent gastric ischemia and ensure patient survival.
Background:
Gastric volvulus (GV) occurs when the stomach abnormally rotates around one of its axes and is a rare upper gastrointestinal obstruction. We present an unusual case of intrathoracic GV associated with delayed manifestation of congenital diaphragmatic hernia.
Methods:
A 16-month-old female infant presented with a history of projectile non-bilious vomiting for 2 days and mild hematemesis for the last day. Physical examination showed epigastric fullness and pain with abdominal palpation. Complaints of the patient disappeared on the 2nd day after hospital admission. On the 6th day non-bilious vomiting started again and an epigastric mass was palpable. Contrast study of the stomach after oral barium administration showed the mesenteroaxial volvulus of the stomach. At laparotomy, the association of non-necrotic intrathoracic GV with intrathoracic spleen was confirmed. Moreover, the diaphragm presented a giant posterolateral hernia of the left dome. Diaphragmatic repair was performed in addition to gastropexy and splenopexy.
Results:
The postoperative course was uneventful and the child was discharged on the 5th post-operative day. On follow up after one month, clinical examination and plain abdominal X-ray were normal.
Conclusions:
GV is a clinical emergency which can be life-threatening for children. Upper gastrointestinal study and CT scan with contrast meal are helpful in the diagnosis of the lesion. We emphasize prompt surgical therapy to avoid gastric necrosis.
Related Concept Videos
 01:25
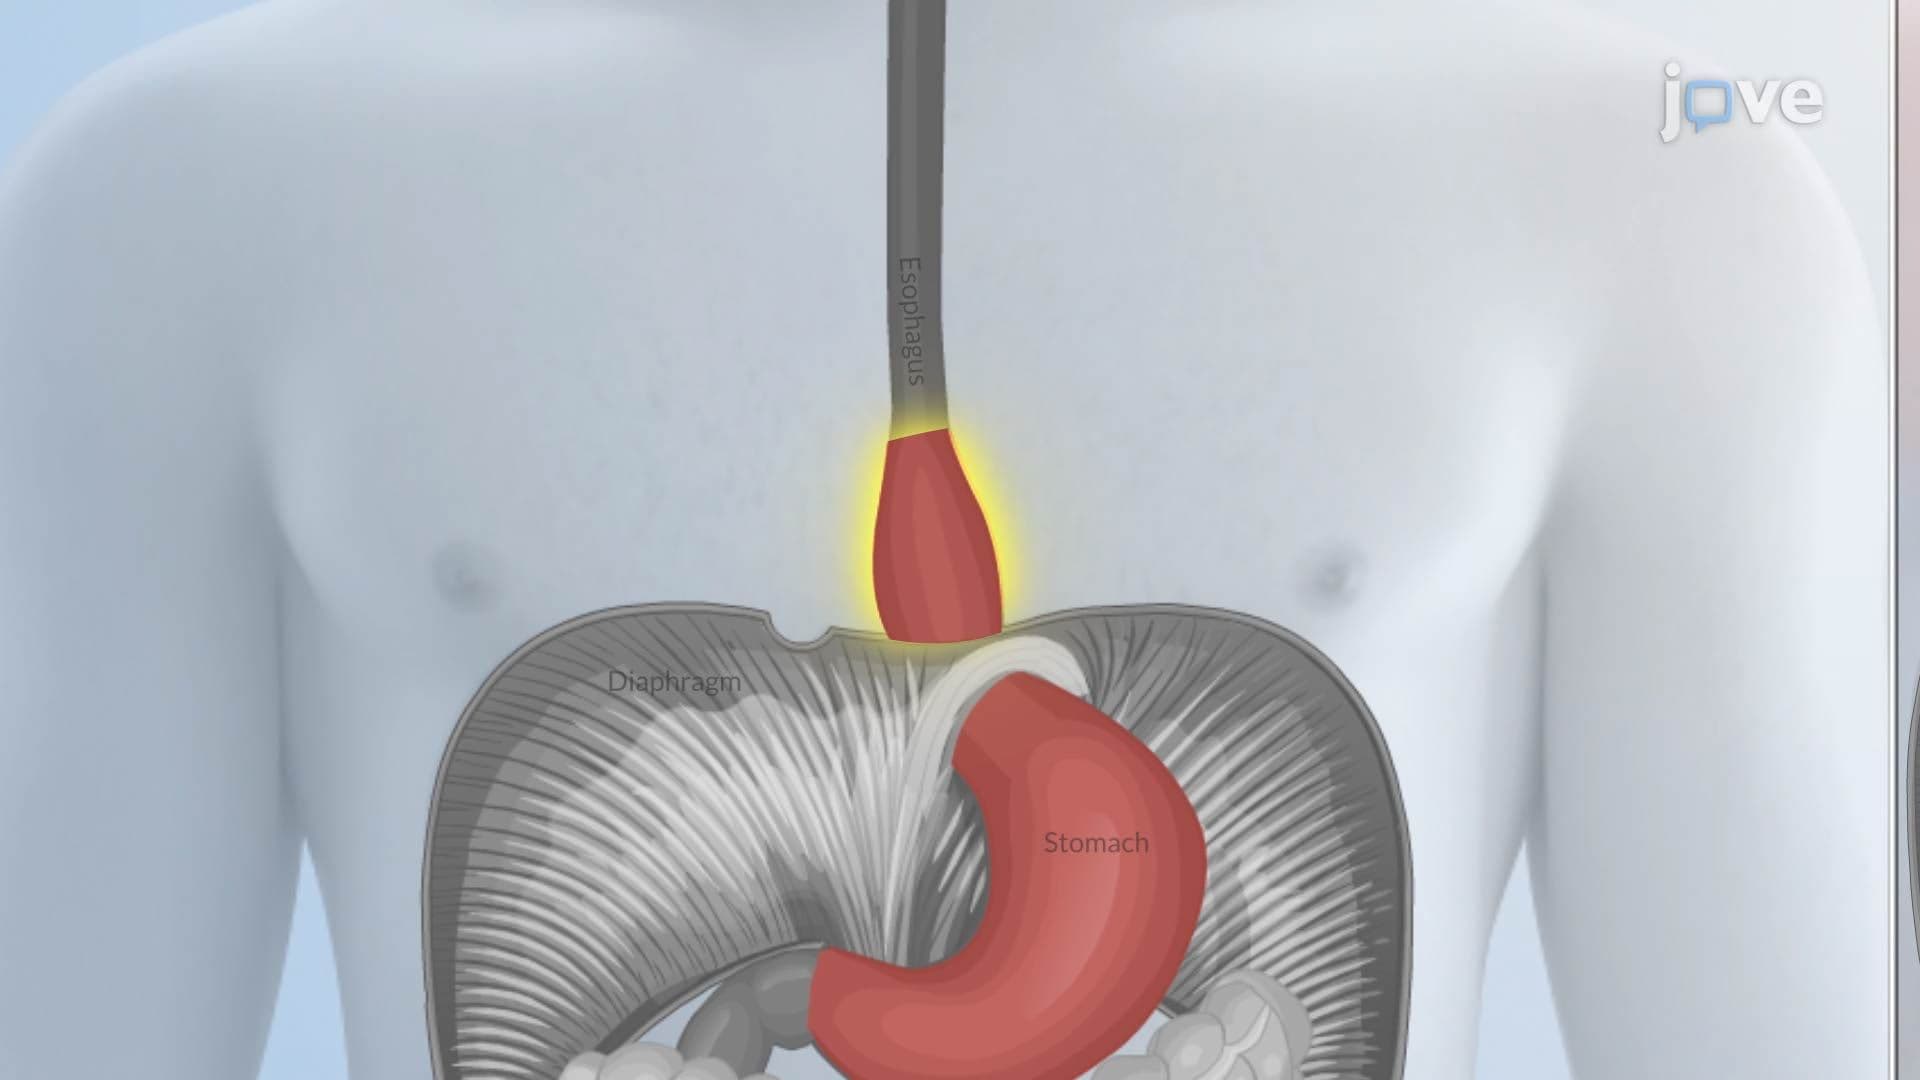
Hiatal Hernia
 01:11
Pyloric Obstruction
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus.
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...