Related Experiment Video
Updated: Jun 20, 2026


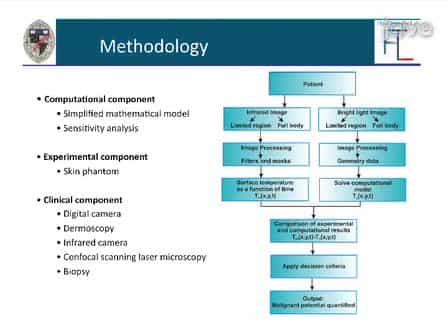
Dual-mode Imaging of Cutaneous Tissue Oxygenation and Vascular Function
Published on: December 8, 2010
On the possibility of non-invasive multilayer temperature estimation using soft-computing methods
C A Teixeira1, W C A Pereira, A E Ruano
1Centre for Informatics and Systems, Faculty of Sciences and Technology, University of Coimbra, 3030-290 Coimbra, Portugal. cteixei@dei.uc.pt

Objective And Motivation:
This work reports original results on the possibility of non-invasive temperature estimation (NITE) in a multilayered phantom by applying soft-computing methods. The existence of reliable non-invasive temperature estimator models would improve the security and efficacy of thermal therapies. These points would lead to a broader acceptance of this kind of therapies. Several approaches based on medical imaging technologies were proposed, magnetic resonance imaging (MRI) being appointed as the only one to achieve the acceptable temperature resolutions for hyperthermia purposes. However, MRI intrinsic characteristics (e.g., high instrumentation cost) lead us to use backscattered ultrasound (BSU). Among the different BSU features, temporal echo-shifts have received a major attention. These shifts are due to changes of speed-of-sound and expansion of the medium.
Novelty Aspects:
The originality of this work involves two aspects: the estimator model itself is original (based on soft-computing methods) and the application to temperature estimation in a three-layer phantom is also not reported in literature.
Materials And Methods:
In this work a three-layer (non-homogeneous) phantom was developed. The two external layers were composed of (in % of weight): 86.5% degassed water, 11% glycerin and 2.5% agar-agar. The intermediate layer was obtained by adding graphite powder in the amount of 2% of the water weight to the above composition. The phantom was developed to have attenuation and speed-of-sound similar to in vivo muscle, according to the literature. BSU signals were collected and cumulative temporal echo-shifts computed. These shifts and the past temperature values were then considered as possible estimators inputs. A soft-computing methodology was applied to look for appropriate multilayered temperature estimators. The methodology involves radial-basis functions neural networks (RBFNN) with structure optimized by the multi-objective genetic algorithm (MOGA). In this work 40 operating conditions were considered, i.e. five 5-mm spaced spatial points and eight therapeutic intensities (I(SATA)): 0.3, 0.5, 0.7, 1.0, 1.3, 1.5, 1.7 and 2.0W/cm(2). Models were trained and selected to estimate temperature at only four intensities, then during the validation phase, the best-fitted models were analyzed in data collected at the eight intensities. This procedure leads to a more realistic evaluation of the generalisation level of the best-obtained structures.
Results And Discussion:
At the end of the identification phase, 82 (preferable) estimator models were achieved. The majority of them present an average maximum absolute error (MAE) inferior to 0.5 degrees C. The best-fitted estimator presents a MAE of only 0.4 degrees C for both the 40 operating conditions. This means that the gold-standard maximum error (0.5 degrees C) pointed for hyperthermia was fulfilled independently of the intensity and spatial position considered, showing the improved generalisation capacity of the identified estimator models. As the majority of the preferable estimator models, the best one presents 6 inputs and 11 neurons. In addition to the appropriate error performance, the estimator models present also a reduced computational complexity and then the possibility to be applied in real-time.
Conclusions:
A non-invasive temperature estimation model, based on soft-computing technique, was proposed for a three-layered phantom. The best-achieved estimator models presented an appropriate error performance regardless of the spatial point considered (inside or at the interface of the layers) and of the intensity applied. Other methodologies published so far, estimate temperature only in homogeneous media. The main drawback of the proposed methodology is the necessity of a-priory knowledge of the temperature behavior. Data used for training and optimisation should be representative, i.e., they should cover all possible physical situations of the estimation environment.

Related Concept Videos
 01:14
Temperature Measurement Sites
Oral: When assessing oral temperature, the thermometer tip should be placed under the tongue in the posterior sublingual pocket. It offers accurate readings and can be...
 01:19
Assessing Body Temperature - Temporal Artery
Step 1: Perform hand hygiene and don a fresh pair of gloves to prevent cross-infection and ensure patient safety.
Step 2: Explain the procedure to the patient to establish trust. Clear communication establishes trust with the patient, ensures they understand what to expect, promotes cooperation, and enhances comfort during the procedure.
Step 3: Assess the patient's forehead...
 01:43
Thermosensation
 01:13
Equipments Used to Measure Body Temperature
Glass-bulb Thermometer:
Glass-bulb thermometers are hollow glass tubes with a bulb tip containing liquid such as ethanol or mercury. Historically, glass bulb mercury thermometers were the standard device to measure body temperature. Today, mercury thermometers are prohibited in many countries due to the hazardous effects of mercury and the risk of exposure if the glass bulb breaks. In general,...
 01:22
Multi-input and Multi-variable systems
In the absence of...
 01:14
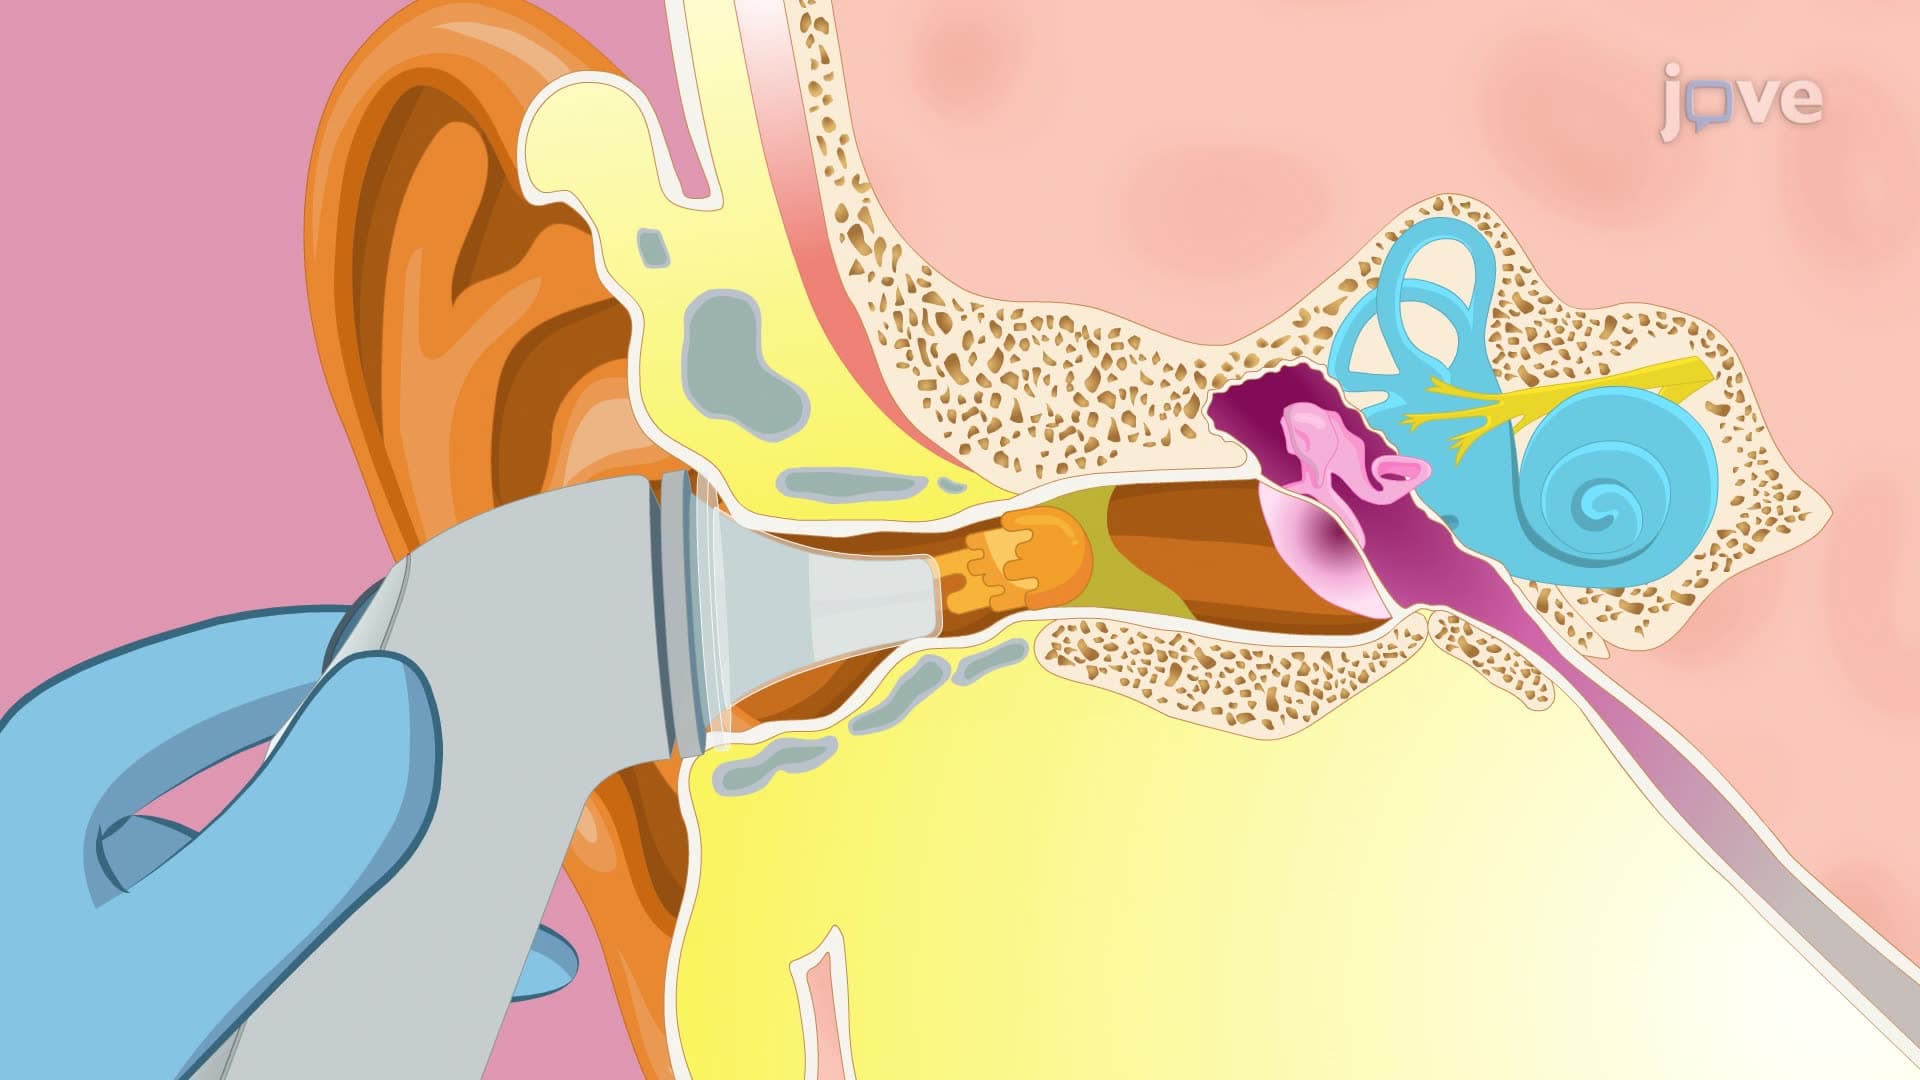
Assessing Body Temperature - Tympanic membrane
Step 1: Begin by practicing good hand hygiene to prevent the transmission of microorganisms.
Step 2: Turn on the thermometer and wait until the ready sign appears on the screen to ensure accurate measurement.
Step 3: Slide the probe cover in place to prevent cross-contamination.
Step 4: Instruct the patient to tilt their head to the side for comfort and check for cerumen...