

Paradoxical amniotic fluid embolism presenting before caesarean section in a woman with an atrial septal defect
1Department of Anaesthesia and Intensive Care, Indraprastha Apollo Hospitals, New Delhi, India. kumarvk42@hotmail.com

We present a case of presumed amniotic fluid embolism in a 33-year-old parturient at 30 weeks of gestation, which occurred just before she was due to receive spinal anaesthesia for urgent caesarean section. While sitting, the woman suddenly lost consciousness, started having convulsions and finally suffered cardiorespiratory collapse. She was resuscitated and a live baby was delivered by emergency caesarean section. An echocardiogram performed postoperatively showed a large atrial septal defect and severe right ventricular dysfunction with moderate pulmonary hypertension. Paradoxical amniotic fluid embolism was diagnosed. After extubation she was aphasic and had a right hemiparesis. She made a good recovery and was discharged from hospital 24 days later, at which time she had a slight weakness on her right side. Three months later she had a normal gait with no obvious neurological deficit.
We present a case of presumed amniotic fluid embolism in a 33-year-old parturient at 30 weeks of gestation, which occurred just before she was due to receive spinal anaesthesia for urgent caesarean section. While sitting, the woman suddenly lost consciousness, started having convulsions and finally suffered cardiorespiratory collapse. She was resuscitated and a live baby was delivered by emergency caesarean section. An echocardiogram performed postoperatively showed a large atrial septal defect and severe right ventricular dysfunction with moderate pulmonary hypertension. Paradoxical amniotic fluid embolism was diagnosed. After extubation she was aphasic and had a right hemiparesis. She made a good recovery and was discharged from hospital 24 days later, at which time she had a slight weakness on her right side. Three months later she had a normal gait with no obvious neurological deficit.


Related Concept Videos
 01:29
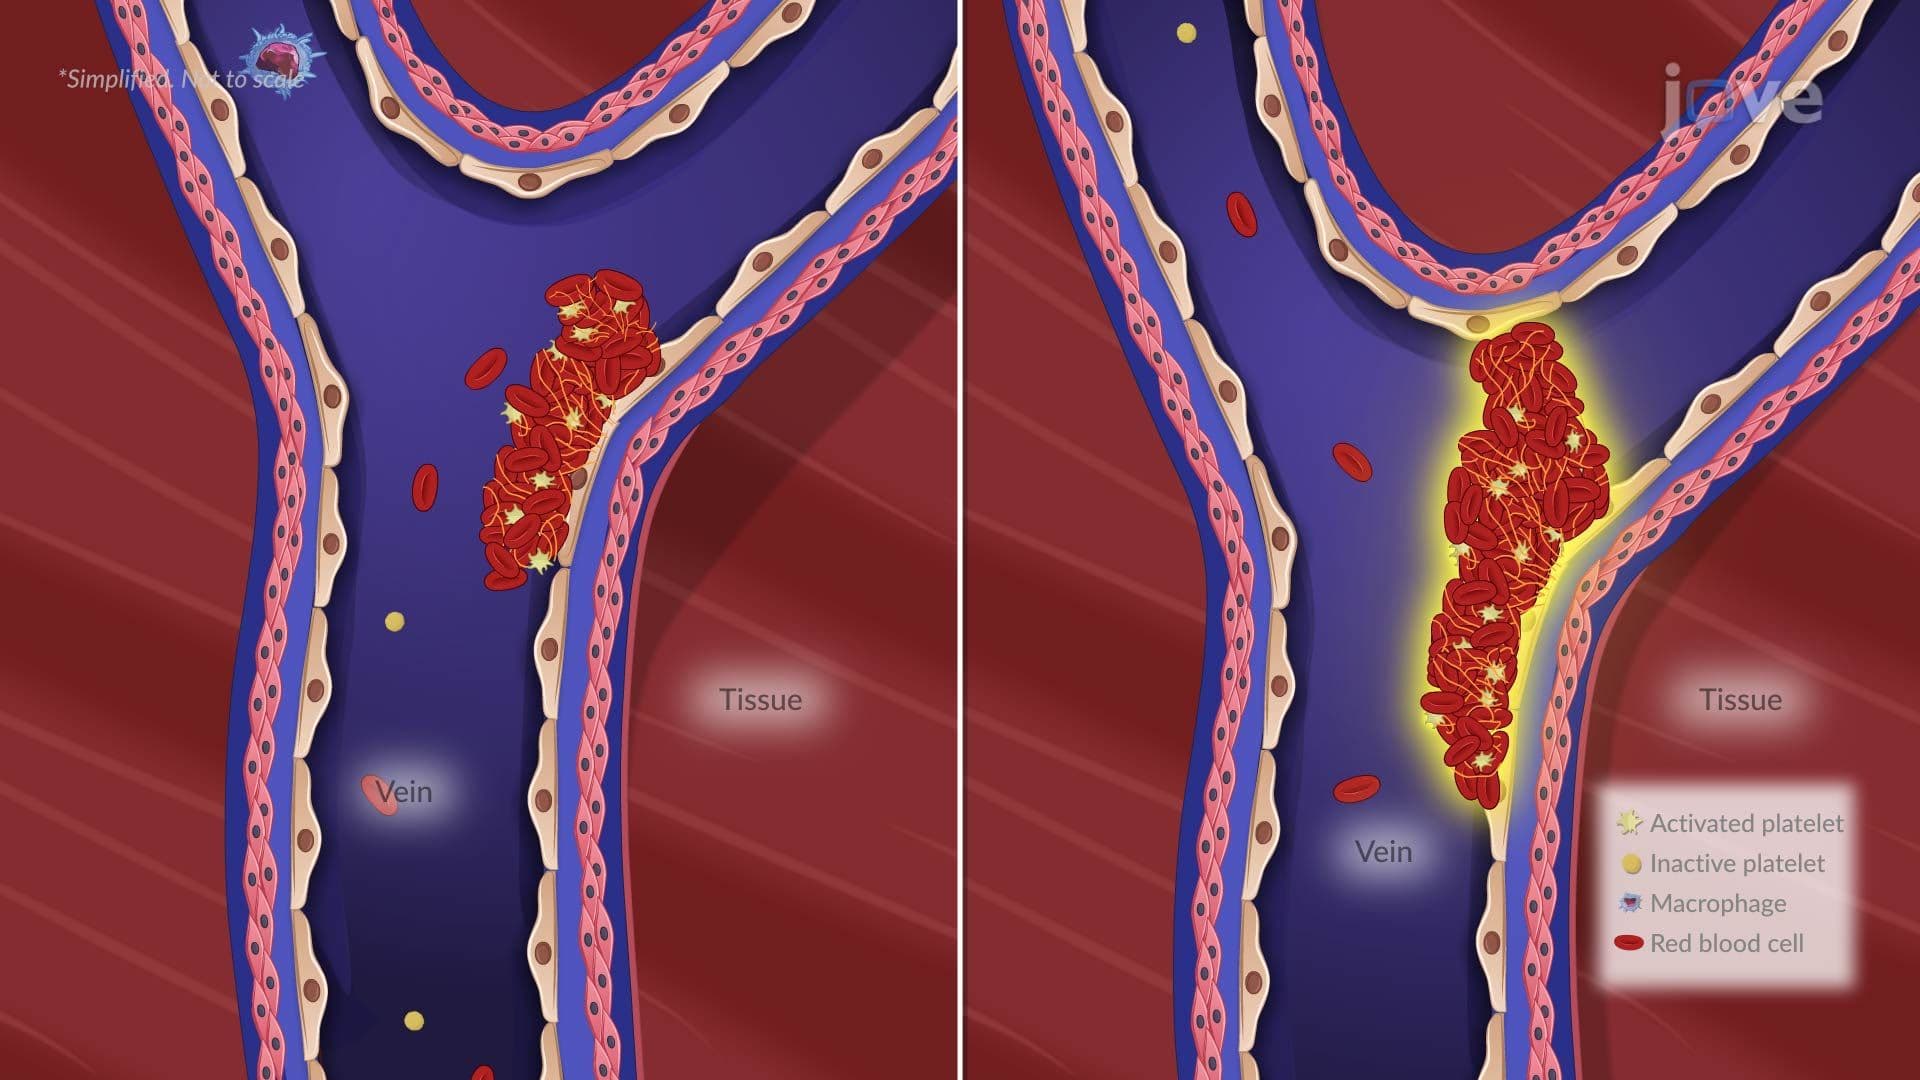
Pulmonary Embolism I: Introduction
 01:19
Pulmonary Embolism I: Introduction
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:18
Pulmonary Edema II: Pathophysiology
 01:10
Atelectasis II: Pathophysiology