Related Experiment Video
Updated: Jun 20, 2026
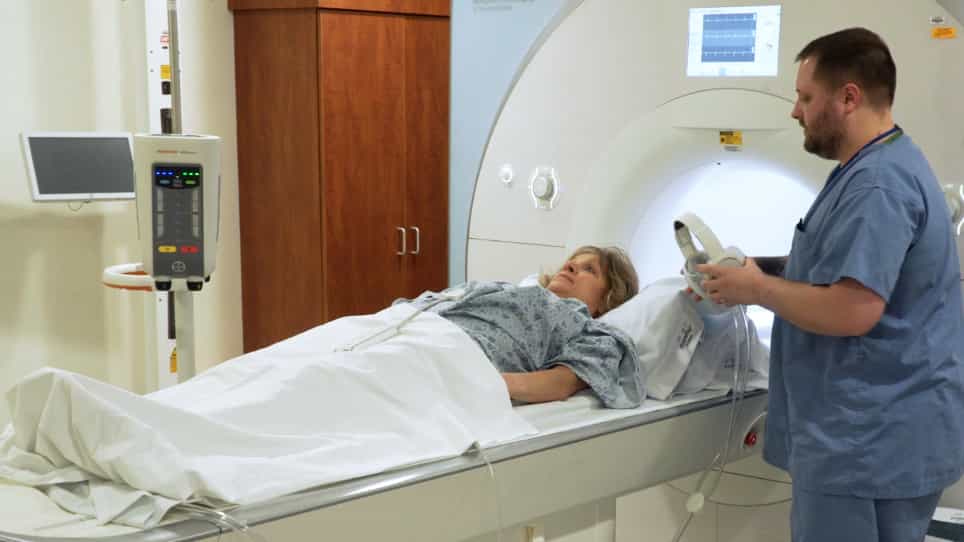
Cardiac Magnetic Resonance for the Evaluation of Suspected Cardiac Thrombus: Conventional and Emerging Techniques
Published on: June 11, 2019
Cardiac magnetic resonance evaluation of edema after ST-elevation acute myocardial infarction
José V Monmeneu1, Vicente Bodí, Juan Sanchis
1ERESA, Unidad de Imagen Cardiaca, Hospital Clínico Universitario de Valencia, Valencia, Spain. jmonmeneu@eresa.com

Insights
Myocardial edema after ST-elevation acute myocardial infarction is common and linked to poor heart function. This cardiac magnetic resonance imaging study shows edema resolves within six months.
Area of Science:
- Cardiology
- Medical Imaging
- Cardiovascular Research
Background:
- ST-elevation acute myocardial infarction (STEMI) can lead to myocardial edema.
- Assessing edema's impact on ventricular function is crucial for patient outcomes.
Purpose of the Study:
- To characterize myocardial edema post-STEMI using cardiac magnetic resonance imaging (CMR).
- To investigate the impact of edema on ventricular function and its evolution over time.
Main Methods:
- 134 STEMI patients underwent CMR, including cine, edema, perfusion, and viability imaging.
- Imaging was repeated at 6 months to assess changes.
- Low-dose dobutamine stress was used to evaluate ventricular function.
Main Results:
- 96.6% of patients showed edema in the first week post-STEMI.
- Extensive edema correlated with larger ventricular volumes, reduced ejection fraction, and more extensive infarcts.
- Edema resolved by 6 months in all patients, but its initial association with functional and infarct characteristics persisted.
Conclusions:
- CMR effectively characterizes myocardial edema after STEMI.
- Extensive edema is associated with impaired left ventricular characteristics.
- Myocardial edema is a transient condition, resolving within 6 months post-STEMI.
Introduction And Objectives:
The aims of the study were to characterize myocardial edema after ST-elevation acute myocardial infarction using cardiac magnetic resonance imaging and to investigate its impact on ventricular function and its subsequent evolution.
Methods:
In total, 134 patients admitted to hospital for a first ST-elevation myocardial infarction who had a patent infarct-related artery underwent cardiac magnetic resonance imaging. Cine images (at rest and with low-dose dobutamine) and edema, perfusion and viability images were acquired. Imaging was repeated after 6 months.
Results:
In the first week after infarction, edema was detected in at least one segment in 96.6% of patients (4+/-2.1 segments per patient). Extensive edema (> or = 4 segments) was associated with large ventricular end-diastolic and end-systolic volumes (P< .0001), a small left ventricular ejection fraction at rest (P=.001) and with low-dose dobutamine (P=.006), a large number of segments showing hypoperfusion (P=.001) or microvascular obstruction (P=.009), a more extensive infarct (P=.017) and greater transmural extent of the infarct (P=.003). The association between the presence and extent of edema during the first week and functional, perfusion and viability variables was still observable after 6 months. No patient exhibited edema at 6 months.
Conclusions:
Cardiac magnetic resonance imaging was useful for characterizing the myocardial edema that occurred after ST-elevation acute myocardial infarction. Extensive edema was associated with poor left ventricular characteristics. Edema was a transitory phenomenon that vanished within 6 months.

Related Concept Videos
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:21
Imaging Studies for Cardiovascular System IV: CMRI
 01:30
Acute Coronary Syndrome I: Introduction
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests