Related Experiment Video
Updated: Jun 20, 2026
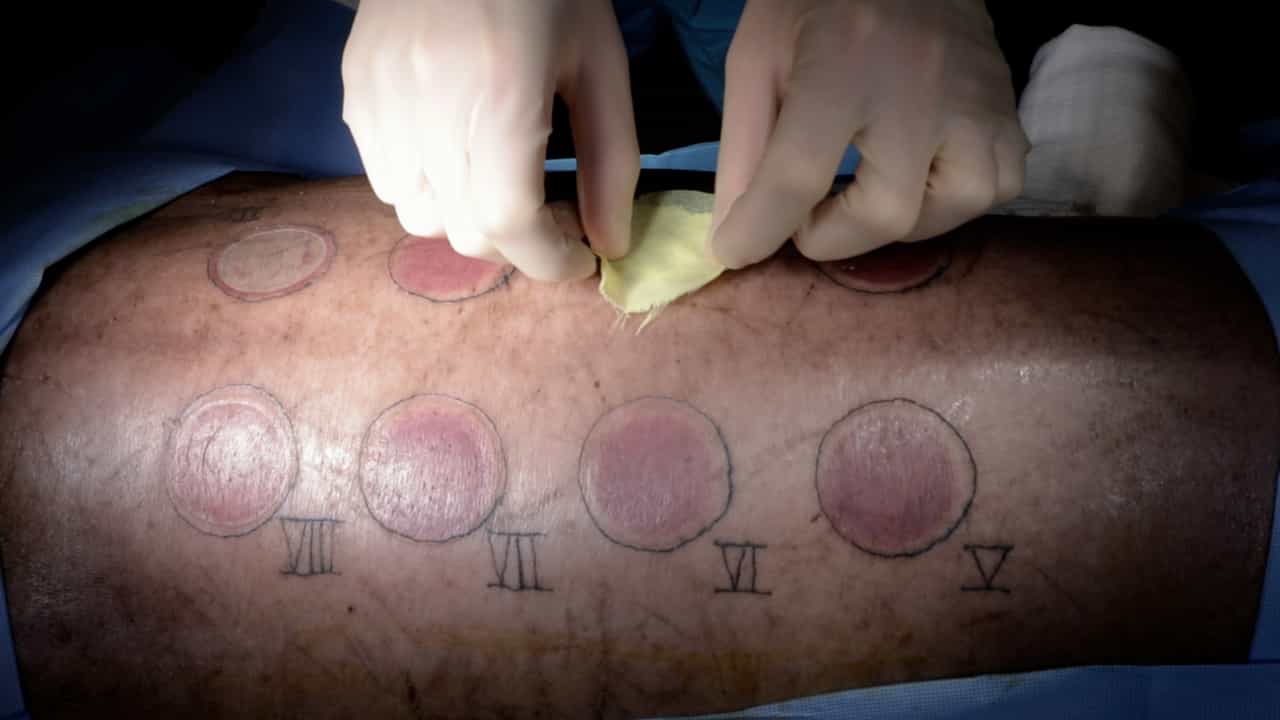

A Swine Burn Model for Investigating the Healing Process in Multiple Depth Burn Wounds
Published on: February 23, 2024
Critical care of the burn patient: the first 48 hours
1Carver College of Medicine, University of Iowa Hospitals & Clinics, Department of Surgery, Iowa City, Iowa, USA. Barbara-latenser@uiowa.edu

Objective:
The goal of this concise review is to provide an overview of some of the most important resuscitation and monitoring issues and approaches that are unique to burn patients compared with the general intensive care unit population.
Study Selection:
Consensus conference findings, clinical trials, and expert medical opinion regarding care of the critically burned patient were gathered and reviewed. Studies focusing on burn shock, resuscitation goals, monitoring tools, and current recommendations for initial burn care were examined.
Conclusions:
The critically burned patient differs from other critically ill patients in many ways, the most important being the necessity of a team approach to patient care. The burn patient is best cared for in a dedicated burn center where resuscitation and monitoring concentrate on the pathophysiology of burns, inhalation injury, and edema formation. Early operative intervention and wound closure, metabolic interventions, early enteral nutrition, and intensive glucose control have led to continued improvements in outcome. Prevention of complications such as hypothermia and compartment syndromes is part of burn critical care. The myriad areas where standards and guidelines are currently determined only by expert opinion will become driven by level 1 data only by continued research into the critical care of the burn patient.

Related Concept Videos
 01:22
Burn Injuries
The damage results in the death of skin cells, which can lead to a massive loss of fluid. Dehydration, electrolyte imbalance, and renal and circulatory failure follow, which can be fatal. Burn patients are treated with intravenous fluids to offset...
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:29
Decreased Body Temperature
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.